PSMB7 / Proteasome subunit beta type-7 · IHC design guide

Design Immunohistochemistry for PSMB7

Plan PSMB7 chromogenic IHC in paraffin sections around its nuclear and cytoplasmic tissue staining (HPA tissue IHC). The guide covers fixation consistency, antibody setup and interpretation of staining intensity in light of reported colorectal cancer up-regulation (UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for PSMB7 (IHC for PSMB7): expected localisation General nuclear and cytoplasmic staining (HPA tissue IHC), antibody A08095-1, validated IHC image, and IHC protocol steps
Printable PSMB7 IHC protocol sheet — expected localisation General nuclear and cytoplasmic staining (HPA tissue IHC), antibody A08095-1, controls and protocol steps. Open the full PSMB7 IHC guide →

PSMB7 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation General nuclear and cytoplasmic staining (HPA tissue IHC)
Staining pattern High nuclear and cytoplasmic staining in glandular cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A08095-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep paraffin-section fixation consistent across samples. (standard IHC practice; not target-specific)
Caveat Broad expression limits negative-tissue control choices (HPA tissue IHC)
Regulation Up-regulated in colorectal cancer (UniProt)
Isoform / epitope 2 isoforms; mature chain starts at residue 44; verify epitope (UniProt)
Section 1

Recommended PSMB7 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet: A08095-1) is accompanied by published PSMB7 staining protocols for human tumour cell slides (PMC2816652) and lung paraffin sections (PMC12401020).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded mouse brain tissue; fixative not specified (datasheet A08095-1)
FixationImage fixative and duration unreported (datasheet A08095-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A08095-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A08095-1)
Primary antibodyRabbit anti-PSMB7, 2-5 μg/ml (datasheet A08095-1)
Primary incubationOvernight at 4 °C (datasheet A08095-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A08095-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultPSMB7-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General nuclear and cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 for the catalog antibody (datasheet: A08095-1). The lung section protocol does not specify retrieval conditions (PMC12401020).
Section 2

What Is the Expected PSMB7 Staining Pattern?

PSMB7 is a soluble proteasome subunit with no transmembrane segment (UniProt Q99436 topology). Expect nuclear and cytoplasmic staining across many cell types (HPA tissue IHC: general nuclear and cytoplasmic expression). High staining is reported in glandular cells, respiratory epithelium and neurons in the listed tissues (HPA tissue IHC: High). Treat the pattern as a guide rather than an absolute rule because tissue IHC reliability is Supported, with medium consistency against RNA data (HPA tissue IHC: reliability).

What am I looking at on my slide?
Nuclear and cytoplasmic chromogen appears in glandular cells of breast, adrenal gland, cervix, endometrium or colon (HPA tissue IHC: High).This matches the reported tissue pattern and UniProt localisation (HPA tissue IHC: general nuclear and cytoplasmic expression; UniProt Q99436: nucleus, cytoplasm). Compare the distribution with nearby cells rather than requiring identical intensity in every cell (general IHC practice).
Signal is confined to a membrane or extracellular material, with little convincing intracellular staining (UniProt Q99436 topology: no transmembrane segment).That distribution conflicts with the reported nuclear and cytoplasmic localisation (HPA tissue IHC; UniProt Q99436). Check morphology, the detection controls and a known positive section before interpreting it as PSMB7 (general IHC practice).
Strong staining occurs mainly in an unexpected cell population while the expected cells are weak or unstained (HPA tissue IHC: listed High cell populations).Consider cross-reactivity or endogenous detection activity (general IHC practice). HPA reports Low staining in lung alveolar type II cells, splenic white-pulp cells and lymph-node non-germinal-center cells; Low is not an absence claim (HPA tissue IHC: Low).
Pale chromogen covers tissue structures evenly and obscures nuclear and cytoplasmic boundaries (HPA tissue IHC: expected general pattern).Treat this as background until controls show a cellular pattern (general IHC practice). Excess primary antibody, incomplete blocking or residual detection reagents can contribute to background; the supplied sources do not identify a PSMB7-specific cause (general IHC practice).
A section from a listed High tissue has no interpretable signal in its listed cell population (HPA tissue IHC: High).First check tissue preservation, retrieval and assay controls (general IHC practice). A negative result alone does not establish absent PSMB7: HPA rates tissue IHC as Supported with medium antibody–RNA consistency (HPA tissue IHC: reliability).
💡Expected PSMB7 appearanceCall a result consistent when glandular, respiratory epithelial or neuronal cells show clear intracellular nuclear and cytoplasmic staining in a listed High tissue (HPA tissue IHC: High; general pattern); structureless haze or isolated extracellular signal is suspect (general IHC practice; UniProt Q99436 topology).
How each factor affects the staining
Intracellular location and topology (UniProt Q99436)PSMB7 is reported in cytoplasm and nucleus and has no transmembrane segment (UniProt Q99436). Score intracellular staining by compartment; membrane-only staining needs control review (general IHC practice).
Maturation and epitope uncertainty (UniProt Q99436)The 277-residue precursor has a propeptide at residues 1–43 and a mature chain at 44–277 (UniProt Q99436). The supplied record does not locate the antibody epitope, so it cannot predict whether processing affects its IHC signal.
Isoforms (UniProt Q99436)Two isoforms are listed (UniProt Q99436). Their tissue distribution and recognition by the IHC antibody are not specified; do not infer isoform identity from staining intensity or compartment.
Tissue evidence and validation (HPA tissue IHC; HPA antibodies)HPA reports low tissue RNA specificity and Supported tissue IHC with medium antibody–RNA consistency (HPA tissue IHC). HPA052408 has Supported IHC status; the supplied record does not establish that every catalog antibody reproduces it (HPA antibodies).
IF/ICC Q: Where should signal appear?A: Mainly in the nucleoplasm, with supported additional nuclear-body and cytosolic localisation (HPA subcellular ICC-IF). Primary-cilium localisation is uncertain (HPA subcellular ICC-IF). This IF observation does not set an IHC scoring requirement.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in a listed High cell population (HPA tissue IHC: High).The section or detection run may have failed (general IHC practice); this result does not establish target absence.Review tissue morphology, retrieval conditions and a concurrent positive control; repeat with the IHC-validated antibody if the run is invalid (general IHC practice).
Only broad, weak staining appears across the section (HPA tissue IHC: expected nuclear and cytoplasmic pattern).Nonspecific background or excess detection signal may obscure cell boundaries (general IHC practice).Compare with a no-primary control, then adjust antibody dilution, blocking or washing according to the assay controls (general IHC practice).
Strong chromogen appears in a no-primary control (general IHC practice).Endogenous detection activity or nonspecific secondary-system signal is possible (general IHC practice).Address the detection-system background and repeat controls before assigning positive cells (general IHC practice).
Signal appears only at cell borders or outside cells (UniProt Q99436 topology: no transmembrane segment).The pattern conflicts with reported intracellular localisation (HPA tissue IHC; UniProt Q99436).Inspect morphology and controls, and reassess whether nuclear or cytoplasmic signal is present (general IHC practice).
The strongest signal is in cells other than the listed High populations (HPA tissue IHC: High).Cross-reactivity is possible (general IHC practice), but the HPA list does not define every positive cell type (HPA tissue IHC).Compare a listed High tissue, a no-primary control and the cell morphology before calling the unexpected population positive (general IHC practice).
A Low population stains faintly, such as lung alveolar type II cells (HPA tissue IHC: Low).Low denotes reported staining level, not a required negative control (HPA tissue IHC: Low).Judge the faint signal against background and nearby cells; do not use this population alone to declare assay specificity or failure (general IHC practice).

Sample controls for PSMB7 IHC & IF

🧪Run cerebral cortex first and score neuronal cells, which HPA rates High for PSMB7 (HPA: cerebral cortex, neuronal cells, High). HPA detects PSMB7 in all 45 scored tissues, so there is no HPA-supported negative tissue; no cell type on the positive slide is established as target-negative, and cells without specific staining should show only counterstain or background (HPA: no negative rows; detected in all 45 scored tissues).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: None in HPA: PSMB7 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show PSMB7 in HeLa, MCF-7, U2OS, ASC52telo, RPTEC/TERT1, hTERT-RPE1 (serum starved), HEK293, NIH 3T3, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Run a no-primary, secondary-only control and a concentration-matched rabbit IgG isotype control; use PSMB7 knockout material as a biological negative if available (standard IHC practice; selected-SKU caption: rabbit primary antibody). Quench endogenous peroxidase and inspect the cerebral cortex for pigment that could be mistaken for DAB signal (standard chromogenic IHC practice; HPA: cerebral cortex).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected-SKU paraffin-section caption does not state a fixative (selected-SKU tissue-IHC caption: fixative not stated). The demonstrated chromogenic workflow uses heat retrieval in EDTA at pH 8.0, but the caption does not establish whether retrieval is essential (selected-SKU tissue-IHC caption). Frozen sections are not documented here, and HPA ICC-IF images support intracellular localisation without showing that IF is easier than paraffin IHC (HPA: subcellular ICC-IF images; selected-SKU tissue-IHC caption).

HPA tissue IHC evidence for PSMB7

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Cerebellum Cells in molecular layer High Protein (IHC) HPA →
Cerebral cortex Neuronal cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: PSMB7 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced PSMB7 IHC Tips

Troubleshoot PSMB7 staining in paraffin sections by checking retrieval, compartment pattern, background controls and how viable cells are scored.

What retrieval should I use when PSMB7 staining is weak in paraffin sections?
Start with heat-mediated EDTA at pH 8.0 for PSMB7 staining in paraffin sections (datasheet A08095-1). The documented image used 2 μg/ml primary antibody overnight at 4°C, so keep those conditions fixed while assessing retrieval (caption A08095-1). Compare sections processed together, including a positive tissue section and a primary-antibody omission control, to distinguish weak antigen exposure from detection background (standard IHC practice). If signal remains weak, adjust heating duration in small increments and watch for tissue damage (standard IHC practice). Record the retrieval conditions for every staining run before comparing intensity across samples (standard IHC practice).
Could fixation explain inconsistent PSMB7 staining between paraffin blocks?
Target-specific sensitivity of PSMB7 to fixation is unknown from the supplied evidence; the selected paraffin-section image does not state its fixative (caption A08095-1). Treat fixation history as a variable when staining differs between blocks, and compare sections with documented, matched processing where possible (standard IHC practice). Overfixation or uneven fixation can change antigen accessibility in IHC generally, but neither effect has been demonstrated specifically for PSMB7 here (standard IHC practice). Keep retrieval and antibody conditions constant while checking block history and tissue preservation (standard IHC practice). Interpret a negative result cautiously when the fixation history is missing or inconsistent (standard IHC practice).
Should PSMB7 staining appear in nuclei, cytoplasm, or both?
Assess both nuclear and cytoplasmic staining in paraffin sections: PSMB7 is reported in the nucleus and cytoplasm (UniProt Q99436), and tissue IHC shows a general nuclear and cytoplasmic pattern (HPA tissue IHC). A nuclear-dominant pattern can also be plausible because the nucleoplasm is the main supported location in subcellular imaging (HPA subcellular). Score the compartments separately rather than treating a shift between them as an automatic staining failure (standard IHC practice). PSMB7 can translocate from cytoplasm to nucleus after interaction with AKIRIN2, which links it to nuclear import through IPO9 (UniProt Q99436). Compare the pattern with matched tissue morphology and staining controls before assigning biological meaning (standard IHC practice).
How could PSMB7 processing affect epitope interpretation in tissue sections?
PSMB7 has 2 annotated isoforms, but the supplied antibody caption does not identify their relative recognition (UniProt Q99436; caption A08095-1). Its precursor contains a propeptide at residues 1–43, whereas the annotated mature chain spans residues 44–277 (UniProt Q99436). Check the antibody's stated immunogen or epitope before claiming that staining reports the mature chain, precursor, or both (standard IHC practice). No transmembrane segment or glycosylation site is annotated, so a membrane-only interpretation needs independent support (UniProt Q99436). If staining changes after retrieval adjustment, confirm the pattern with appropriate tissue controls rather than assigning the change to an isoform (standard IHC practice).
How should I cross-check a PSMB7 IHC pattern with multiplex IF?
Use IF/ICC as a separate cross-check of the paraffin-section IHC pattern, rather than treating its staining conditions as the IHC protocol (standard IHC/IF practice). Pair PSMB7 with a marker for the expected cell population, such as a neuronal marker when examining cerebral cortex, where neuronal staining is reported as high (HPA tissue IHC). Choose spectrally separated fluorophores and assess tissue autofluorescence before interpreting weak signal, particularly when selecting the PSMB7 channel (standard IF practice). Permeabilise for access to nuclear and cytosolic epitopes; PSMB7 has no annotated transmembrane segment (UniProt Q99436; standard IF practice). Fixation sensitivity and an IF dilution are not established by the supplied evidence (caption A08095-1).
How can I separate diffuse PSMB7 staining from chromogenic background?
The documented paraffin-section image used 10% goat serum blocking, a peroxidase-conjugated secondary antibody and DAB detection (caption A08095-1). For troubleshooting, compare a primary-antibody omission control with the stained section and include a peroxidase block before chromogen development (standard IHC practice). If both sections develop color, inspect endogenous peroxidase activity, secondary-antibody binding and residual chromogen before attributing the signal to PSMB7 (standard IHC practice). Evaluate staining within preserved cells rather than in folds, damaged edges or acellular deposits (standard IHC practice). Retain the same exposure to DAB across comparison sections so differences in development do not masquerade as expression differences (standard IHC practice).
What is a defensible way to quantify PSMB7 IHC staining? ⚠ ANSWER MARKED FOR VERIFICATION
Score PSMB7 separately in nuclei and cytoplasm because both compartments are supported locations (UniProt Q99436; HPA tissue IHC). For a defined cell population, record the percentage of positive viable cells and an intensity-based H-score on a 0–300 scale, using the same scoring thresholds across slides (standard IHC practice). If counting positive cells per mm², report the analyzed viable tissue area and the population being counted (standard IHC practice). Normalize comparisons to the number of eligible cells or viable tissue area, rather than to the entire section including empty space (standard IHC practice). Keep retrieval, detection and scoring rules matched across groups (standard IHC practice).
When is an apparent PSMB7-positive cell likely to be an artefact?
Give greatest weight to staining within intact nuclei or cytoplasm, the reported PSMB7 compartments (UniProt Q99436; HPA tissue IHC). The HPA reports high staining in cerebral-cortex neuronal cells and colon glandular cells, providing examples of cell populations in which a positive pattern is plausible (HPA tissue IHC). Be cautious about signal confined to tissue edges, necrotic areas or extracellular deposits, which can reflect section or detection artefacts (standard IHC practice). Color in a primary-antibody omission control suggests detection background, including endogenous peroxidase, rather than specific PSMB7 staining (standard IHC practice). Interpret intensity alongside morphology and controls because tissue-IHC reliability is rated Supported with medium staining–RNA consistency (HPA tissue IHC).
Boster reagents

Best PSMB7 / Proteasome subunit beta type-7 IHC Antibodies

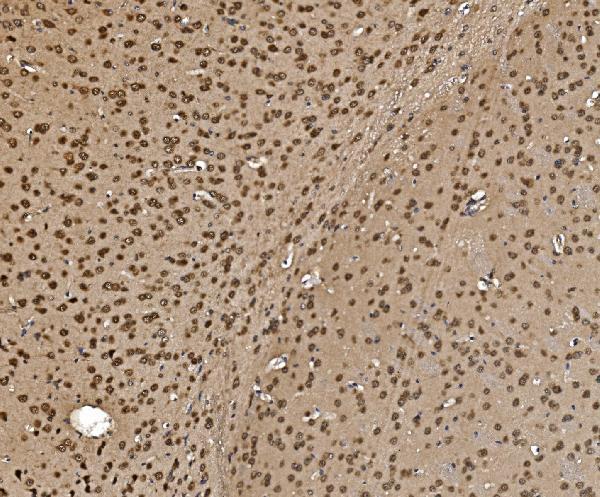
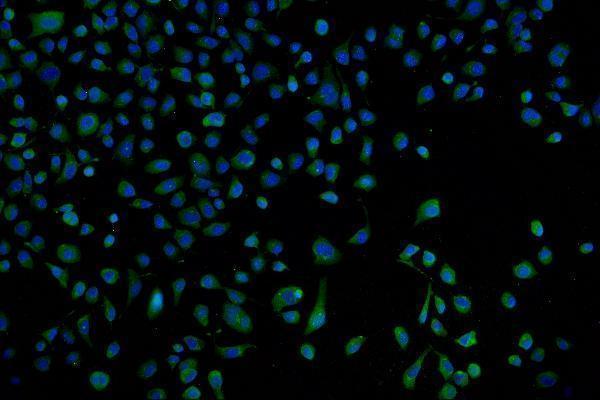
A08095-1 has IHC images from paraffin sections of mouse and rat brain and two human tissue types, plus IF/ICC data from HeLa cells (catalog image captions).

Real IHC data IHC analysis of Proteasome 20S Beta 7/PSMB7 using anti-Proteasome 20S Beta 7/PSMB7 antibody (A08095-1). Proteasome 20S Beta 7/PSMB7 was detected in a paraffin-embedded section of mouse brain tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-Proteasome 20S Beta 7/PSMB7 Antibody (A08095-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-Proteasome 20S beta 7/PSMB7 Antibody ®
Cat # A08095-1

A08095-1 has IHC images from mouse and rat brain, human renal clear cell carcinoma, and human cervical intraepithelial neoplasia, all in paraffin sections (catalog IHC image captions). The same SKU has an IF/ICC image from HeLa cells and lists human, mouse, and rat reactivity (catalog IF image caption; catalog reactivity).

Which to pick: Choose A08095-1 for paraffin-section IHC: its own image captions document staining in mouse, rat, and human tissue (catalog IHC image captions); the fixative is unreported (catalog IHC image captions). Choose A08095-1 for IF/ICC when working with HeLa cells, which appear in its IF image; IF and ICC are listed applications (catalog IF image caption; catalog applications). It is also the listed cross-species choice for human, mouse, and rat, although its clonality is unreported (catalog reactivity; catalog clone field).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q99436 (PSB7_HUMAN, Proteasome subunit beta type-7).
  2. Human Protein Atlas. PSMB7 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. PSMB7 subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to the nuclear bodies, cytosol and primary cilium..
  4. Human Protein Atlas. PSMB7 antibody validation summary (2 antibodies).
  5. Ubiquitination and degradation of CD47 enhances macrophage phagocytosis of hemolytic erythrocytes. iScience 2026 — PMC12818076.
  6. PSMB7 is associated with anthracycline resistance and is a prognostic biomarker in breast cancer. British journal of cancer 2010 — PMC2816652.
  7. Identification and validation of PSMB7 as a novel biomarker for prognosis and immune infiltrates of lung adenocarcinoma. PeerJ 2025 — PMC12401020.
  8. PubMed PMID:8666937 — UniProt-cited evidence.
  9. PubMed PMID:14702039 — UniProt-cited evidence.
  10. PubMed PMID:15164053 — UniProt-cited evidence.