This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Use nuclear and cytoplasmic staining as the RSRC1 tissue IHC benchmark (HPA tissue IHC). This guide highlights glandular cells with high staining (HPA tissue IHC) and the catalog antibody’s 5 μg/mL IHC starting concentration (datasheet: A12655).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclear and cytoplasmic tissue staining (HPA tissue IHC) | |
| Staining pattern | Nuclear and cytoplasmic staining; high in glandular cells (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen) | |
| Positive control | Duodenum+4 more · see all | |
| Negative control | Adipose tissue |
| Fixation | Keep fixation consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Staining and RNA show medium consistency (HPA tissue IHC) | |
| Regulation | Widely expressed; regulation unreported (UniProt) | |
| Isoform / epitope | 2 isoforms; verify antibody epitope coverage (UniProt) |
This section pairs the catalog antibody’s IHC-P protocol with one published RSRC1 staining method (PMC6625388).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A12655); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-RSRC1, 5 μg/mL (datasheet A12655) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | RSRC1-positive staining in glandular cells of duodenum (HPA tissue IHC: High). HPA tissue profile: Nuclear and cytoplasmic expression in all tissues. No signal in the no-primary control. |
RSRC1 is nuclear, including nuclear speckles, and can also be cytoplasmic (UniProt Q96IZ7; HPA tissue IHC; HPA ICC-IF). Expect staining across many cell types, with strong examples in glandular cells of duodenum, fallopian tube and gallbladder, and in testicular spermatogonia (HPA: High). HPA rates tissue IHC as Supported, with medium consistency between staining and RNA data (HPA tissue IHC). RSRC1 has no transmembrane segment (UniProt Q96IZ7 topology).
| Nuclear and cytoplasmic chromogen in glandular cells of duodenum, fallopian tube or gallbladder. | This fits the reported distribution and strong cell examples (HPA tissue IHC: nuclear and cytoplasmic; HPA: High in these glandular cells). Judge localisation within identifiable cells, because broad tissue expression does not mean every cell must stain equally (HPA: low tissue specificity; general IHC interpretation). |
| A crisp nuclear-speckle pattern, with or without detectable cytoplasmic staining. | Nuclear speckles are the approved ICC-IF location (HPA subcellular ICC-IF). UniProt also places RSRC1 in the nucleus and cytoplasm and describes shuttling (UniProt Q96IZ7). The speckle finding helps assess localisation, but an IHC section need not resolve discrete speckles as clearly as ICC-IF (general microscopy practice). |
| Predominantly cell-surface or extracellular staining, without a credible nuclear component. | That compartment is discordant with the reported nuclear and cytoplasmic pattern (HPA tissue IHC; UniProt Q96IZ7) and the absence of a transmembrane segment (UniProt Q96IZ7 topology). Treat it as a possible artefact; inspect morphology and detection controls before assigning RSRC1 localisation (general IHC practice). |
| Strong signal confined to adipocytes while expected positive cells remain blank. | Adipocytes are listed as Not detected, whereas several glandular populations and spermatogonia are High (HPA tissue IHC). This reversal raises cross-reactivity or endogenous detection activity as possibilities, not a diagnosis; compare an appropriate negative control and a known-positive section (general IHC practice). |
| Diffuse colour obscures cell boundaries, or no signal appears in a known-positive section. | Diffuse background cannot establish the reported intracellular localisation (HPA tissue IHC; general IHC interpretation). A blank known-positive section leaves the run uninterpretable: check the staining controls and workflow before inferring absent RSRC1, since HPA documents High staining in specified cells (HPA tissue IHC; general IHC practice). |
| Tissue and cell selection | Use the named High populations to assess an IHC run; hepatocytes and breast glandular cells are Low, and adipocytes are Not detected (HPA tissue IHC). A weak result in a Low population is therefore less informative than a failed High-cell control (HPA tissue IHC; general IHC interpretation). |
| Validation scope | HPA rates tissue IHC Supported and reports medium consistency with RNA; HPA044792 is Supported for IHC and Approved for ICC (HPA tissue IHC; HPA antibodies). These ratings support pattern assessment, but do not establish fixation sensitivity, retrieval conditions or performance for another antibody (HPA validation scope). |
| Isoforms and epitope coverage | Two isoforms are listed (UniProt Q96IZ7). Their listing alone does not show which isoforms an antibody detects; consult the chosen antibody's documented epitope before attributing a staining difference to isoforms (UniProt Q96IZ7; general antibody interpretation). |
| IF/ICC Q: What localisation should an image show? | A: Nuclear speckles are the approved main location (HPA subcellular ICC-IF). This answers localisation only; the separate IF/ICC guide should supply its own staining workflow (HPA subcellular ICC-IF; application scope). |
| Situation | Likely cause | Next action |
|---|---|---|
| Known-positive glandular cells show no chromogen. | A failed staining run is possible; those cells are reported High (HPA tissue IHC). | Confirm tissue identity and cell preservation, then check the positive control, primary-antibody step, retrieval and detection reagents according to the assay workflow (general IHC practice). Do not assign an RSRC1-specific fixation or retrieval cause from these sources (HPA/UniProt evidence scope). |
| Signal is faint in liver hepatocytes or breast glandular cells. | Both populations are listed Low (HPA tissue IHC). | Compare a named High-cell section processed in the same run before changing assay conditions (HPA tissue IHC; general IHC practice). Score the relevant cells rather than treating a weak Low-cell result alone as a failed antibody (general IHC interpretation). |
| Brown deposit appears mainly at cell borders or outside cells. | This distribution conflicts with nuclear and cytoplasmic RSRC1 and its lack of a transmembrane segment (HPA tissue IHC; UniProt Q96IZ7 topology). | Inspect tissue morphology and a primary-omission control, then review washing and detection steps (general IHC practice). Require intracellular signal in the expected cells before calling it specific (HPA tissue IHC; general IHC interpretation). |
| Adipocytes stain strongly. | HPA lists adipocytes as Not detected; cross-reactivity or endogenous detection activity is possible (HPA tissue IHC; general IHC practice). | Compare a primary-omission control and a named High-cell positive section; review detection blocking as appropriate for the chemistry used (general IHC practice). Avoid using adipocyte colour alone to score RSRC1 (HPA tissue IHC). |
| Background makes nuclear and cytoplasmic staining hard to judge. | Nonspecific binding or detection background may obscure cell-level localisation (general IHC practice). | Review blocking, primary-antibody dilution, washing and counterstain against the assay instructions; compare controls before adjusting one condition at a time (general IHC practice). No RSRC1-specific dilution or background mechanism is supplied (HPA/UniProt evidence scope). |
| The IHC result lacks visibly discrete nuclear speckles. | HPA's approved speckle assignment comes from ICC-IF, while tissue IHC is described as nuclear and cytoplasmic (HPA subcellular ICC-IF; HPA tissue IHC). | Assess the IHC section against its tissue-level nuclear and cytoplasmic pattern and cell identity; use the separate IF/ICC guide when discrete speckle imaging is the goal (HPA tissue IHC; HPA subcellular ICC-IF; general microscopy practice). |
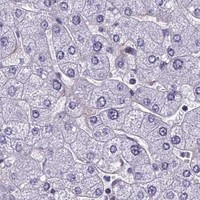


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Duodenum | Glandular cells | High | Protein (IHC) | HPA → |
| Fallopian tube | Glandular cells | High | Protein (IHC) | HPA → |
| Gallbladder | Glandular cells | High | Protein (IHC) | HPA → |
| Parathyroid gland | Glandular cells | High | Protein (IHC) | HPA → |
| Testis | Spermatogonia cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
Troubleshoot RSRC1 chromogenic IHC by checking retrieval, compartment-specific staining, cell identity, and controls before interpreting signal intensity.
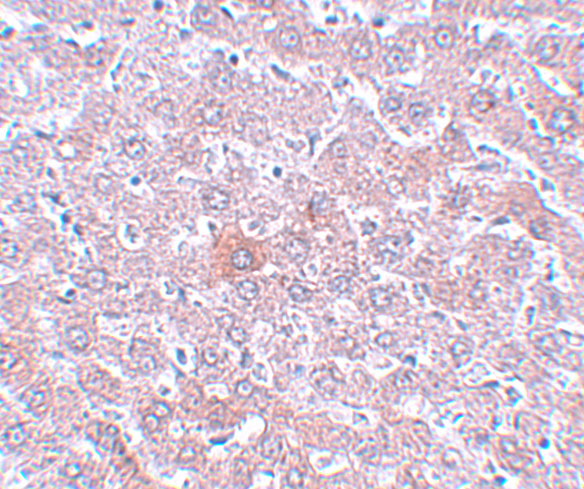
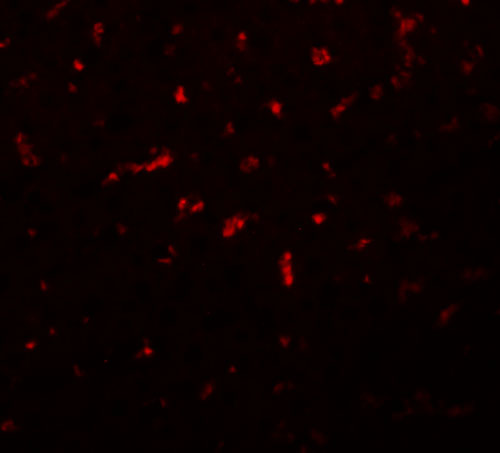
A12655 has rat liver IHC and IF images (catalog image captions). Human, mouse and rat reactivity is listed; the pictured tissue is rat liver (catalog reactivity; image captions).
A12655 will render with its rat liver IHC image at 5 μg/mL (IHC image caption). Its IF image shows rat liver at 20 μg/mL; human, mouse and rat reactivity is listed (IF image caption; catalog reactivity).
Which to pick: For paraffin-section IHC, choose A12655: IHC-P is listed and its own IHC image shows rat liver at 5 μg/mL; the fixative is unreported (catalog applications; IHC image caption). For IF, A12655 has a rat liver image at 20 μg/mL; ICC validation is unreported (IF image caption; catalog applications). For work across species, A12655 lists human, mouse and rat reactivity, while the supplied IHC and IF images document rat liver only; its host is rabbit, and clonality is unreported (catalog reactivity; image captions; catalog host and clone fields).