SIAE / Sialate O-acetylesterase · IHC design guide

Design Immunohistochemistry for SIAE

Plan SIAE staining in paraffin sections using the IHC-validated antibody, with cytoplasmic staining as the tissue pattern to assess (HPA tissue IHC). Compare suitable positive and negative cell populations, and interpret intensity cautiously because antibody staining has low consistency with RNA expression (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for SIAE (IHC for SIAE): expected localisation Cytoplasmic staining (HPA tissue IHC), antibody A08046, validated IHC image, and IHC protocol steps
Printable SIAE IHC protocol sheet — expected localisation Cytoplasmic staining (HPA tissue IHC), antibody A08046, controls and protocol steps. Open the full SIAE IHC guide →

SIAE Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining (HPA tissue IHC)
Staining pattern Cytoplasmic staining in glandular, tubular and hematopoietic cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A08046)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Duodenum+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A08046)
Caveat Staining has low consistency with RNA; verify independently (HPA tissue IHC)
Regulation No specific expression regulator reported (UniProt)
Isoform / epitope 2 isoforms; signal peptide 1–23; epitope coverage unknown (UniProt)
Section 1

Recommended SIAE IHC & IF Protocols

The catalog antibody’s IHC-P protocol and a published SIAE IHC protocol for human intestinal biopsies (PMC12011031) provide starting conditions for paraffin sections.

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human glioblastoma tissue; fixative not specified (datasheet A08046)
FixationImage fixative and duration unreported (datasheet A08046); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A08046); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A08046)
Primary antibodyRabbit anti-SIAE, 2-5 μg/ml (datasheet A08046)
Primary incubationOvernight at 4 °C (datasheet A08046)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A08046)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultSIAE-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in several tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet: A08046); the published protocol used citrate pH 6.0 (PMC12011031).
Section 2

What Is the Expected SIAE Staining Pattern?

SIAE is annotated in lysosomes and cytoplasm, with no transmembrane segment (UniProt Q9HAT2). In paraffin IHC, expect cytoplasmic staining in selected cells, including kidney tubule cells and adrenal glandular cells (HPA: High). HPA calls its tissue pattern “Approved” but reports low consistency between antibody staining and RNA expression, pending external verification (HPA tissue IHC).

What am I looking at on my slide?
Cytoplasmic signal in kidney tubule cells or adrenal glandular cells, with little signal in adjacent unstained structures.Fits the reported compartment and two High cell populations (UniProt Q9HAT2; HPA tissue IHC). A punctate component may be consistent with lysosomes, but HPA tissue IHC describes the pattern broadly as cytoplasmic (UniProt Q9HAT2; HPA tissue IHC).
Predominantly nuclear or sharply cell-surface staining, without a convincing cytoplasmic component.This is discordant with the annotated lysosomal and cytoplasmic locations and lack of a transmembrane segment (UniProt Q9HAT2). Treat it as a possible artefact and check controls before assigning it to SIAE (general IHC practice).
Strong staining in a cell population listed as Not detected, such as duodenal glandular cells or cardiomyocytes.That conflicts with the reported staining for those specific cells (HPA tissue IHC). Consider cross-reactivity or endogenous detection activity; a tissue label alone cannot identify which cell population produced the signal (general IHC practice).
Uniform brown haze across many cell types, extracellular spaces, and the negative control.A widespread signal without cell or compartment selectivity is difficult to reconcile with HPA’s cell-specific observations (HPA tissue IHC). Background from detection chemistry or inadequate blocking is possible (general IHC practice).
No signal in kidney tubule cells or adrenal glandular cells that are present and interpretable on the section.These are reported High cell populations, so a blank result warrants a technical check (HPA tissue IHC). HPA’s low staining–RNA consistency also means that one absent result cannot by itself settle SIAE expression (HPA tissue IHC).
💡Expected SIAE appearanceCall a positive result when the IHC-validated antibody gives selective cytoplasmic staining in an HPA High cell population, such as kidney tubule cells or adrenal glandular cells; dominant nuclear, cell-surface, or uniform tissue-wide staining is suspect (UniProt Q9HAT2; HPA tissue IHC; general IHC practice).
How each factor affects the staining
Cell population used for interpretationHPA reports High staining in kidney tubule cells, adrenal glandular cells, bone marrow hematopoietic cells, and several other specified populations; it reports Not detected for particular cells in other tissues (HPA tissue IHC). Score the identified cells, since a whole-tissue positive or negative label loses that distinction (general IHC practice).
Antibody validation and agreementHPA038052 and HPA038053 are rabbit polyclonal antibodies marked IHC Approved, while the tissue profile has low consistency with RNA and awaits external verification (HPA antibodies; HPA tissue IHC). Approval supports use of the reported pattern as a reference, with this explicit limitation (HPA tissue IHC).
Protein location and topologyUniProt lists lysosome and cytoplasm and no transmembrane segment (UniProt Q9HAT2). This supports cytoplasmic interpretation; it does not make an isolated plasma-membrane outline an expected result (UniProt Q9HAT2 topology).
Processing, glycosylation, and isoformsUniProt annotates a 1–23 signal peptide, a 24–523 chain, six glycosylation sites, and two isoforms (UniProt Q9HAT2). Their effects on the catalog antibody’s epitope and paraffin-section staining are unreported in the supplied evidence.
Antigen retrieval and fixationRetrieval conditions should be established with the IHC-validated antibody and a positive control (general IHC practice). No SIAE-specific retrieval requirement or fixation sensitivity is established by the supplied UniProt and HPA records.
Q: Can IF/ICC confirm the compartment?A: HPA supplies no main ICC-IF location and no cell-line ICC-IF images for SIAE (HPA subcellular). Use this section’s compartment call as an IHC interpretation informed by UniProt, without treating it as an HPA-confirmed IF pattern (UniProt Q9HAT2; HPA subcellular).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The positive-control section is blank.Section, primary-antibody, retrieval, or detection failure is possible (general IHC practice).Check that the expected cells are present, then review the catalog antibody’s IHC-P instructions and verify retrieval and detection with an interpretable control (general IHC practice; HPA: High in kidney tubule cells and adrenal glandular cells).
Signal is predominantly nuclear or outlines cell membranes.The compartment conflicts with lysosomal and cytoplasmic annotation and no transmembrane segment (UniProt Q9HAT2).Compare the primary-omission control and repeat staining with the IHC-validated antibody under its documented IHC-P conditions; withhold a SIAE call if the discordance persists (general IHC practice).
Strong staining appears in duodenal glandular cells or cardiomyocytes.These specific populations are reported Not detected (HPA tissue IHC); cross-reactivity or endogenous detection activity is possible (general IHC practice).Confirm cell identity on the counterstain, inspect a primary-omission control, and review endogenous enzyme blocking for chromogenic detection (general IHC practice).
Brown signal covers most structures, including the negative control.Detection background, endogenous enzyme activity, or insufficient blocking is possible (general IHC practice).Review blocking and detection controls, then assess whether signal becomes selective for reported cell populations and the cytoplasm (general IHC practice; HPA tissue IHC; UniProt Q9HAT2).
Only scattered cells stain in a tissue expected to be positive.The observed HPA levels refer to named cell populations, so sampling or cell identification may explain an apparent mismatch (HPA tissue IHC; general IHC practice).Identify the relevant cells on the counterstain and score those cells separately; record the distribution before interpreting overall tissue intensity (general IHC practice).
Two IHC runs or antibodies give conflicting tissue patterns.HPA reports low consistency between staining and RNA, pending external verification; both listed antibodies have IHC Approved status (HPA tissue IHC; HPA antibodies).Compare the same cell populations, compartment, and controls across runs. Report the disagreement rather than resolving it from RNA levels or an HPA tissue label alone (general IHC practice; HPA tissue IHC).

Sample controls for SIAE IHC & IF

🧪Run kidney first: tubular cells should stain (HPA: High in kidney tubular cells); use heart muscle as a negative tissue, where cardiomyocytes are not detected (HPA: Not detected in cardiomyocytes). On the kidney slide, use neighboring non-tubular areas to judge background, without assuming those cells are SIAE-negative (HPA: kidney result specifies tubular cells).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Duodenum (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for SIAE; derive a cell-line control from the positive tissue's cell type (Glandular cells) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control, a concentration-matched rabbit IgG isotype control, and, if available, a SIAE-knockout section or immunizing-peptide block (A08046 caption: rabbit primary; standard IHC practice). Quench endogenous peroxidase for DAB detection and block endogenous biotin if using an avidin–biotin system, particularly in kidney (A08046 caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected A08046 paraffin-section caption does not state a fixative (A08046 caption: fixative unreported). Heat retrieval in EDTA at pH 8.0 is a documented starting condition; whether retrieval is essential has not been established by the supplied evidence (A08046 caption: heat-mediated EDTA retrieval). The supplied evidence does not establish frozen sections or IF/ICC as easier; HPA lists no ICC-IF images, while kidney can produce endogenous biotin background with avidin–biotin detection (HPA subcellular: no ICC-IF images; standard IHC practice).

HPA tissue IHC evidence for SIAE

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Cerebellum Cells in molecular layer High Protein (IHC) HPA →
Epididymis Glandular cells High Protein (IHC) HPA →
Kidney Cells in tubules High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Duodenum Glandular cells Not detected Protein (IHC) HPA →
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Lymph node Germinal center cells Not detected Protein (IHC) HPA →
Oral mucosa Squamous epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced SIAE IHC Tips

Troubleshoot SIAE staining in paraffin sections by checking retrieval, compartment, cell identity and controls before comparing signal across samples (UniProt Q9HAT2; HPA tissue IHC).

How should I optimize retrieval when SIAE staining is weak?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A08046). The selected SIAE tissue image used this retrieval with 2 μg/ml primary antibody overnight at 4°C, so retain those conditions while diagnosing weak staining (datasheet A08046). Check that sections are fully deparaffinized, then compare retrieval duration on adjacent sections while holding antibody concentration and DAB development constant (standard IHC practice). If staining remains weak, test a different retrieval buffer only as a documented fallback, alongside the EDTA reference condition (standard IHC practice). Assess improvement in cell-associated cytoplasmic staining, consistent with reported localisation, rather than in diffuse background alone (UniProt Q9HAT2 localisation; HPA tissue IHC).
Could fixation explain variable SIAE staining between sections?
The selected tissue caption identifies a paraffin-embedded section but does not report its fixative, so SIAE-specific fixation sensitivity is unknown (datasheet A08046). Record the actual fixative and fixation interval for each specimen before attributing a weak result to the antigen (standard IHC practice). Compare adjacent sections with matched thickness, EDTA retrieval at pH 8.0, and identical detection settings to isolate processing differences (datasheet A08046; standard IHC practice). Include a control section with reproducible cell-associated staining in every run, and inspect morphology for processing damage (standard IHC practice). Do not infer fixation tolerance from SIAE localisation, glycosylation sites or the HPA staining profile (UniProt Q9HAT2; HPA tissue IHC).
Where should convincing SIAE staining appear in tissue sections?
Expect a cell-associated cytoplasmic pattern, potentially with puncta, because SIAE is annotated in the cytoplasm and lysosome (UniProt Q9HAT2 localisation; HPA tissue IHC). Its record lists no transmembrane segment, so a crisp membrane-only rim needs additional validation before assignment to SIAE (UniProt Q9HAT2 topology). Evaluate localisation within intact cells rather than interpreting extracellular deposits, folds or tissue edges as a compartmental pattern (standard IHC practice). HPA reports high staining in kidney tubule cells and thyroid glandular cells, which can help frame cell-level review without establishing specificity for a new antibody (HPA tissue IHC). Compare serial sections and negative controls using the same pH 8.0 EDTA retrieval before changing the expected pattern (datasheet A08046; standard IHC practice).
Can the two SIAE isoforms explain discordant staining?
SIAE has 2 annotated isoforms, but the supplied antibody caption does not identify its epitope or establish which isoform it detects (UniProt Q9HAT2 isoforms; datasheet A08046). The precursor has a signal peptide at residues 1–23 and a chain at 24–523, which makes epitope position relevant to interpretation (UniProt Q9HAT2 processing). Six glycosylation sites are annotated, but their effect on this antibody's tissue staining has not been established here (UniProt Q9HAT2 glycosylation; datasheet A08046). Request the immunogen or epitope location before proposing an isoform-specific explanation, and compare antibody results with an independent assay when available (standard IHC practice). Keep retrieval and detection matched across sections while investigating a discordant pattern (standard IHC practice).
How can IF help assess an ambiguous chromogenic SIAE pattern?
Use IF as a separate corroborating experiment; the selected antibody evidence documents paraffin-section chromogenic IHC, and the supplied HPA record lists no ICC/IF images (datasheet A08046; HPA subcellular). Multiplex SIAE with a marker for the cell population under study, then inspect whether signal shares those cells and the expected cytoplasmic or lysosomal region (UniProt Q9HAT2 localisation; standard IF practice). Choose fluorophores after checking tissue autofluorescence and include single-colour controls to assess bleed-through (standard IF practice). For an intracellular epitope, assess permeabilisation, while recognizing that this antibody's epitope location is unreported (UniProt Q9HAT2 localisation; datasheet A08046; standard IF practice). IF agreement supports localisation assessment but does not by itself prove antibody specificity in the chromogenic section (standard IHC/IF practice).
What should I check when DAB obscures SIAE-positive cells?
First inspect a no-primary control for signal from secondary detection and a matched negative control for nonspecific staining (standard IHC practice). The selected tissue image used 10% goat serum, a peroxidase-conjugated anti-rabbit secondary and DAB development; treat those as documented image conditions (datasheet A08046). Include a peroxidase block before HRP detection and check whether reducing development time or primary concentration improves cellular contrast (standard IHC practice). Compare tissue edges, folds and damaged regions with intact areas, since concentrated precipitate there can mislead interpretation (standard IHC practice). Score a putative SIAE signal only after background is controlled and its cellular pattern is compatible with cytoplasmic or lysosomal localisation (UniProt Q9HAT2 localisation; standard IHC practice).
How should I quantify SIAE staining across specimens? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and tissue compartment before scoring, since HPA reports different staining levels among cell types within its tissue survey (HPA tissue IHC). For chromogenic sections, record an H-score or the percentage of positive cells within the defined population, using consistent intensity thresholds (standard IHC practice). If spatial burden matters, report positive-cell density per mm² of evaluable tissue and exclude folds, necrosis and missing tissue by a preset rule (standard IHC practice). Normalize comparisons to the same cell type, evaluable area and staining batch, with a common control section to monitor run variation (standard IHC practice). Report retrieval and antibody conditions, including pH 8.0 EDTA when following the selected image method (datasheet A08046).
How do I distinguish genuine SIAE staining from artefact?
A plausible result is cell-associated cytoplasmic staining, possibly punctate, consistent with reported cytoplasmic and lysosomal localisation (UniProt Q9HAT2 localisation; HPA tissue IHC). Question a membrane-only rim or isolated extracellular deposit because the record lists no transmembrane segment and identifies intracellular locations (UniProt Q9HAT2 topology and localisation). Review the stained cell type against the tissue context; HPA reports high kidney tubule staining but no detected staining in skeletal muscle myocytes (HPA tissue IHC). Exclude edge effects, necrotic regions and endogenous peroxidase signal using morphology, a peroxidase block and appropriate controls (standard IHC practice). Interpret agreement with HPA cautiously because its SIAE tissue IHC entry reports low consistency between antibody staining and RNA expression (HPA tissue IHC).
Boster reagents

Best SIAE / Sialate O-acetylesterase IHC Antibodies

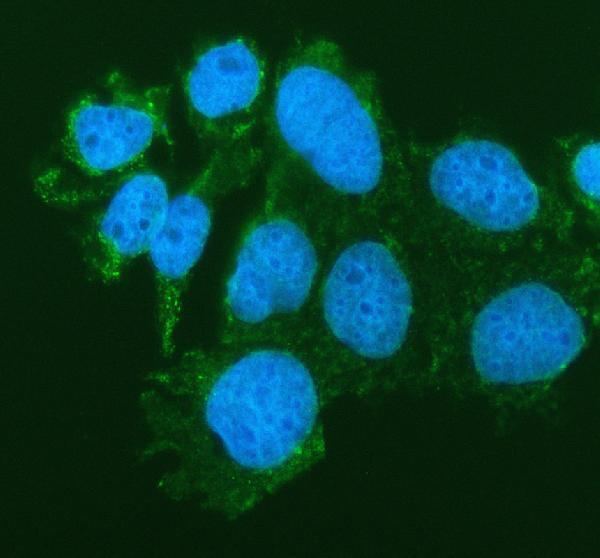
The catalog antibody has IHC images from human paraffin sections and an IF image from CACO-2 cells (catalog captions: A08046); listed species reactivity is human, mouse and rat (catalog: A08046).

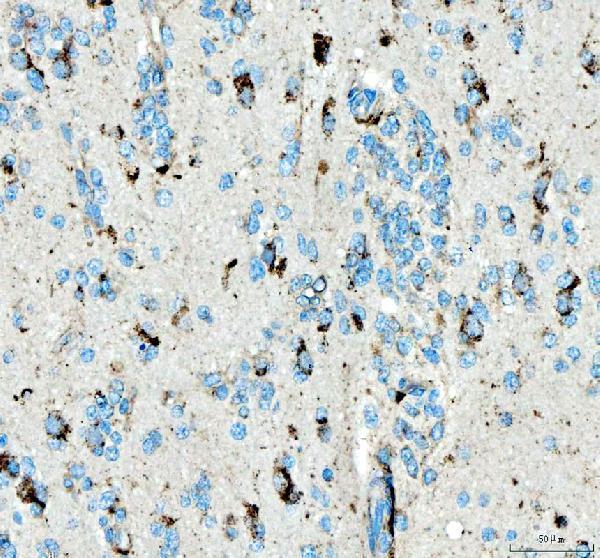
Real IHC data IHC analysis of SIAE using anti-SIAE antibody (A08046). SIAE was detected in a paraffin-embedded section of human glioblastoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-SIAE Antibody (A08046) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-SIAE Antibody ®
Cat # A08046

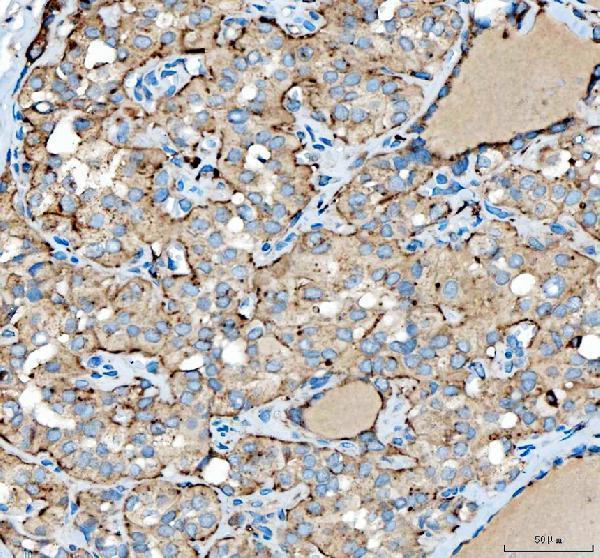
A08046 will render with its own IHC figure from a human paraffin-embedded glioblastoma section (catalog IHC caption: A08046). Its additional IHC caption shows human thyroid papillary carcinoma, and its IF caption shows CACO-2 cells (catalog captions: A08046).

Which to pick: Choose A08046 for paraffin-section IHC: its IHC captions document human glioblastoma and thyroid papillary carcinoma sections; the fixative is unreported (catalog IHC captions: A08046). For IF/ICC, A08046 lists both applications and has an IF image from CACO-2 cells (catalog applications and IF caption: A08046). It lists human, mouse and rat reactivity, but the supplied IHC and IF images document human samples only; clonality is unreported (catalog reactivity, captions and clone field: A08046).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9HAT2 (SIAE_HUMAN, Sialate O-acetylesterase).
  2. Human Protein Atlas. SIAE tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. SIAE subcellular location (ICC-IF): Highest expression in ASC52telo: 85.3 nTPM.
  4. Human Protein Atlas. SIAE antibody validation summary (2 antibodies).
  5. SIAE-Mediated Loss of Sialic Acid Acetylation Contributes to Ulcerative Colitis. Journal of inflammation research 2025 — PMC12011031.
  6. Multiomics elucidation of surrounding AT2 cells impeding tertiary lymphoid structures function in neoadjuvant chemoimmunotherapy response of multiple primary lung cancers. Journal for immunotherapy of cancer 2025 — PMC12516992.
  7. PubMed PMID:15292578 — UniProt-cited evidence.
  8. PubMed PMID:14702039 — UniProt-cited evidence.
  9. PubMed PMID:15489334 — UniProt-cited evidence.