SPTBN4 / Spectrin beta chain, non-erythrocytic 4 · IHC design guide

Design Immunohistochemistry for SPTBN4

Start paraffin-section IHC with catalog antibody A14322 at 1:50 (datasheet A14322). Assess CNS neuronal projections and cerebellar granular cells against adipose adipocytes reported as not detected, while accounting for presumed off-target staining (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for SPTBN4 (IHC for SPTBN4): expected localisation CNS neuronal projections (HPA tissue IHC), antibody A14322, validated IHC image, and IHC protocol steps
Printable SPTBN4 IHC protocol sheet — expected localisation CNS neuronal projections (HPA tissue IHC), antibody A14322, controls and protocol steps. Open the full SPTBN4 IHC guide →

SPTBN4 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation CNS neuronal projections (HPA tissue IHC)
Staining pattern CNS projections; cerebellar granular-cell cytoplasm/membrane (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A14322)
Positive control ⓘ Adrenal gland+3 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep paraffin-section fixation consistent across samples. (standard IHC practice; not target-specific)
Caveat Presumed off-target staining may confound interpretation (HPA tissue IHC)
Regulation Staining intensity varies by tissue (HPA tissue IHC)
Isoform / epitope 5 isoforms; epitope coverage is unspecified (UniProt)
Section 1

Recommended SPTBN4 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is accompanied by one published SPTBN4 staining protocol for patient tissue microarrays (PMC12048191).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human cervical carcinoma tissue; fixative not specified (datasheet A14322)
FixationImage fixative and duration unreported (datasheet A14322); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Tris-EDTA pH 9.0 (datasheet A14322); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-SPTBN4, 1:50 recommended; image 1:200 (datasheet A14322)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultSPTBN4-positive staining in medullary cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Expression in adrenal medulla and neuronal projections in CNS. No signal in the no-primary control.
💡Decision noteStart with heat-mediated Tris-EDTA retrieval at pH 9.0 (datasheet A14322); the published protocol reports antigen retrieval without specifying conditions (PMC12048191).
Section 2

What Is the Expected SPTBN4 Staining Pattern?

SPTBN4 is annotated at the cytoskeleton and cell cortex, with no transmembrane segment (UniProt Q9H254: location and topology). In paraffin IHC, expect staining in cerebellar granular cells and cerebral cortical neuronal projections; adrenal medullary and ovarian follicle cells may also stain (HPA tissue IHC). HPA rates its tissue profile Enhanced, while noting medium agreement with RNA data and presumed off-target staining that was disregarded (HPA tissue IHC).

What am I looking at on my slide?
Strong staining follows cerebral cortical neuronal projections, or appears in the cytoplasm/membrane of cerebellar granular cells (HPA tissue IHC).These match HPA's High IHC observations. Score the named cells and compartments rather than treating any color in the section as a positive result (HPA tissue IHC; general IHC practice).
An IHC section shows predominantly nuclear or nucleolar staining without the expected cortical projection or cerebellar granular-cell pattern (HPA tissue IHC).Treat this as an unresolved compartment mismatch and check controls and detection background (general IHC practice). HPA reports nucleolar staining in ICC-IF, so its IF observation should not be silently substituted for its tissue-IHC pattern (HPA subcellular; HPA tissue IHC).
Strong staining appears in adipocytes, marrow hematopoietic cells, or bronchial respiratory epithelial cells (HPA tissue IHC).HPA lists those specific cell populations as Not detected. Consider cross-reactivity or endogenous chromogenic detection activity, and assess controls before calling the tissue positive (HPA tissue IHC; general IHC practice).
Color spreads across cells and extracellular areas without a recognizable cellular or projection pattern (general IHC practice).This is background until controls support specific staining. Check blocking, washes, detection reagent background, and the counterstain; diffuse color alone cannot establish the HPA cell-specific pattern (general IHC practice; HPA tissue IHC).
No staining appears in cerebellar granular cells or cerebral cortical neuronal projections (HPA tissue IHC).A negative result in either HPA High population makes that run hard to interpret. Review the positive control, tissue preservation, retrieval, primary-antibody conditions, and detection controls before scoring other sections (HPA tissue IHC; general IHC practice).
💡Expected SPTBN4 appearanceA convincing positive is High staining in cerebral cortical neuronal projections or cerebellar granular-cell cytoplasm/membrane (HPA tissue IHC); nuclear-only color or strong staining in an HPA Not detected cell population calls for control review (HPA tissue IHC; general IHC practice).
How each factor affects the staining
Cellular location and topology (UniProt Q9H254)SPTBN4 is annotated at the cytoskeleton and cell cortex and has no transmembrane segment (UniProt Q9H254). Use the observed HPA cell and compartment patterns to judge IHC; topology alone does not predict staining intensity (HPA tissue IHC; UniProt Q9H254).
Isoforms and epitope coverage (UniProt Q9H254)Five isoforms are listed, but the supplied record gives no antibody epitope or isoform coverage (UniProt Q9H254; HPA antibodies). An unexpected negative cannot be attributed to a particular isoform from these data; review antibody documentation if isoform recognition matters (general IHC practice).
IHC evidence and limits (HPA tissue IHC; HPA antibodies)HPA rates tissue IHC Enhanced and lists HPA054481 as Enhanced for IHC, while reporting medium consistency with RNA data and disregarded presumed off-target binding (HPA tissue IHC; HPA antibodies). Interpret a new stain against the specified cell patterns and controls (general IHC practice).
IF/ICC Q: Should nucleolar staining define a positive IHC section? (HPA subcellular)A: HPA reports mainly nucleoli, with additional nucleoplasm, in ICC-IF; HPA tissue IHC instead highlights neuronal projections and cerebellar granular-cell cytoplasm/membrane (HPA subcellular; HPA tissue IHC). Evaluate each application against its own evidence and controls (general IHC practice).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known-positive cerebral cortex or cerebellum has little or no expected staining (HPA tissue IHC).Target-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation.Check tissue preservation, retrieval and detection controls, then adjust one general IHC condition at a time using an appropriate positive control (general IHC practice).
Signal is diffuse across the section or obscures cell boundaries (general IHC practice).Nonspecific reagent binding, incomplete washing, or detection background can obscure localization (general IHC practice).Inspect the no-primary control; review blocking, washes, primary-antibody conditions, and chromogen development before interpreting compartments (general IHC practice).
The IHC signal is predominantly nucleolar (HPA subcellular; HPA tissue IHC).The ICC-IF nucleolar observation and tissue-IHC observations differ; these sources do not resolve the reason (HPA subcellular; HPA tissue IHC).Compare positive tissue and no-primary controls, then require the expected tissue-specific pattern before assigning an IHC-positive call (HPA tissue IHC; general IHC practice).
HPA Not detected cell populations stain strongly, including adipocytes or marrow hematopoietic cells (HPA tissue IHC).Cross-reactivity or endogenous detection activity is possible; the tissue profile alone cannot distinguish them (HPA tissue IHC; general IHC practice).Run a no-primary control and assess detection background alongside a known-positive population before scoring those cells (general IHC practice; HPA tissue IHC).
Adrenal medullary or ovarian follicle staining looks weaker than staining in HPA High populations (HPA tissue IHC).HPA reports Medium staining in those cells and High staining in cortical projections and cerebellar granular cells (HPA tissue IHC).Score each named cell population against its reported level; do not require a Medium population to match a High one (HPA tissue IHC; general IHC practice).
A section has patchy staining that changes across tissue areas (general IHC practice).Uneven reagent coverage or section quality may cause a patchy pattern; the supplied sources do not establish a SPTBN4-specific cause (general IHC practice).Inspect section integrity and staining uniformity, and compare the same cell population in a well-preserved area and positive control (general IHC practice).

Sample controls for SPTBN4 IHC & IF

🧪Run cerebellum first and look for cytoplasmic or membrane staining in granular cells (HPA: High in cerebellar granular cells). Use adipose tissue as a negative comparator because adipocytes are not detected (HPA: Not detected in adipocytes); cells outside the expected granular-cell pattern on the positive slide should show counterstain without specific chromogen, but their SPTBN4 status is unverified.
Positive control tissue: Adrenal gland (Medullary cells, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show SPTBN4 in HEK293, SH-SY5Y, U2OS, with annotated localisation: Nucleoli (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only section and an isotype control matched to the primary antibody’s host species and clonality; use SPTBN4 knockout material, if available, as a biological specificity control (standard IHC control practice). For chromogenic detection, quench endogenous peroxidase and inspect the no-primary cerebellar section for background pigment (standard IHC practice).
⚠️Feasibility: The selected A14322 paraffin-section caption reports Tris-EDTA retrieval at pH 9.0, but its fixative is unreported; a target-specific fixation window and dependence on retrieval are unreported (A14322 tissue-IHC caption). The supplied evidence does not establish whether frozen sections or IF would be easier; the separate ICC-IF evidence reports nucleolar and nucleoplasmic signal, whereas UniProt annotates cytoskeletal and cell-cortex localization (HPA: subcellular ICC-IF; UniProt Q9H254 subcellular). Cerebellar lipofuscin can cause autofluorescence in IF, so inspect an unstained or no-primary section when assessing fluorescence (standard IF practice).

HPA tissue IHC evidence for SPTBN4

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Presumed off target binding observed and disregarded.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Medullary cells Medium Protein (IHC) HPA →
Cerebellum Granular cells - cytoplasm/membrane High Protein (IHC) HPA →
Cerebral cortex Neuronal projections High Protein (IHC) HPA →
Ovary Follicle cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Appendix Endocrine cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced SPTBN4 IHC Tips

Troubleshoot SPTBN4 staining in paraffin sections by checking retrieval, cell type, compartment, and controls before interpreting chromogenic signal.

How should I adjust retrieval when SPTBN4 staining is weak?
Start with heat-mediated retrieval in Tris-EDTA at pH 9.0 (datasheet A14322). The selected paraffin-section example pairs this retrieval with primary antibody at 1:200 overnight at 4°C (caption A14322). If staining remains weak, compare retrieval duration and heating consistency across adjacent sections while holding antibody dilution and detection constant (standard IHC practice). Use a known positive compartment, such as neuronal projections in cerebral cortex, to judge recovery; widespread staining alone is unconvincing because presumed off-target binding was observed in the tissue survey (HPA: high in cerebral-cortex neuronal projections; HPA: Enhanced reliability description).
Could fixation explain weak or patchy SPTBN4 staining?
Target-specific fixation sensitivity is unknown: the selected paraffin-section caption does not state a fixative (caption A14322). Record the actual fixative, fixation duration, section age, and processing history before comparing cases, since each can affect antigen preservation in routine IHC (standard IHC practice). On matched sections, keep Tris-EDTA retrieval at pH 9.0 and the primary antibody at 1:200 overnight at 4°C while checking whether staining varies with processing history (datasheet A14322; caption A14322). Do not assign a fixation effect to SPTBN4 from tissue-expression patterns; evaluate morphology and the same positive control alongside each comparison (standard IHC practice).
Which staining compartment should I expect in tissue sections?
Assess the stained cell and its subcellular pattern together: SPTBN4 is annotated at the cytoskeleton and cell cortex, with no transmembrane segment (UniProt Q9H254 topology and subcellular annotation). Tissue IHC reports high staining in cerebral-cortex neuronal projections and cerebellar granular-cell cytoplasm or membrane (HPA: cerebral cortex; HPA: cerebellum). The subcellular imaging record instead reports mainly nucleolar staining with additional nucleoplasmic staining, so a nuclear-only tissue result needs independent scrutiny (HPA: subcellular localisation). Compare serial-section morphology and a no-primary control before calling punctate nuclear, diffuse stromal, or peripheral staining specific (standard IHC practice; UniProt Q9H254 subcellular annotation).
Can this antibody distinguish SPTBN4 isoforms in paraffin sections?
Do not assign an isoform from chromogenic staining alone: the record lists 5 SPTBN4 isoforms, but the supplied IHC caption gives no epitope or isoform coverage (UniProt Q9H254 isoforms; caption A14322). The protein has two N-terminal calponin-homology domains and a C-terminal PH domain, which makes the antibody's mapped epitope relevant when comparing splice forms (UniProt Q9H254 domains and isoforms). Check the catalog antibody's immunogen or epitope documentation before claiming shared or isoform-specific detection (standard antibody-validation practice). If the epitope remains unknown, report the result as antibody-detected SPTBN4 staining and seek orthogonal, isoform-aware evidence before assigning a splice form (standard antibody-validation practice).
How can IF help resolve an ambiguous chromogenic pattern?
Use IF as a separate validation experiment and multiplex with a marker identifying the expected cell type, then inspect whether SPTBN4 signal occupies the same cells and plausible subcellular structures (standard IF practice; HPA: neuronal projections in cerebral cortex). Choose a fluorophore channel with low tissue autofluorescence, and assess each channel with single-stain and no-primary controls (standard IF practice). SPTBN4 has no transmembrane segment and is annotated at the cytoskeleton and cell cortex; permeabilise as needed for access to an intracellular epitope, after checking the antibody's epitope information (UniProt Q9H254 topology and subcellular annotation; standard IF practice). Nuclear signal deserves particular review because subcellular imaging reports nucleolar and nucleoplasmic localisation (HPA: subcellular localisation).
What should I change when the DAB background obscures specific staining?
First inspect no-primary and detection-only sections, especially where pigment, necrosis, or endogenous peroxidase could mimic DAB signal (standard chromogenic IHC practice). Apply an appropriate peroxidase block, then optimise protein blocking, wash stringency, antibody concentration, and DAB development one variable at a time (standard chromogenic IHC practice). The paraffin-section example used primary antibody at 1:200 overnight at 4°C and secondary antibody at 1:200 for 45 minutes at room temperature; these are starting conditions, not evidence that background is absent (caption A14322). Require staining to match a plausible cell and compartment, since presumed off-target binding was observed and disregarded in the tissue survey (HPA: reliability description).
How should I score SPTBN4 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scored cell population and compartment before measuring intensity, because tissue IHC reports neuronal projections in cerebral cortex and cytoplasm or membrane in cerebellar granular cells (HPA: cerebral cortex; HPA: cerebellum). For cell bodies, report percent positive cells and an H-score using intensity categories 0–3; for projections, report positive area or signal density per mm² of eligible tissue (standard IHC quantification practice). Normalise cell-based scores to eligible cells and area-based scores to viable, analysable tissue area, excluding folds, edges, and necrosis by a prespecified rule (standard IHC quantification practice). Keep staining and image-analysis thresholds consistent across batches, using the same positive and negative controls to monitor drift (standard IHC quantification practice).
When should an apparent SPTBN4-positive result be considered artefactual?
Give greatest weight to signal in an expected cell and compartment, such as cerebral-cortex neuronal projections or cerebellar granular-cell cytoplasm or membrane (HPA: cerebral cortex; HPA: cerebellum). Be cautious with staining restricted to section edges, necrotic regions, or cells without an expected pattern; compare those areas with morphology and no-primary controls (standard IHC practice). Endogenous peroxidase can create chromogenic signal, so confirm that the peroxidase block and detection-only control behave as expected (standard chromogenic IHC practice). Nuclear staining alone requires corroboration: subcellular imaging reports nucleolar and nucleoplasmic localisation, while the tissue survey reports presumed off-target binding and only medium staining–RNA consistency (HPA: subcellular localisation; HPA: reliability description).
Boster reagents

Best SPTBN4 / Spectrin beta chain, non-erythrocytic 4 IHC Antibodies

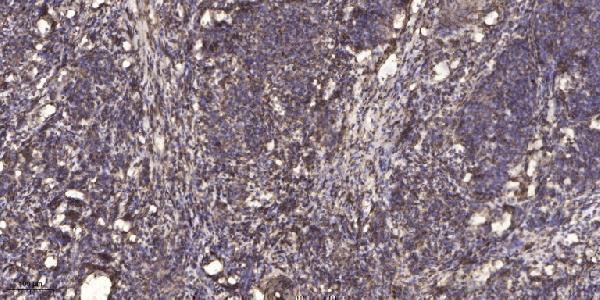
A14322 has real IHC data from paraffin-embedded human cervical carcinoma (catalog IHC image caption). IF is listed for human samples, but no IF figure is supplied (catalog applications; catalog reactivity; catalog IF images).

Real IHC data Immunohistochemical analysis of paraffin-embedded human cervical carcinoma. 1, Antibody was diluted at 1:200 (4° overnight). 2, Tris-EDTA, pH9.0 was used for antigen retrieval. 3, Secondary antibody was diluted at 1:200 (room temperature, 45min).
Anti-SPTN4 SPTBN4 Antibody
Cat # A14322

A14322 is listed for human IHC and IF (catalog applications; catalog reactivity). Its IHC image shows paraffin-embedded human cervical carcinoma; no IF image is supplied (catalog IHC image caption; catalog IF images).

Which to pick: For tissue IHC, choose A14322 for human paraffin sections; the fixative is unreported (catalog IHC image caption). For IF, A14322 is listed for human samples, but ICC is not listed and no IF image is supplied; its host is rabbit and clonality is unreported (catalog applications; catalog reactivity; catalog IF images; catalog host; catalog clone). No cross-species option is supported by this payload because A14322 lists human reactivity only (catalog reactivity).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9H254 (SPTN4_HUMAN, Spectrin beta chain, non-erythrocytic 4).
  2. Human Protein Atlas. SPTBN4 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. SPTBN4 subcellular location (ICC-IF): Mainly localized to the nucleoli. In addition localized to the nucleoplasm..
  4. Human Protein Atlas. SPTBN4 antibody validation summary (1 antibodies).
  5. Multiomics Approach Distinguishes SPTBN4 as a Key Molecule in Diagnosis, Prognosis, and Immune Suppression of Testicular Seminomas. International journal of genomics 2025 — PMC12048191.
  6. DNA methylation map of mouse and human brain identifies target genes in Alzheimer's disease. Brain : a journal of neurology 2013 — PMC3784285.
  7. Novel bi-allelic variants expand the SPTBN4-related genetic and phenotypic spectrum. European journal of human genetics : EJHG 2021 — PMC8298470.
  8. PubMed PMID:11294830 — UniProt-cited evidence.
  9. PubMed PMID:11086001 — UniProt-cited evidence.
  10. PubMed PMID:15057824 — UniProt-cited evidence.