ST18 / Suppression of tumorigenicity 18 protein · IHC design guide

Design Immunohistochemistry for ST18

Plan chromogenic ST18 IHC in paraffin sections using the catalog antibody’s 1:100–1:300 dilution range (datasheet A10267-1). Compare nuclear and cytoplasmic staining with HPA tissue observations, bearing in mind its uncertain reliability rating (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ST18 (IHC for ST18): expected localisation Nuclear and cytoplasmic tissue staining (HPA tissue IHC), antibody A10267-1, validated IHC image, and IHC protocol steps
Printable ST18 IHC protocol sheet — expected localisation Nuclear and cytoplasmic tissue staining (HPA tissue IHC), antibody A10267-1, controls and protocol steps. Open the full ST18 IHC guide →

ST18 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear and cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern General nuclear and cytoplasmic staining (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A10267-1)
Positive control ⓘ Cerebral cortex+4 more · see all
Negative control ⓘ Appendix+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections (standard IHC practice; not target-specific)
Caveat Antibody staining has low concordance with RNA (HPA tissue IHC)
Regulation ST18 abundance regulation is unreported (UniProt)
Isoform / epitope No isoforms or cleavage annotated; epitope dependence unknown (UniProt)
Section 1

Recommended ST18 IHC & IF Protocols

Start with the catalog antibody’s IHC-P protocol, then compare the published ST18 staining conditions for mouse embryonic cryosections (PMC9751150).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human tonsil tissue; fixative not specified (datasheet A10267-1)
FixationImage fixative and duration unreported (datasheet A10267-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Tris-EDTA pH 9.0 (datasheet A10267-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-ST18, 1:100-1:300 (datasheet A10267-1)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultST18-positive staining in neuronal cells of cerebral cortex (HPA tissue IHC: High). HPA tissue profile: General nuclear and cytoplasmic expression. No signal in the no-primary control.
💡Decision noteFor paraffin sections, start with heat-mediated Tris-EDTA pH 9.0 retrieval (datasheet A10267-1); the published cryosection protocol does not report retrieval (PMC9751150).
Section 2

What Is the Expected ST18 Staining Pattern?

ST18 is annotated as nuclear and has no transmembrane segment (UniProt O60284). In tissue IHC, look for staining in cerebral cortical neurons, kidney tubule cells, smooth muscle cells, and stomach glandular cells, where HPA reports high staining (HPA tissue IHC). HPA also describes general nuclear and cytoplasmic expression, but rates the tissue pattern Uncertain because antibody staining and RNA expression show low consistency (HPA tissue IHC).

What am I looking at on my slide?
Distinct nuclear staining in cerebral cortical neurons, kidney tubule cells, smooth muscle cells, or stomach glandular cells.This fits the UniProt nuclear annotation and HPA high-staining cell groups (UniProt O60284; HPA tissue IHC). Score the named cells and compartment separately: HPA reports general nuclear and cytoplasmic staining, so nuclear predominance is an expectation, not a validated nuclear-only rule (HPA tissue IHC).
Staining appears chiefly at cell borders or in a membrane-like pattern, with little nuclear signal.Treat the compartment mismatch as a possible staining artefact: UniProt places ST18 in the nucleus and reports no transmembrane segment (UniProt O60284). Review morphology and the detection controls before assigning membrane staining to ST18. HPA's reported cytoplasmic component does not establish membrane localisation (HPA tissue IHC).
Strong staining appears in cell groups outside the HPA high-staining groups, especially where a control section also stains.Consider cross-reactivity or endogenous detection activity as general IHC possibilities, then check a no-primary control and cell identity. HPA reports some additional cell groups at medium or low levels, so an unexpected cell group alone does not prove a false positive (HPA tissue IHC).
Colour is diffuse across cells, extracellular areas, or much of the section, without a readable compartment.The distribution cannot establish ST18 localisation. Assess general IHC causes such as background from the detection system or inadequate blocking, and compare with a no-primary control. The reference pattern is general nuclear and cytoplasmic expression in tissue, with Uncertain reliability (HPA tissue IHC).
A cerebral cortex, kidney, smooth muscle, or stomach section shows no staining in the named cells.First verify that the expected cell population is present and that the IHC run worked. These are high-staining examples in HPA, not guaranteed positive controls: its tissue assessment is Uncertain and pending external verification (HPA tissue IHC). An absent signal alone cannot establish absent ST18 protein.
💡Expected ST18 appearanceA persuasive positive result is readable, preferably nuclear staining in the HPA high-staining neuronal, tubular, smooth muscle, or glandular cells; general cytoplasmic staining has also been reported, while membrane-like or section-wide diffuse colour warrants control review (UniProt O60284; HPA tissue IHC).
How each factor affects the staining
Compartment and topologyUniProt annotates ST18 in the nucleus and reports no transmembrane segment (UniProt O60284). Use those facts to assess a proposed membrane pattern; HPA's tissue IHC profile also reports cytoplasmic staining, so compartment alone cannot validate antibody specificity (HPA tissue IHC).
Choice of tissue and cell populationHPA reports high staining in cerebral cortical neurons, kidney tubule cells, smooth muscle cells, and stomach glandular cells; it reports medium, low, and undetected groups elsewhere (HPA tissue IHC). Compare the relevant cells within each section instead of treating every cell as an equivalent control.
Strength of the tissue evidenceHPA rates the tissue IHC pattern Uncertain because antibody staining has low consistency with RNA expression; external verification is pending (HPA tissue IHC). Its high and undetected examples are useful comparison points, but neither category alone confirms an antibody's specificity.
Antibody-level validationThe listed antibody, HPA044919, is a rabbit polyclonal with IHC status Uncertain (HPA antibodies). Interpret its staining alongside tissue morphology and controls; the supplied record provides no stronger antibody-level validation claim.
IF/ICC evidenceHPA lists no main subcellular location and no cell lines with ICC-IF images for ST18 (HPA subcellular). The UniProt nuclear annotation is a starting expectation for IF/ICC, but the supplied HPA record does not show an IF/ICC staining pattern (UniProt O60284; HPA subcellular).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The expected cells are blank in a candidate positive section.The cell group may be absent from the field, or the IHC run may have failed; HPA high staining is an Uncertain observation (HPA tissue IHC).Locate the named cells on the counterstained section, check the run's general positive control, and compare another HPA high-staining tissue if available. Do not call the result biological absence from a single blank section (HPA tissue IHC).
Only cell borders stain strongly.A membrane-like pattern conflicts with the nuclear annotation and lack of a transmembrane segment (UniProt O60284).Check the no-primary control and review whether the colour follows cell borders or nuclear structures. Record the mismatch rather than scoring border staining as confirmed ST18; HPA reports nuclear and cytoplasmic tissue staining (HPA tissue IHC).
Unexpected cells stain more strongly than the HPA high-staining cell groups.Cross-reactivity or endogenous detection activity is possible in general IHC; HPA's tissue assessment is Uncertain (HPA tissue IHC).Confirm the stained cell type by morphology, inspect a no-primary control, and compare the HPA cell-specific entries. HPA also reports medium and low staining in other groups, so assess the full pattern before rejecting it (HPA tissue IHC).
The whole section has weak, diffuse colour.General IHC background can obscure compartment and cell-specific interpretation.Compare the no-primary control, review blocking and detection conditions, and score only distinguishable cellular staining. HPA's reported general nuclear and cytoplasmic profile is not a reason to count uniform section-wide colour as positive (HPA tissue IHC).
A tissue listed as undetected shows staining.The apparent conflict could reflect background or a real difference between samples; HPA's IHC pattern has Uncertain reliability (HPA tissue IHC).Verify the named cell population and compare a no-primary control. HPA lists appendix glandular cells, parathyroid glandular cells, and splenic red-pulp cells as not detected; treat these as comparison observations, not absolute negative standards (HPA tissue IHC).
Can the tissue IHC pattern be used as an IF/ICC expectation?HPA provides no ICC-IF image-bearing cell lines or main subcellular location for ST18 (HPA subcellular).Use UniProt's nuclear annotation as an initial localisation expectation, then assess IF/ICC controls on its own guide page. Do not transfer HPA's tissue staining intensity to an IF/ICC result (UniProt O60284; HPA tissue IHC; HPA subcellular).

Sample controls for ST18 IHC & IF

🧪Run stomach first: glandular cells should show ST18 staining (HPA: High in stomach glandular cells), with nuclear localisation expected (UniProt O60284: nucleus). Use appendix glandular cells as the negative tissue (HPA: Not detected in appendix glandular cells); on the stomach slide, assess other cells for background without assuming they are ST18-negative (HPA: High is assigned to glandular cells).
Positive control tissue: Cerebral cortex (Neuronal cells, HPA High)
Negative control tissue: Appendix (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for ST18; derive a cell-line control from the positive tissue's cell type (Neuronal cells) and confirm it by RNA or western blot first.
Technical controls: Include no-primary (secondary-only) and isotype controls matched to the primary antibody’s host species and immunoglobulin class or subclass, plus a comparably processed ST18 knockout sample as a biological negative. For chromogenic stomach IHC, quench endogenous peroxidase and check for residual glandular background; block endogenous biotin if using avidin–biotin detection.
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A10267-1 tonsil caption does not state a fixative (selected-SKU tissue-IHC caption). Retrieval dependence is unestablished; that caption uses Tris-EDTA at pH 9.0 and a 1:200 primary dilution for paraffin-section IHC (selected-SKU tissue-IHC caption). Neither frozen sections nor IF can be judged easier from the supplied evidence; HPA lists no ICC-IF image cell lines, and stomach glandular background should be assessed during scoring (HPA subcellular record; HPA: High in stomach glandular cells).

HPA tissue IHC evidence for ST18

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Cerebral cortex Neuronal cells High Protein (IHC) HPA →
Kidney Cells in tubules High Protein (IHC) HPA →
Smooth muscle Smooth muscle cells High Protein (IHC) HPA →
Stomach Glandular cells High Protein (IHC) HPA →
Adipose tissue Adipocytes Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Appendix Glandular cells Not detected Protein (IHC) HPA →
Parathyroid gland Glandular cells Not detected Protein (IHC) HPA →
Spleen Cells in red pulp Not detected Protein (IHC) HPA →
Section 3

Advanced ST18 IHC Tips

Troubleshoot ST18 staining in paraffin sections by checking retrieval, nuclear localisation, controls and scoring; interpret discordant patterns cautiously (UniProt O60284; HPA tissue IHC).

How should I optimise retrieval when ST18 staining is weak in paraffin sections?
Use heat-mediated Tris-EDTA at pH 9.0 for ST18 paraffin-section IHC (datasheet A10267-1). The selected tonsil image used this retrieval with primary antibody at 1:200 overnight at 4 °C (caption A10267-1). If staining is weak, compare controlled changes in heating time or cooling while keeping section thickness, detection and exposure to chromogen consistent (standard IHC practice). Include a known staining reference section in each run, and examine whether stronger retrieval also raises nonspecific staining or damages tissue (standard IHC practice). Record the retrieval conditions alongside nuclear and cytoplasmic staining because the HPA tissue pattern has uncertain reliability (HPA tissue IHC).
Could fixation explain weak or uneven ST18 staining?
Target-specific ST18 sensitivity to fixation is unknown: the selected paraffin-embedded tonsil caption does not state its fixative (caption A10267-1). Do not infer fixation tolerance from the reported tissue staining or from ST18 having no annotated transmembrane segment or glycosylation sites (HPA tissue IHC; UniProt O60284). For a controlled comparison, process matched specimens with documented fixation and processing conditions, then apply the same retrieval and chromogenic detection (standard IHC practice). Check morphology and staining across section interiors and edges before attributing a difference to antigen loss (standard IHC practice). Report the actual fixative and processing history with any proposed fixation effect (standard IHC practice).
Should ST18 staining be nuclear if some cells also show cytoplasmic signal?
Prioritise nuclear staining when assessing ST18, which is annotated in the nucleus and functions as a DNA-binding transcriptional repressor (UniProt O60284). HPA nevertheless describes general nuclear and cytoplasmic tissue staining, with uncertain reliability and low agreement with RNA expression (HPA tissue IHC). Compare each compartment within the same cell type and run, using a counterstain to identify intact nuclei (standard IHC practice). If cytoplasmic staining dominates, inspect negative controls, tissue preservation and retrieval-dependent background before assigning it to ST18 (standard IHC practice). Report nuclear and cytoplasmic scores separately so an uncertain cytoplasmic signal cannot inflate the nuclear result (HPA tissue IHC; standard IHC practice).
How do I assess an unexpected staining pattern when the ST18 epitope is unspecified?
The supplied record lists a 1,047-residue ST18 chain and no annotated isoforms, signal peptide, propeptide, glycosylation sites or modified residues (UniProt O60284). It provides no antibody epitope location, so those annotations cannot establish which region the catalog antibody recognises (UniProt O60284; caption A10267-1). When a pattern is unexpected, compare staining across retrieval conditions and use an independent, validated antibody recognising a documented different epitope if available (standard IHC practice). Keep tissue, detection and scoring conditions matched so agreement is interpretable (standard IHC practice). Treat discordant compartment patterns as unresolved until supported by an orthogonal assay and suitable controls (standard IHC practice).
How can I use IF to investigate an uncertain ST18 IHC pattern?
Use IF as a separate validation experiment; the supplied HPA subcellular record lists no ICC/IF images, while the selected antibody image documents paraffin-section IHC (HPA subcellular; caption A10267-1). Multiplex ST18 with a validated marker for the expected cell type, selected from the tissue being examined, and assess nuclear overlap using a DNA counterstain (standard IF practice). Choose fluorophores after checking that tissue’s autofluorescence and spectral bleed-through, and include single-stain controls (standard IF practice). Because ST18 is annotated in the nucleus and lacks a transmembrane segment, optimise permeabilisation for access to an intracellular nuclear epitope without assuming its precise location (UniProt O60284; standard IF practice). Do not transfer the IHC dilution or retrieval conditions directly to IF (caption A10267-1; standard IF practice).
How do I distinguish ST18 signal from chromogenic background?
Inspect a matched no-primary control for detection-system staining and use an appropriate peroxidase block before DAB development (standard chromogenic IHC practice). The selected tonsil image specifies primary antibody at 1:200 overnight at 4 °C and secondary antibody at 1:200 for 45 minutes at room temperature (caption A10267-1). Treat those settings as a documented starting point, then compare titrations while keeping retrieval, washes and DAB development consistent (standard IHC practice). Check tissue edges, folds, damaged regions and diffuse precipitate before interpreting increased colour as expression (standard IHC practice). Assess nuclear signal separately because ST18 is annotated in the nucleus, while HPA reports uncertain nuclear and cytoplasmic staining (UniProt O60284; HPA tissue IHC).
What should I score when comparing ST18 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring; nuclear localisation is annotated for ST18, whereas HPA tissue staining includes uncertain cytoplasmic signal (UniProt O60284; HPA tissue IHC). For comparable sections, report the percentage of positive nuclei and an intensity-based H-score, with blinded thresholds set from controls (standard IHC practice). If cell abundance differs substantially, report positive-cell density per mm² as well (standard IHC practice). Normalise counts to the number of evaluable cells or viable tissue area within the same annotated region, and exclude folds and necrosis (standard IHC practice). Keep retrieval, staining batch, counterstain and image-acquisition settings documented for comparisons (standard IHC practice).
When should an apparent ST18-positive cell be considered an artefact?
A plausible ST18-positive cell has assessable nuclear staining in intact tissue, consistent with its annotated nuclear localisation (UniProt O60284; standard IHC practice). Check the cell identity: HPA reports high staining in cerebral-cortex neuronal cells and kidney tubule cells, but rates its tissue-IHC reliability uncertain (HPA tissue IHC). Predominantly cytoplasmic colour, staining confined to section edges or necrosis, and signal in no-primary controls require investigation before a positive call (HPA tissue IHC; standard IHC practice). Endogenous peroxidase can also produce misleading chromogenic signal, so interpret staining only after appropriate blocking and controls (standard chromogenic IHC practice). Record discrepant cell types or compartments explicitly and seek independent corroboration before treating them as established ST18 expression (standard IHC practice).
Boster reagents

Best ST18 / Suppression of tumorigenicity 18 protein IHC Antibodies

Two anti-ST18 antibodies cover paraffin-section IHC in human tissue (catalog IHC captions); both list Human, Mouse and Rat reactivity (catalog reactivity), and one also lists IF (catalog applications).

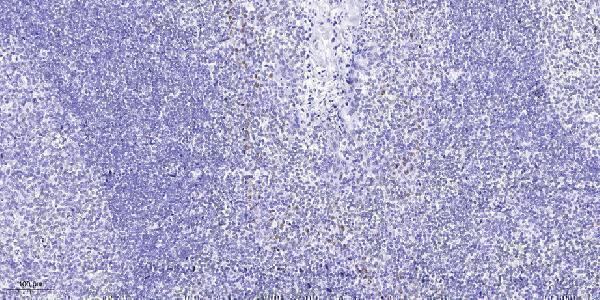
Real IHC data Immunohistochemical analysis of paraffin-embedded human tonsil. 1, Antibody was diluted at 1:200 (4° overnight). 2, Tris-EDTA, pH9.0 was used for antigen retrieval. 3, Secondary antibody was diluted at 1:200 (room temperature, 45min).
Anti-ST18 Antibody
Cat # A10267-1
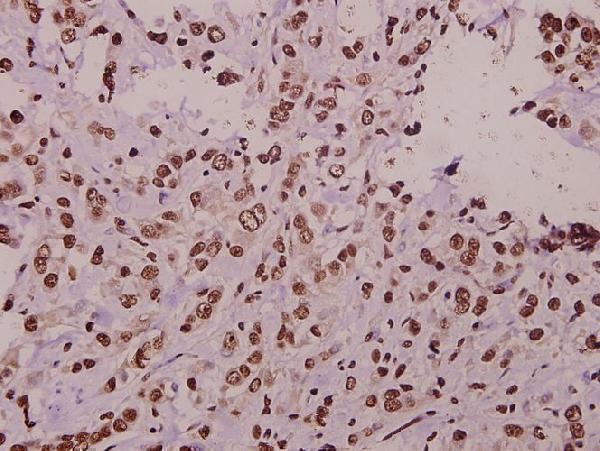
Real IHC data Immunohistochemistry (IHC) analyzes of ST18 (E72) pAb in paraffin-embedded human colorectal carcinoma tissue at 1:50.
Anti-ST18 (E72) Antibody
Cat # A10267

A10267 will render with an IHC image of paraffin-embedded human colorectal carcinoma at 1:50 (A10267 IHC caption). A10267-1 will render with an IHC image of paraffin-embedded human tonsil at 1:200 and also lists IF as an application (A10267-1 IHC caption; catalog applications).

Which to pick: For tissue IHC, choose the image-matched SKU: A10267 for paraffin-embedded human colorectal carcinoma or A10267-1 for paraffin-embedded human tonsil (respective IHC captions); the fixative is unreported in both captions. For IF, choose A10267-1 because IF is listed for that SKU, while ICC validation and an IF image are unreported (A10267-1 catalog applications and images). Both are rabbit antibodies with no clone specified and list Human, Mouse and Rat reactivity, but their displayed IHC evidence is human tissue only (catalog host, clone and reactivity; respective IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O60284 (ST18_HUMAN, Suppression of tumorigenicity 18 protein).
  2. Human Protein Atlas. ST18 tissue IHC expression (reliability: Uncertain).
  3. Human Protein Atlas. ST18 subcellular location (ICC-IF): Highest expression in HAP1: 1.6 nTPM.
  4. Human Protein Atlas. ST18 antibody validation summary (1 antibodies).
  5. Long interspersed nuclear element-1 hypomethylation is associated with poor outcomes via the activation of ST18 in human hepatocellular carcinoma. Medicine 2021 — PMC8078304.
  6. St18 specifies globus pallidus projection neuron identity in MGE lineage. Nature communications 2022 — PMC9751150.
  7. Denosumab Regulates Titanium Particles-Induced Macrophages Inflammation and Osteolysis by Targeting the ST18/PARP1 Interaction. Orthopaedic surgery 2026 — PMC12862431.
  8. PubMed PMID:9628581 — UniProt-cited evidence.
  9. PubMed PMID:15489334 — UniProt-cited evidence.
  10. PubMed PMID:15489893 — UniProt-cited evidence.