TBKBP1 / TANK-binding kinase 1-binding protein 1 · IHC design guide

Design Immunohistochemistry for TBKBP1

Plan paraffin-section TBKBP1 IHC using 5 μg/mL as the catalog antibody’s starting concentration (datasheet: A10984 IHC-P). Compare high staining in placental decidual cells with undetected staining in adrenal glandular cells, and score cytoplasmic and vessel staining by cell type (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for TBKBP1 (IHC for TBKBP1): expected localisation Cytoplasmic staining and vessel expression (HPA tissue IHC), antibody A10984, validated IHC image, and IHC protocol steps
Printable TBKBP1 IHC protocol sheet — expected localisation Cytoplasmic staining and vessel expression (HPA tissue IHC), antibody A10984, controls and protocol steps. Open the full TBKBP1 IHC guide →

TBKBP1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining and vessel expression (HPA tissue IHC)
Staining pattern Variable cytoplasmic staining across cell types and vessels (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Placenta+4 more · see all
Negative control ⓘ Adrenal gland+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Staining and RNA show low consistency (HPA tissue IHC)
Regulation Expression regulation not annotated (UniProt)
Isoform / epitope 2 isoforms; no annotated processing; epitope impact unknown (UniProt)
Section 1

Recommended TBKBP1 IHC & IF Protocols

The catalog antibody's IHC-P protocol is accompanied by one published TBKBP1 IHC protocol using human FFPE specimens (PMC12867762).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleTissue sections; selected-image fixative not specified (standard IHC workflow)
FixationImage fixative and duration unreported (datasheet A10984); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-TBKBP1, 5 μg/mL (datasheet A10984)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultTBKBP1-positive staining in decidual cells of placenta (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic and vessel expression at variable levels in several different cell types. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 retrieval at 95–98 °C for 20 min (page retrieval rule); compare the published primary dilution of 1:200 (PMC12867762).
Section 2

What Is the Expected TBKBP1 Staining Pattern?

In paraffin-section IHC, expect variable cytoplasmic and vessel-associated TBKBP1 staining, with high staining in placental decidual cells and late spermatids (HPA tissue IHC). HPA rates the tissue staining Approved, but reports low consistency with RNA expression and pending external verification (HPA tissue IHC). TBKBP1 has no annotated transmembrane segment (UniProt A7MCY6 topology); UniProt does not assign it a subcellular location (UniProt A7MCY6).

What am I looking at on my slide?
Decidual cells stain strongly in placenta, or elongated or late spermatids stain strongly in testis; signal appears cytoplasmic (HPA tissue IHC).This fits the reported High staining in those cell populations and the broader cytoplasmic IHC profile (HPA tissue IHC). Compare the named cells, not the entire tissue, when judging a control.
A paraffin section shows predominantly nuclear staining with little cytoplasmic signal (HPA tissue IHC).Investigate a compartment mismatch against the reported tissue IHC pattern before accepting it (HPA tissue IHC). HPA separately reports approved nucleoplasmic localisation by ICC-IF, so nuclear signal alone cannot establish an IHC artefact (HPA ICC-IF).
Cells reported as unstained, such as bronchial respiratory epithelium or adrenal glandular cells, show strong chromogen signal (HPA tissue IHC).The cell-level mismatch raises concern for antibody cross-reactivity or endogenous detection activity (standard IHC practice). HPA's Not detected designation applies to those specified cells; it does not establish that every cell in either tissue must be negative (HPA tissue IHC).
Chromogen covers cells and surrounding section broadly, obscuring cell boundaries (standard IHC practice).Treat this as background until controls support a cell-specific pattern (standard IHC practice). HPA describes variable cytoplasmic and vessel expression, so diffuse colour across all structures should not be scored as TBKBP1 positivity (HPA tissue IHC).
Placental decidual cells or late spermatids lack signal in an otherwise assessable section (HPA tissue IHC).These are reported High populations, making them useful positive comparators (HPA tissue IHC). First check section quality, primary-antibody application and detection controls (standard IHC practice); one negative result cannot establish that the specimen lacks TBKBP1.
💡Expected TBKBP1 appearanceCall an IHC result consistent when identifiable decidual cells or late spermatids show High, mainly cytoplasmic staining, with variable vessel-associated signal; widespread staining of reported negative cell types is suspect (HPA tissue IHC; standard IHC practice).
How each factor affects the staining
Cell population and tissueHPA reports High staining in decidual cells and late spermatids, but Medium staining in adipocytes and bone-marrow hematopoietic cells (HPA tissue IHC); compare like cells.
Assay-specific localisationTissue IHC describes cytoplasmic and vessel expression (HPA tissue IHC); ICC-IF reports approved nucleoplasmic localisation (HPA ICC-IF). Assess each result in its assay.
Strength of tissue evidenceIHC is Approved for 2 listed antibodies, yet tissue staining has low RNA consistency and awaits external verification (HPA antibodies; HPA tissue IHC).
Isoform coverageUniProt lists 2 isoforms (UniProt A7MCY6). The payload gives no antibody epitope or isoform coverage, so staining cannot be assigned to one isoform.
Chromogenic detection backgroundEndogenous enzyme activity or inadequate blocking can mimic antibody signal in IHC (standard IHC practice). Use detection controls when a reported negative cell population stains.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in placental decidual cells or late spermatids.These cells are reported High; failure of staining or detection is possible (HPA tissue IHC; standard IHC practice).Check morphology, primary-antibody application, retrieval and chromogen controls on a positive section; optimise one step at a time without assuming TBKBP1-specific retrieval sensitivity (standard IHC practice).
Only nuclei stain in paraffin-section IHC.The result differs from the reported cytoplasmic tissue IHC profile, although ICC-IF reports nucleoplasmic localisation (HPA tissue IHC; HPA ICC-IF).Review cell boundaries and counterstain, then compare the same IHC run with a positive tissue control (standard IHC practice). Keep the ICC-IF observation assay-specific.
Bronchial respiratory epithelial cells stain strongly.HPA reports this cell population as Not detected; cross-reactivity or detection background is possible (HPA tissue IHC; standard IHC practice).Check a primary-omission control and, for enzyme-based detection, the relevant endogenous-enzyme block before interpreting epithelial staining (standard IHC practice).
Uniform colour obscures adipocytes or glandular cells.Diffuse background can hide the Medium cell-specific staining reported in adipose tissue or selected glands (HPA tissue IHC; standard IHC practice).Inspect the primary-omission control, blocking and washes; adjust antibody concentration only against a positive comparator (standard IHC practice).
A whole tissue is called negative because one cell type is unstained.HPA levels refer to named populations: bronchial respiratory epithelium is Not detected, while placental decidual cells are High (HPA tissue IHC).Score the specified cells separately from vessels and other cells; record both distribution and intensity (HPA tissue IHC; standard IHC practice).
An IHC result disagrees with RNA abundance or an ICC-IF image.HPA reports low tissue staining–RNA consistency and different compartment summaries for tissue IHC and ICC-IF (HPA tissue IHC; HPA ICC-IF).Document assay, cell population and controls; treat the disagreement as unresolved and seek independent validation before making a firm localisation claim (standard IHC practice).

Sample controls for TBKBP1 IHC & IF

🧪Run placenta first and look for staining in decidual cells (HPA: High in decidual cells). Use adrenal glandular cells as the negative tissue (HPA: Not detected); on the placenta slide, compare decidual staining with any morphologically distinct cells that remain at background, without assuming those cells are target-negative.
Positive control tissue: Placenta (Decidual cells, HPA High)
Negative control tissue: Adrenal gland (HPA Not detected)
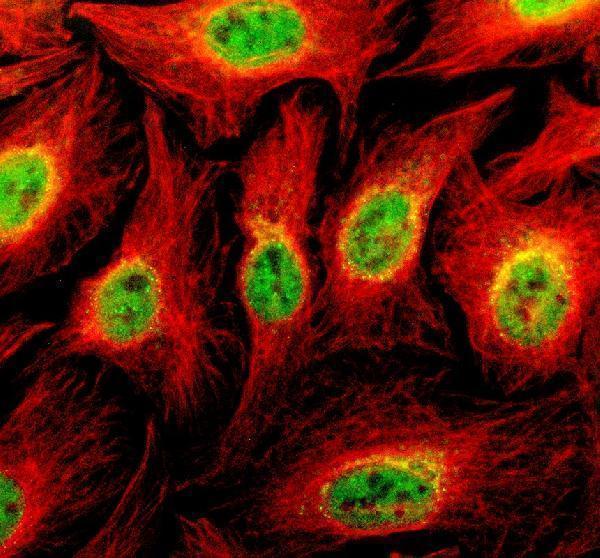
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show TBKBP1 in CACO-2, HEK293, U2OS, with annotated localisation: Nucleoplasm (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, a control antibody matched to the primary antibody’s host species and class, and a TBKBP1 knockout specimen or immunizing-peptide competition where available (standard IHC practice). For placental sections, quench endogenous peroxidase with HRP detection and check endogenous biotin if using avidin–biotin detection (standard IHC practice).
⚠️Feasibility: A target-specific fixation window and antigen-retrieval dependency are unreported in the supplied evidence; the selected A10984 tissue-IHC caption also leaves the fixative unreported (selected-SKU caption: fixative not stated). The supplied evidence does not establish that frozen sections or IF/ICC are easier than paraffin IHC, although ICC-IF images are available and show nucleoplasmic localization (HPA: subcellular). In placenta, blood-associated endogenous peroxidase can complicate chromogenic interpretation, so assess it with the detection controls (standard IHC practice).

HPA tissue IHC evidence for TBKBP1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data. Pending external verification. External characterization data supports antibody staining.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Placenta Decidual cells High Protein (IHC) HPA →
Testis Elongated or late spermatids High Protein (IHC) HPA →
Adipose tissue Adipocytes Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →
Breast Adipocytes Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Section 3

Advanced TBKBP1 IHC Tips

Troubleshoot TBKBP1 chromogenic IHC by checking retrieval, staining compartment, antibody specificity, and cell-level controls (HPA tissue IHC; HPA subcellular).

How should I retrieve TBKBP1 antigen when paraffin-section staining is weak?
Start with citrate buffer at pH 6.0, heated to 95–98 °C for 20 minutes (page retrieval specification). Allow sections to cool in buffer, then compare retrieved and unretrieved control sections processed with the same antibody dilution and detection reagents (standard IHC practice). If staining remains weak, test a second retrieval condition on matched sections as a fallback, while watching for tissue damage or increased background (standard IHC practice). TBKBP1 has no annotated transmembrane segment, but that does not establish whether its antibody epitope survives retrieval (UniProt A7MCY6 topology; standard IHC practice). Score the expected cells and compartments separately because reported tissue staining is variable (HPA tissue IHC).
Could fixation be masking TBKBP1 staining in my paraffin sections?
Target-specific sensitivity of TBKBP1 to fixation is unknown from the supplied evidence (supplied evidence). Record the specimen fixative, fixation duration, processing history, and section age before comparing cases, because these variables can change antigen accessibility in paraffin sections (standard IHC practice). If matched material is available, compare routinely fixed sections with sections processed under a shorter, documented fixation condition while holding retrieval and antibody concentration constant (standard IHC practice). Include a tissue with reported TBKBP1 staining, such as placental decidual cells, and assess preservation alongside signal (HPA: High in placental decidual cells; standard IHC practice). Do not use tissue staining patterns to assign a TBKBP1-specific fixation effect (HPA tissue IHC; supplied evidence).
Should I expect nuclear or cytoplasmic TBKBP1 staining in tissue IHC?
Treat compartment as a question to resolve experimentally: tissue IHC reports variable cytoplasmic and vessel staining, while approved cell imaging reports nucleoplasmic localisation (HPA tissue IHC; HPA subcellular). UniProt supplies no subcellular annotation for TBKBP1, so neither pattern alone establishes the correct compartment in your section (UniProt A7MCY6 subcellular; standard IHC practice). Score nuclear and cytoplasmic signal separately in the same defined cell populations, with a nuclear counterstain and identical exposure to chromogen (standard IHC practice). Review vessel-associated staining against tissue morphology and a no-primary control before treating it as cell-intrinsic expression (HPA tissue IHC; standard IHC practice). Reconcile any discordance using an independent antibody or orthogonal assay (standard IHC practice).
How can I assess whether the antibody recognizes both TBKBP1 isoforms?
TBKBP1 has 2 listed isoforms, but the supplied evidence does not map this antibody's epitope to either sequence (UniProt A7MCY6 isoforms; supplied evidence). Obtain the immunogen or epitope sequence and compare it with both isoforms before claiming pan-isoform staining (standard IHC practice). TBKBP1 also has reported phosphorylated serines, including residues 184 and 365, so an epitope overlapping a modified site may require separate validation (UniProt A7MCY6 modified residues; standard IHC practice). For a suspected isoform-specific pattern, compare the same cells using an independently mapped antibody or an isoform-resolving orthogonal assay (standard IHC practice). Keep retrieval and detection conditions constant during that comparison (standard IHC practice).
How should I check a TBKBP1 pattern using multiplex immunofluorescence?
Use IF/ICC as a separate validation experiment and compare its compartment pattern with chromogenic IHC rather than assuming they coincide (HPA subcellular; HPA tissue IHC). Multiplex TBKBP1 with a validated marker for the cell population being scored, such as decidual cells in placenta, and include a nuclear stain (HPA: High in placental decidual cells; standard IF practice). Choose a fluorophore channel away from the specimen's strongest autofluorescence, checking an unstained section under the same imaging settings (standard IF practice). TBKBP1 has no annotated transmembrane segment; for intracellular cytoplasmic or nucleoplasmic epitopes, test mild permeabilisation after fixation, while confirming the antibody's epitope accessibility experimentally (UniProt A7MCY6 topology; HPA subcellular; standard IF practice).
What should I change when TBKBP1 staining has diffuse background?
First inspect a no-primary section and the tissue edge to separate detection background from antibody-associated signal (standard IHC practice). For chromogenic detection, block endogenous peroxidase before applying the detection reagent and check whether vessel-rich areas retain signal in the no-primary control (standard IHC practice; HPA tissue IHC). Titrate the primary antibody downward and shorten incubation in matched sections, keeping retrieval at citrate pH 6.0, 95–98 °C for 20 minutes during the comparison (standard IHC practice; page retrieval specification). Also adjust blocking and washing if nonspecific staining persists, and inspect necrotic or damaged regions separately (standard IHC practice). Report background by compartment because tissue IHC describes both cytoplasmic and vessel staining (HPA tissue IHC).
How should I quantify TBKBP1 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, then use percent positive cells and an H-score for nuclear and cytoplasmic staining separately (standard IHC practice; HPA tissue IHC; HPA subcellular). Calculate H-score as 1 × % weak + 2 × % moderate + 3 × % strong, using the same intensity thresholds across slides (standard IHC practice). Normalise cell-based results to the number of evaluable cells in each annotated population, excluding folds, necrosis, and tissue edges (standard IHC practice). If reporting vessel-associated signal, use positive area or density per mm² of evaluable vessel area and state that denominator explicitly (HPA tissue IHC; standard IHC practice). Keep section processing and image acquisition consistent across groups (standard IHC practice).
How can I distinguish genuine TBKBP1 signal from staining artefact?
Compare signal with tissue morphology and reported cell patterns: decidual cells in placenta show high staining, while bronchial respiratory epithelial cells were not detected in the cited tissue survey (HPA tissue IHC). Treat a uniformly nuclear or uniformly cytoplasmic result cautiously because cell imaging reports nucleoplasmic localisation whereas tissue IHC reports variable cytoplasmic and vessel staining (HPA subcellular; HPA tissue IHC). Exclude edge staining, necrotic deposits, and endogenous peroxidase signal using adjacent morphology and a no-primary control (standard IHC practice). The supplied hero image caption names Prosapip2, so it cannot validate TBKBP1 staining for SKU A10984 (selected hero caption). Confirm a consequential interpretation with an independent antibody or orthogonal assay (standard IHC practice).
Boster reagents

Best TBKBP1 / TANK-binding kinase 1-binding protein 1 IHC Antibodies

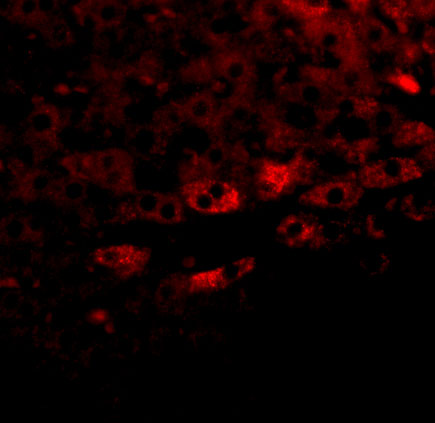
Real IHC and IF images show A10984 in rat liver and A10984-1 in U2OS cells; both list Human, Mouse, and Rat reactivity (catalog image captions; reactivity).

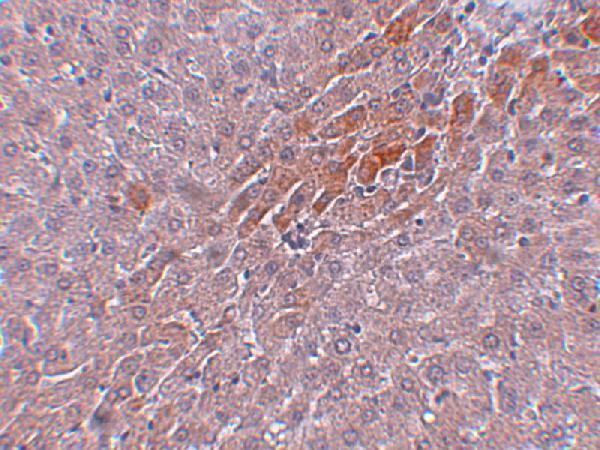
Real IHC data Immunohistochemistry of Prosapip2 in rat liver tissue with Prosapip2 antibody at 5 μg/mL.
Anti-Prosapip2 TBKBP1 Antibody
Cat # A10984
Real IF data IF analysis of TBKBP1 using anti-TBKBP1 antibody (A10984-1) and anti-Beta Tubulin antibody (M01857-3). TBKBP1 was detected in an immunocytochemical section of U2OS cells. Enzyme antigen retrieval was performed using IHC enzyme antigen retrieval reagent (AR0022) for 15 mins. The cells were blocked with 10% goat serum. And then incubated with 5 μg/mL rabbit anti-TBKBP1 Antibody (A10984-1) and mouse anti-Beta Tubulin antibody (M01857-3) overnight at 4°C. DyLight®488 Conjugated Goat Anti-Rabbit IgG (BA1127) and Cy3 Conjugated Goat Anti-Mouse IgG (BA1031) were used as secondary antibody at 1:500 dilution and incubated for 30 minutes at 37°C. Visualize using a fluorescence microscope and filter sets appropriate for the label used.
Anti-TBKBP1 Antibody ®
Cat # A10984-1

A10984 is listed for IHC-P and IF, with rat liver images at 5 μg/mL for IHC and 20 μg/mL for IF (catalog applications; image captions). A10984-1 is listed for IF/ICC, with a U2OS cell IF image at 5 μg/mL; IHC-P is absent from its application list (catalog applications; IF image caption).

Which to pick: Choose A10984 for paraffin-section IHC: it lists IHC-P and has a rat liver IHC image at 5 μg/mL; the image caption does not report a fixative (catalog applications; A10984 IHC image caption). Choose A10984-1 for cell IF/ICC based on its U2OS image, or A10984 for tissue IF based on its rat liver image (catalog applications; IF image captions). Both list Human, Mouse, and Rat reactivity, but the supplied IHC image covers rat liver only; neither catalog entry specifies a clone (catalog reactivity; A10984 IHC image caption; catalog clone fields).

Each figure is that product's own IHC / IF validation image from its datasheet.