This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic IHC for UBE2G1 in paraffin sections using the catalog antibody's 1:100–1:300 dilution range (datasheet A09806-1). Use the reported cytoplasmic pattern and high-staining glandular and hematopoietic cells to assess staining (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | General cytoplasmic staining (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic in glandular and hematopoietic cells (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A09806-1) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | None in HPA (detected in all 44 tissues); use no-primary + isotype controls |
| Fixation | Keep formalin fixation consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Staining and RNA show medium consistency (HPA tissue IHC) | |
| Regulation | Mainly expressed in skeletal muscle (UniProt) | |
| Isoform / epitope | No isoforms; Met1 removal warrants an N-terminal epitope check (UniProt) |
The catalog antibody’s IHC-P protocol (datasheet A09806-1) is accompanied by one published UBE2G1 IHC protocol in large yellow croaker (PMC9368838).
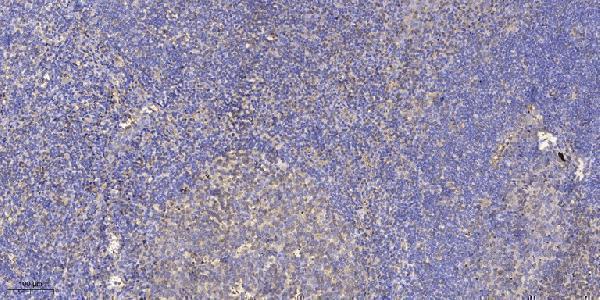
| Sample | Paraffin-embedded human tonsil tissue; fixative not specified (datasheet A09806-1) |
| Fixation | Image fixative and duration unreported (datasheet A09806-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Tris-EDTA pH 9.0 (datasheet A09806-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-UBE2G1, 1:100-1:300 (datasheet A09806-1) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | UBE2G1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control. |
Expect predominantly cytoplasmic UBE2G1 staining in paraffin sections (HPA tissue IHC: general cytoplasmic expression). High staining is reported in glandular cells of the adrenal gland, appendix, colon and duodenum, among other cell populations (HPA tissue IHC). UBE2G1 has no transmembrane segment (UniProt P62253 topology). HPA rates its tissue IHC profile Approved, with medium agreement between staining and RNA data; external verification is pending (HPA tissue IHC).
| Cytoplasmic chromogen in glandular cells of colon or duodenum, with discernible cell boundaries. | This fits the reported compartment and cell types; HPA scores these glandular cells High (HPA tissue IHC). Compare staining with the section’s morphology and controls. An HPA level describes an observed pattern, not a required intensity for every cell or staining run. |
| Signal confined to cell membranes, lumens or extracellular material, with little cytoplasmic staining. | That distribution conflicts with general cytoplasmic tissue staining (HPA tissue IHC) and the absence of a transmembrane segment (UniProt P62253 topology). Check section morphology and detection controls before treating the pattern as UBE2G1. |
| Strong chromogen in unexpected cells while an expected cell population is weak. | Investigate antibody cross-reactivity or endogenous detection activity. UBE2G1 is widely expressed (UniProt P62253 tissue specificity), so an unexpected cell type alone cannot prove a false positive. Compare cell-specific staining with HPA observations and appropriate controls. |
| Diffuse colour covers tissue, empty spaces and cell-free areas. | Poorly localized colour makes the cytoplasmic pattern difficult to assess (HPA tissue IHC: general cytoplasmic expression). As general IHC practice, inspect reagent-only or primary-omission controls, blocking and wash steps for background before scoring cells. |
| No staining in a colon glandular-cell section expected to be positive. | HPA reports High staining in colon glandular cells (HPA tissue IHC), making them a useful comparison. First verify that the relevant cells are present and the detection control worked; an absent signal alone does not establish absent UBE2G1. |
| Tissue and cell selection | HPA reports High staining in adrenal, appendix, colon and duodenum glandular cells; bone marrow hematopoietic cells; caudate neuronal cells; and cerebellar granular-layer cells (HPA tissue IHC). Select a comparison section whose expected cells can be identified morphologically. |
| Skeletal muscle expectation | UniProt describes widespread expression, mainly in skeletal muscle (UniProt P62253 tissue specificity), and HPA calls skeletal-muscle RNA tissue-enhanced (HPA tissue IHC). The supplied HPA tissue IHC observations give no skeletal-muscle staining level, so they do not establish its expected chromogen intensity. |
| Topology and antigen interpretation | UBE2G1 has no transmembrane segment and has a UBC core at residues 5–166 (UniProt P62253 topology/domains). The supplied record gives no antibody epitope, so these facts cannot predict whether a particular retrieval condition will expose it. |
| Evidence strength | HPA lists HPA045681 and HPA050551 as IHC Approved (HPA antibodies). The tissue profile has medium agreement with RNA data and awaits external verification (HPA tissue IHC). Treat the reported distribution as a reference for interpretation, with controls for the assay at hand. |
| IF/ICC Q: Should nuclear fluorescence be treated as the expected IHC result? | A: HPA reports approved nucleoplasm and cytosol localization by ICC-IF (HPA subcellular). For paraffin IHC, use its reported general cytoplasmic pattern as the primary comparison (HPA tissue IHC); assess any nuclear chromogen with controls rather than automatically calling it artefact. |
| Situation | Likely cause | Next action |
|---|---|---|
| Colon glandular cells lack signal. | The expected cells may be absent from the examined area, or an assay step may have failed; HPA reports High staining in these cells (HPA tissue IHC). | Locate intact glands, check the positive and detection controls, then review retrieval, primary-antibody dilution and incubation as general IHC troubleshooting. No UBE2G1-specific retrieval or dilution condition is supplied. |
| A strong membrane rim replaces cytoplasmic staining. | The pattern differs from general cytoplasmic tissue staining (HPA tissue IHC) and lacks support from UBE2G1 topology (UniProt P62253: no transmembrane segment). | Inspect morphology and controls; reassess antibody-specific staining and chromogen deposition before assigning the rim to UBE2G1. |
| Unexpected cells stain strongly. | Cross-reactivity or endogenous detection activity is possible, but widespread expression limits conclusions from cell identity alone (UniProt P62253 tissue specificity). | Compare the same section with primary-omission and detection controls, then check whether cytoplasmic staining also appears in the HPA-reported cell populations (HPA tissue IHC). |
| Colour is diffuse across tissue and blank areas. | Background from detection reagents or insufficient blocking or washing can obscure cellular localization; the reference tissue pattern is cytoplasmic (HPA tissue IHC). | Use primary-omission and reagent controls, inspect blank areas, and adjust blocking or washing according to the assay’s general IHC workflow before scoring intensity. |
| Nuclear chromogen appears alongside cytoplasmic staining. | Nucleoplasm and cytosol are both approved ICC-IF locations (HPA subcellular), while the supplied tissue IHC profile describes general cytoplasmic expression (HPA tissue IHC). | Record the compartments separately and review controls and morphology. Do not infer that ICC-IF localization alone validates a nuclear paraffin-IHC signal. |
| Signal differs between two antibodies or sections. | HPA lists both supplied antibodies as IHC Approved, while the tissue profile has medium staining–RNA agreement and awaits external verification (HPA antibodies; HPA tissue IHC). | Compare the same cell populations and controls across sections, document any compartment difference, and avoid treating one discrepant stain as definitive localization. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | High | Protein (IHC) | HPA → |
| Caudate | Neuronal cells | High | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: UBE2G1 is detected in all 44 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Troubleshoot UBE2G1 staining in paraffin sections by checking retrieval, staining controls, compartment patterns and cell-specific scoring.
A09806-1 has a human tonsil paraffin-section IHC image (IHC image caption) and lists IF and human, mouse and rat reactivity (catalog: applications; catalog: reactivity).
A09806-1 was imaged by IHC on paraffin-embedded human tonsil at 1:200, following Tris-EDTA retrieval at pH 9.0 (IHC image caption). It lists IF and human, mouse and rat reactivity, but supplies no IF image (catalog: applications; catalog: reactivity; catalog: IF image alts).
Which to pick: For tissue IHC, choose A09806-1 for paraffin sections using the human tonsil example as a starting point; the fixative is unreported (IHC image caption). For IF/ICC, A09806-1 lists IF at 1:50, but ICC is not listed and no IF image is supplied; its host is rabbit and clonality is unreported (catalog: applications; catalog: IF dilution; catalog: IF image alts; catalog: host and clone). For cross-species work, A09806-1 lists human, mouse and rat reactivity, while its supplied IHC image documents human tissue only (catalog: reactivity; IHC image caption).