UBXN1 / UBX domain-containing protein 1 · IHC design guide

Design Immunohistochemistry for UBXN1

Plan UBXN1 paraffin IHC using the catalog antibody at 2–5 μg/ml (datasheet A09683-1). Use trophoblastic cells or cells in seminiferous ducts as positive controls, and assess cytoplasmic and nuclear staining (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for UBXN1 (IHC for UBXN1): expected localisation Cytoplasmic and nuclear staining in tissue (HPA tissue IHC), antibody A09683-1, validated IHC image, and IHC protocol steps
Printable UBXN1 IHC protocol sheet — expected localisation Cytoplasmic and nuclear staining in tissue (HPA tissue IHC), antibody A09683-1, controls and protocol steps. Open the full UBXN1 IHC guide →

UBXN1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and nuclear staining in tissue (HPA tissue IHC)
Staining pattern Cytoplasmic and nuclear staining in most tissues (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A09683-1)
Positive control ⓘ Placenta+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Staining has medium consistency with RNA data (HPA tissue IHC)
Regulation Induced following viral infection (UniProt)
Isoform / epitope 2 isoforms; verify epitope coverage (UniProt)
Section 1

Recommended UBXN1 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet A09683-1) with published UBXN1 staining of patient glioma sections (PMC8778801).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human tonsil tissue; fixative not specified (datasheet A09683-1)
FixationImage fixative and duration unreported (datasheet A09683-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A09683-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A09683-1)
Primary antibodyRabbit anti-UBXN1, 2-5 μg/ml (datasheet A09683-1)
Primary incubationOvernight at 4 °C (datasheet A09683-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A09683-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultUBXN1-positive staining in trophoblastic cells of placenta (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic and nuclear expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 for the catalog antibody (datasheet A09683-1); the published glioma excerpt does not specify retrieval (PMC8778801).
Section 2

What Is the Expected UBXN1 Staining Pattern?

UBXN1 is annotated as cytoplasmic, with no transmembrane segment (UniProt Q04323); HPA reports cytoplasmic and nuclear staining in most tissues (HPA tissue IHC). Expect staining in trophoblastic cells of placenta and cells in testicular seminiferous ducts, both scored High (HPA tissue IHC). Treat this as a reference pattern rather than definitive specificity: HPA rates tissue staining Approved, with medium consistency against RNA data and external verification pending (HPA tissue IHC).

What am I looking at on my slide?
Trophoblastic cells in placenta or cells in testicular seminiferous ducts show strong cellular staining (HPA tissue IHC).This matches HPA's High cell-specific observations (HPA tissue IHC). Check cytoplasmic staining first, consistent with UniProt's location and HPA's tissue profile (UniProt Q04323; HPA tissue IHC). Nuclear staining can occur in tissue sections, so it does not alone disqualify the result (HPA tissue IHC).
Signal is confined to cell surfaces, lumens or extracellular material, with little cellular staining.That distribution conflicts with the reported cytoplasmic location and lack of a transmembrane segment (UniProt Q04323). Review morphology and detection controls before calling it UBXN1; deposited chromogen or nonspecific staining can mimic a positive result (general IHC practice).
Strong staining dominates an HPA Not detected cell population, such as adipocytes or cardiomyocytes (HPA tissue IHC).The cell-specific mismatch raises concern for cross-reactivity or endogenous detection activity (general IHC practice; HPA tissue IHC). Confirm cell identity and compare a no-primary control. Do not treat an entire tissue as negative when HPA's observation names a particular cell type (HPA tissue IHC).
Diffuse color covers stroma, blank areas or many cell types without clear cellular boundaries.This is difficult to score as UBXN1 because HPA describes staining by identifiable cells and compartments (HPA tissue IHC). Check the no-primary control, blocking and wash conditions for background from the detection workflow (general IHC practice).
No convincing staining appears in placental trophoblastic cells or testicular seminiferous-duct cells (HPA tissue IHC).Both are reported High and can serve as reference-positive cell populations (HPA tissue IHC). First verify that those cells are present and intact; then review retrieval, primary antibody dilution and detection performance as general IHC workflow checks. HPA does not establish UBXN1-specific fixation sensitivity.
💡Expected UBXN1 appearanceA convincing positive result shows High cellular staining in placental trophoblastic cells or testicular seminiferous-duct cells, principally cytoplasmic with possible nuclear staining; surface-only or diffuse acellular color is suspect (HPA tissue IHC; UniProt Q04323).
How each factor affects the staining
Reference cell populationPlacental trophoblastic cells and testicular seminiferous-duct cells are High; adrenal glandular and bronchial respiratory epithelial cells are Medium (HPA tissue IHC). Judge intensity within the named cells, not across the whole section.
Compartment and topologyUniProt places UBXN1 in the cytoplasm and reports no transmembrane segment (UniProt Q04323). HPA tissue IHC also reports nuclear expression, so nuclear color requires context rather than automatic rejection (HPA tissue IHC).
Antibody evidenceHPA012669 is Approved for IHC, while the overall tissue profile has medium agreement with RNA data and awaits external verification (HPA antibodies; HPA tissue IHC). An unexpected pattern warrants an independent specificity check.
Isoforms and epitopeUniProt lists two isoforms and UBA and UBX domains (UniProt Q04323). The supplied record gives no antibody epitope, so isoform recognition and any retrieval-dependent epitope effect cannot be predicted from it.
IF/ICC Q: where should signal appear?A: Mainly in the cytosol; additional nucleoplasmic localization is uncertain (HPA subcellular ICC-IF). That IF observation helps assess compartment, while the paraffin IHC tissue profile governs this guide's cell-specific expectations (HPA tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Reference-positive cells show no signal.The expected cells may be absent, or retrieval, primary incubation or detection may have failed (HPA tissue IHC; general IHC practice).Identify trophoblastic or seminiferous-duct cells on the counterstain; check the run's positive control, then review retrieval and antibody dilution against the validated IHC procedure (general IHC practice).
A nominally negative section contains positive cells.HPA's Not detected calls apply to named populations, such as adipocytes or cardiomyocytes, rather than every cell in their tissues (HPA tissue IHC).Score the specified cells separately from vessels and other structures; compare the distribution with HPA's cell-level observations before changing the assay (HPA tissue IHC).
Nuclei stain more strongly than cytoplasm.HPA reports nuclear staining in tissues, although UniProt annotates cytoplasm and HPA's additional nucleoplasmic IF location is uncertain (HPA tissue IHC; UniProt Q04323; HPA subcellular ICC-IF).Check whether staining remains cell-associated in expected populations, then compare with a no-primary control; avoid rejecting nuclear signal solely by compartment (HPA tissue IHC; general IHC practice).
Strong color appears on surfaces or outside cells.The pattern conflicts with UBXN1's cytoplasmic annotation and lack of a transmembrane segment; background is possible (UniProt Q04323; general IHC practice).Inspect the no-primary control and tissue morphology, then review blocking, washing and chromogen development before scoring those deposits as positive (general IHC practice).
Color is widespread and tissue detail is obscured.Excess detection background or concentrated primary antibody can reduce cell-level interpretability (general IHC practice).Compare no-primary and reference-positive sections; review dilution, blocking, washes and development time while preserving a readable counterstain (general IHC practice).
A known-positive section is weak but controls stain.Biological variation or assay conditions may explain the discrepancy; HPA's tissue profile has only medium RNA-staining consistency (HPA tissue IHC).Confirm the named positive cells and their preservation, repeat with the validated IHC conditions, and report weak staining without claiming a UBXN1-specific fixation effect (HPA tissue IHC; general IHC practice).

Sample controls for UBXN1 IHC & IF

🧪Run placenta first and look for UBXN1 staining in trophoblastic cells (HPA: High); use adipose tissue adipocytes as the negative tissue comparator (HPA: Not detected). On the placenta slide, use cells without discernible specific cytoplasmic staining as an internal background reference, without assuming they lack UBXN1 (UniProt Q04323: Cytoplasm; HPA subcellular: supported cytosol).
Positive control tissue: Placenta (Trophoblastic cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show UBXN1 in SH-SY5Y, SK-MEL-30, U2OS, with annotated localisation: Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; a rabbit IgG control matched to the primary’s clonality where applicable (selected-SKU caption: rabbit anti-UBXN1); and a UBXN1 knockout biological control or a validated peptide-block control. For chromogenic placenta IHC, block endogenous peroxidase and check blood-rich areas for background staining (selected-SKU caption: peroxidase secondary and DAB detection; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported in the supplied evidence, and the selected-SKU paraffin-section caption does not state the fixative (selected-SKU caption: fixative not stated). The caption uses heat retrieval in EDTA at pH 8.0, but does not establish that retrieval is required; it reports 2 μg/ml primary antibody overnight at 4°C for its tonsil section (selected-SKU caption). Frozen sections and IF cannot be ranked as easier from the supplied evidence; placenta blood-rich areas warrant background review for chromogenic staining and autofluorescence if IF is used (standard IHC/IF practice).

HPA tissue IHC evidence for UBXN1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Placenta Trophoblastic cells High Protein (IHC) HPA →
Testis Cells in seminiferous ducts High Protein (IHC) HPA →
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Breast Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Hippocampus Glial cells Not detected Protein (IHC) HPA →
Salivary gland Glandular cells Not detected Protein (IHC) HPA →
Section 3

Advanced UBXN1 IHC Tips

Troubleshoot UBXN1 chromogenic IHC against the catalog antibody’s paraffin tonsil example and the reported tissue and subcellular patterns (datasheet A09683-1; HPA).

What retrieval should I try first when UBXN1 staining is weak?
Begin with heat-mediated retrieval in EDTA at pH 8.0 for the catalog antibody on paraffin sections (datasheet A09683-1). The supplied tonsil example uses this retrieval, followed by 10% goat serum blocking and 2 µg/ml primary antibody overnight at 4°C (datasheet A09683-1). If signal is weak, compare shorter and longer heating intervals on matched sections while keeping EDTA and detection conditions fixed (standard IHC practice). Check tissue integrity and background before increasing primary concentration, because excessive heating can damage morphology and increase nonspecific staining (standard IHC practice).
Could fixation explain inconsistent UBXN1 staining between paraffin samples?
Target-specific fixation sensitivity is unknown: the selected paraffin tonsil caption does not report a fixative (datasheet A09683-1). Record the actual fixative, fixation duration, tissue thickness and processing history for each sample, then compare matched sections where those variables differ (standard IHC practice). For new specimens, follow the laboratory’s validated paraffin fixation workflow and assess morphology alongside staining before attributing weak signal to a UBXN1-specific fixation effect (standard IHC practice). Use the documented EDTA pH 8.0 retrieval and 2 µg/ml overnight primary condition as an initial assay reference (datasheet A09683-1).
Should nuclear UBXN1 staining be scored alongside cytoplasmic staining?
Expect cytoplasmic staining as the principal pattern: UBXN1 is annotated in the cytoplasm, and cytosolic localisation is supported (UniProt Q04323; HPA subcellular). Nuclear staining deserves separate review because tissue IHC reports cytoplasmic and nuclear expression in most tissues, while nucleoplasmic localisation in cell imaging remains uncertain (HPA tissue IHC; HPA subcellular). Score cytoplasmic and nuclear compartments separately, using the same thresholds across sections and checking each against the negative control (standard IHC practice). Diffuse surface outlining would be unexpected for a protein with no transmembrane segment; investigate such staining before counting it as UBXN1 (UniProt Q04323 topology; standard IHC practice).
How do isoforms and epitope placement affect interpretation of weak staining?
UBXN1 has 2 annotated isoforms, but the supplied antibody caption does not identify its epitope or establish isoform selectivity (UniProt Q04323; datasheet A09683-1). Its UBA domain spans residues 2–42 and its UBX domain spans 211–293, so epitope mapping would help interpret any isoform-dependent staining (UniProt Q04323). Reported modified residues include phosphoserines near 199–200 and phosphothreonines at 207 and 229; their effect on this antibody’s IHC signal is unknown (UniProt Q04323; datasheet A09683-1). If patterns differ across specimens, first compare processing and controls, and avoid assigning a difference to an isoform or modification without epitope information (standard IHC practice).
How should I investigate the IHC pattern with companion immunofluorescence?
Treat companion IF as a separate assay: the selected catalog evidence documents paraffin IHC conditions, without establishing IF performance for this antibody (datasheet A09683-1). For a placenta comparison, multiplex UBXN1 with a validated trophoblastic cell marker, since trophoblastic cells show high tissue staining, and check whether signals occupy the expected cells (HPA tissue IHC; standard IF practice). Choose a spectrally separated, preferably far-red fluorophore after inspecting tissue autofluorescence and single-label controls (standard IF practice). Permeabilise sufficiently to access a cytosolic epitope, while titrating detergent against preserved morphology; the antibody’s exact epitope remains unspecified (UniProt Q04323 topology; HPA subcellular; datasheet A09683-1; standard IF practice).
How can I reduce diffuse brown staining without losing UBXN1 signal?
First compare an adjacent no-primary section with the stained section to identify signal from detection reagents or tissue chemistry (standard IHC practice). The demonstrated workflow uses 10% goat serum blocking, a peroxidase-conjugated secondary and DAB development, so reproduce its blocking step before changing primary concentration (datasheet A09683-1). Include an endogenous peroxidase block and inspect pigment or precipitate under the microscope; these are general chromogenic IHC controls, not UBXN1-specific findings (standard IHC practice). If diffuse colour persists, shorten DAB development or titrate the secondary on matched sections, then reassess whether cytoplasmic staining remains distinguishable from background (standard IHC practice; HPA subcellular).
What scoring method best compares UBXN1 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring; cytoplasmic signal is the primary localisation, while nuclear signal should be recorded separately (UniProt Q04323; HPA subcellular; standard IHC practice). For each compartment, report percentage of positive cells and staining intensity, or calculate an H-score from intensity categories 0–3 for a possible range of 0–300 (standard IHC practice). Normalise positive-cell counts to the number of eligible cells, or area-based counts to analysed tissue area in mm², excluding folds and necrosis (standard IHC practice). Keep acquisition, DAB development and thresholds consistent across batches, and document the control used to set positivity (standard IHC practice).
How do I distinguish credible UBXN1 positivity from staining artefacts?
Give most weight to reproducible cytoplasmic staining in intact cells, because UBXN1 is annotated as cytoplasmic and cytosolic localisation is supported (UniProt Q04323; HPA subcellular). Tissue context matters: trophoblastic cells in placenta show high staining, whereas adipocytes in adipose tissue are reported as not detected; neither pattern alone validates antibody specificity (HPA tissue IHC; standard IHC practice). Review unexpected membrane outlines, tissue edges, folds and necrotic regions against adjacent morphology and a no-primary control before scoring them (UniProt Q04323 topology; standard IHC practice). Persistent brown signal in the no-primary control suggests endogenous enzyme activity or detection background, and uncertain nuclear staining warrants separate confirmation (standard IHC practice; HPA subcellular).
Boster reagents

Best UBXN1 / UBX domain-containing protein 1 IHC Antibodies

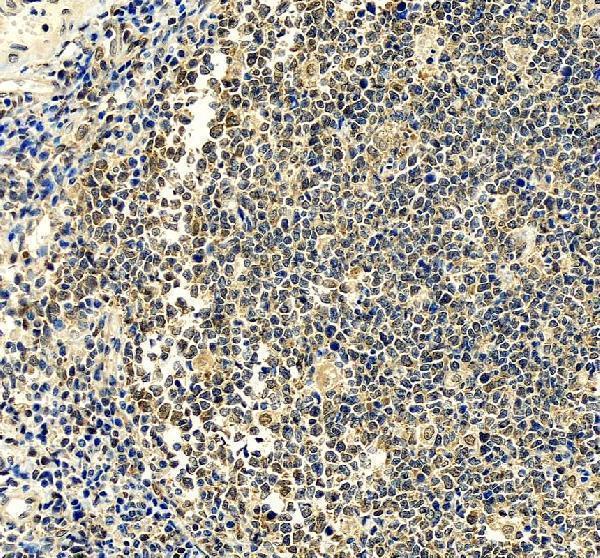
A09683-1 has real IHC data from a paraffin-embedded human tonsil section (catalog image caption). Its listed reactivity covers human, mouse, and rat (catalog reactivity).

Real IHC data IHC analysis of UBXN1 using anti-UBXN1 antibody (A09683-1). UBXN1 was detected in a paraffin-embedded section of human tonsil tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-UBXN1 Antibody (A09683-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-UBXN1 Antibody ®
Cat # A09683-1

A09683-1 is shown staining a paraffin-embedded human tonsil section by IHC (catalog image caption). Its caption documents EDTA pH 8 retrieval, 2 μg/ml primary antibody, and DAB detection; the fixative is unreported (catalog image caption).

Which to pick: Choose A09683-1 for paraffin-section IHC based on its own human-tonsil image (catalog image caption). No SKU in the payload has a listed IF/ICC application or IF image, so there is no supported IF/ICC pick (catalog applications and IF images). A09683-1 is a polyclonal antibody listed for human, mouse, and rat IHC (catalog dilution and reactivity), although its supplied image documents human tissue only (catalog image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q04323 (UBXN1_HUMAN, UBX domain-containing protein 1).
  2. Human Protein Atlas. UBXN1 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. UBXN1 subcellular location (ICC-IF): Mainly localized to the cytosol. In addition localized to the nucleoplasm..
  4. Human Protein Atlas. UBXN1 antibody validation summary (2 antibodies).
  5. YTHDF2 facilitates UBXN1 mRNA decay by recognizing METTL3-mediated m(6)A modification to activate NF-κB and promote the malignant progression of glioma. Journal of hematology & oncology 2021 — PMC8272379.
  6. LncRNA PRADX-mediated recruitment of PRC2/DDX5 complex suppresses UBXN1 expression and activates NF-κB activity, promoting tumorigenesis. Theranostics 2021 — PMC7977445.
  7. PTRF/Cavin-1 as a Novel RNA-Binding Protein Expedites the NF-κB/PD-L1 Axis by Stabilizing lncRNA NEAT1, Contributing to Tumorigenesis and Immune Evasion in Glioblastoma. Frontiers in immunology 2021 — PMC8778801.
  8. PubMed PMID:15489334 — UniProt-cited evidence.
  9. PubMed PMID:15362974 — UniProt-cited evidence.
  10. PubMed PMID:18775313 — UniProt-cited evidence.