VIRMA / Protein virilizer homolog · IHC design guide

Design Immunohistochemistry for VIRMA

Plan chromogenic VIRMA IHC around nuclear and cytoplasmic staining (HPA tissue IHC). Use strongly stained adrenal or stomach glandular cells as positive references, and score nuclear and cytoplasmic signal separately (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for VIRMA (IHC for VIRMA): expected localisation Nuclear and cytoplasmic tissue staining (HPA tissue IHC), antibody A32283-1, validated IHC image, and IHC protocol steps
Printable VIRMA IHC protocol sheet — expected localisation Nuclear and cytoplasmic tissue staining (HPA tissue IHC), antibody A32283-1, controls and protocol steps. Open the full VIRMA IHC guide →

VIRMA Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear and cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern General nuclear and cytoplasmic staining across tissues (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A32283-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Heart muscle+3 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Staining and RNA show only medium consistency (HPA tissue IHC)
Regulation No specific regulation reported (UniProt)
Isoform / epitope 4 isoforms; check epitope coverage across variants (UniProt)
Section 1

Recommended VIRMA IHC & IF Protocols

The catalog antibody protocol is followed by four published VIRMA IHC protocols for oral, lung, nasopharyngeal and testicular tumors (PMC12226839; PMC12010004; PMC10235437; PMC6416960).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human bladder epithelial carcinoma tissue; fixative not specified (datasheet A32283-1)
FixationImage fixative and duration unreported (datasheet A32283-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A32283-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A32283-1)
Primary antibodyRabbit anti-VIRMA, 2-5 μg/ml (datasheet A32283-1)
Primary incubationOvernight at 4 °C (datasheet A32283-1)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A32283-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultVIRMA-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General nuclear and cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval (datasheet: A32283-1). The testicular tumor study also used EDTA retrieval but did not report its pH (PMC6416960).
Section 2

What Is the Expected VIRMA Staining Pattern?

VIRMA is mainly nuclear, with a smaller cytoplasmic fraction (UniProt Q69YN4); tissue IHC shows general nuclear and cytoplasmic expression (HPA tissue IHC). Expect strong staining in adrenal and stomach glandular cells (HPA: High). VIRMA has no transmembrane segment (UniProt Q69YN4 topology). HPA rates the tissue staining Approved, with medium consistency between staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Nuclear staining, sometimes with cytoplasmic staining, in adrenal or stomach glandular cells.This fits VIRMA localisation (UniProt Q69YN4; HPA tissue IHC). HPA reports High staining in these cells (HPA: High); assess the nuclear signal within the identified glandular cells.
Predominantly cell-surface or extracellular staining, with little nuclear signal.That distribution conflicts with the reported mainly nuclear location and lack of a transmembrane segment (UniProt Q69YN4). Check morphology and staining controls before attributing it to VIRMA; a chromogenic deposit alone does not establish target identity (general IHC practice).
Strong staining in cardiomyocytes, liver cholangiocytes, or salivary gland glandular cells.HPA reports VIRMA Not detected in those specific cell populations (HPA tissue IHC). Consider cross-reactivity or endogenous detection activity, then check controls; the observation does not establish staining throughout the named tissue.
Diffuse colour across tissue and empty areas, without clear cellular boundaries.This is more consistent with background than an interpretable nuclear and cytoplasmic pattern (HPA tissue IHC; general IHC practice). Inspect no-primary and detection controls to distinguish nonspecific antibody binding from detection-related deposit.
No staining in adrenal or stomach glandular cells.These are HPA High reference populations (HPA tissue IHC), so a blank result calls for a technical check before a biological interpretation. Confirm that the expected cells are present and that detection controls worked (general IHC practice).
💡Expected VIRMA appearanceA positive IHC result shows strong staining in adrenal or stomach glandular cells, centred on nuclei with possible cytoplasmic signal (HPA: High; HPA tissue IHC; UniProt Q69YN4); isolated surface staining or diffuse deposit without cellular localisation warrants control checks (UniProt Q69YN4 topology; general IHC practice).
How each factor affects the staining
Subcellular localisationUniProt places VIRMA in nuclear speckles and nucleoplasm, with some cytoplasmic fraction (UniProt Q69YN4). HPA tissue IHC reports general nuclear and cytoplasmic expression (HPA tissue IHC). Judge compartment and cell identity together.
Reference cell populationsAdrenal and stomach glandular cells are High; adipocytes in adipose tissue and breast, appendix glandular cells, bone marrow hematopoietic cells, bronchial basal cells, and caudate glial cells are Medium (HPA tissue IHC). Use the identified cell population when comparing slides.
Antibody evidenceHPA031530 has Approved IHC status (HPA antibodies). The overall tissue profile has medium consistency with RNA expression (HPA tissue IHC). Treat the pattern as a reference for interpretation, with controls for any unexpected result.
Isoforms and epitope coverageUniProt lists four VIRMA isoforms (UniProt Q69YN4). The supplied record does not map this antibody's epitope to them (HPA antibodies); do not infer that every isoform produces the same IHC signal.
IF/ICC: what pattern should I expect?HPA ICC-IF reports mainly nuclear bodies, with additional nucleoplasmic signal; its antibody ICC status is Supported (HPA subcellular; HPA antibodies). This is a localisation reference, not a required punctate appearance for chromogenic tissue IHC.
Detection backgroundEndogenous detection activity can contribute colour independently of primary-antibody binding (general IHC practice). Use appropriate detection controls when colour appears outside the expected cells or compartments.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Adrenal or stomach glandular cells are blank.The slide may lack the relevant cells, or an IHC step may have failed; these populations are High references (HPA tissue IHC; general IHC practice).Verify cell identity and tissue integrity, then review retrieval, primary incubation, detection reagents, and a working positive control (general IHC practice).
Signal is predominantly membranous.That conflicts with VIRMA's mainly nuclear location and absence of a transmembrane segment (UniProt Q69YN4). Nonspecific staining is one possibility (general IHC practice).Check a no-primary control, inspect the cellular boundaries, and reassess staining with an independently supported control if available (general IHC practice).
Strong signal appears in an HPA Not detected cell population.For cardiomyocytes, cholangiocytes, salivary gland glandular cells, and smooth muscle cells, that differs from the reported pattern (HPA tissue IHC); cross-reactivity or detection activity may contribute (general IHC practice).Confirm the cell type and compare no-primary and detection controls before calling the signal VIRMA (general IHC practice).
Diffuse background obscures nuclei.Nonspecific binding, incomplete blocking, or detection-related deposit may obscure the expected cellular pattern (HPA tissue IHC; general IHC practice).Compare no-primary controls and review blocking, primary-antibody concentration, washing, and detection conditions (general IHC practice).
Cytoplasmic signal seems stronger than nuclear signal.Some cytoplasmic VIRMA is reported, but UniProt describes VIRMA as mainly nuclear (UniProt Q69YN4). Background or cell-identification errors are possible (general IHC practice).Check nuclear counterstain, cell boundaries, and controls; interpret a reproducible cytoplasmic signal in its cell context (general IHC practice).
The IHC slide lacks distinct nuclear puncta seen by IF/ICC.HPA ICC-IF reports nuclear bodies and nucleoplasm (HPA subcellular), while HPA tissue IHC describes general nuclear and cytoplasmic staining (HPA tissue IHC).Score the chromogenic tissue pattern by its compartment and cell type; use the separate IF/ICC guide for fluorescent localisation assessment.

Sample controls for VIRMA IHC & IF

🧪Run stomach first and score its glandular cells for VIRMA staining (HPA: High in stomach glandular cells). Use salivary glandular cells as the negative tissue comparator (HPA: Not detected in salivary glandular cells); on the stomach slide, assess other cell types as potential internal negative cells, but verify their staining rather than assuming they are negative (HPA: stomach result specifies glandular cells).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Heart muscle (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show VIRMA in A-431, U-251MG, U2OS, with annotated localisation: Nuclear bodies (supported) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and concentration-matched rabbit IgG isotype controls, plus VIRMA-knockout material as a biological negative (selected-SKU tissue-IHC caption: rabbit primary; standard IHC practice). For stomach SABC/DAB staining, check endogenous peroxidase and biotin background before scoring glandular cells (selected-SKU tissue-IHC caption: SABC/DAB; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A32283-1 paraffin-section caption does not state a fixative (selected-SKU tissue-IHC caption). The caption uses heat-mediated EDTA retrieval at pH 8.0, but does not establish that retrieval is required; assess background in stomach glandular cells when interpreting the SABC/DAB signal (selected-SKU tissue-IHC caption; standard IHC practice). Is frozen section or IF/ICC easier? The supplied evidence does not establish either as easier; the separate IF/ICC guide can use the supported nuclear-body and additional nucleoplasmic pattern for localisation assessment (HPA subcellular).

HPA tissue IHC evidence for VIRMA

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Stomach Glandular cells High Protein (IHC) HPA →
Adipose tissue Adipocytes Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Salivary gland Glandular cells Not detected Protein (IHC) HPA →
Smooth muscle Smooth muscle cells Not detected Protein (IHC) HPA →
Section 3

Advanced VIRMA IHC Tips

Troubleshoot VIRMA staining in paraffin sections by checking retrieval, compartment-specific signal, controls, and scoring before interpreting chromogenic results.

Which retrieval conditions should I start with for VIRMA in paraffin sections?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A32283-1). The selected antibody stained a human bladder epithelial carcinoma section after this retrieval, followed by 2 μg/ml primary antibody overnight at 4°C (datasheet A32283-1). If staining is weak, compare a modest range of heating times while keeping buffer, detection chemistry, and section thickness constant; excessive heating can damage morphology (standard IHC practice). Score nuclear signal against a matched section processed without primary antibody, since VIRMA is mainly nuclear and also has a cytoplasmic fraction (UniProt Q69YN4 localisation).
How should I troubleshoot weak VIRMA staining when fixation history varies?
Target-specific fixation sensitivity is unknown: the selected paraffin-section caption does not state a fixative or fixation duration (datasheet A32283-1). Record each specimen’s fixative, duration, and processing history, then compare sections with the same EDTA pH 8.0 retrieval and antibody conditions (datasheet A32283-1; standard IHC practice). Include a well-preserved control section in each run and inspect nuclear morphology before attributing a weak signal to antigen loss (standard IHC practice). Changes in nuclear or cytoplasmic staining cannot establish a VIRMA-specific fixation effect without a controlled fixation comparison (UniProt Q69YN4 localisation; standard IHC practice).
Should VIRMA staining be nuclear, cytoplasmic, or both?
Expect predominantly nuclear staining, with possible cytoplasmic signal: VIRMA occurs in nuclear speckles and nucleoplasm, with a smaller cytoplasmic fraction (UniProt Q69YN4 localisation). Tissue IHC also reports general nuclear and cytoplasmic expression, though its staining and RNA data have medium consistency (HPA tissue IHC). Compare signal within intact cells and distinguish nuclear staining from pigment or chromogen overlying a nucleus in a thick section (standard IHC practice). If a section shows exclusively diffuse cytoplasmic staining, review the no-primary control, section quality, and retrieval before calling it a new localisation pattern (UniProt Q69YN4 localisation; standard IHC practice).
Can isoforms or epitope accessibility explain differing VIRMA staining patterns?
VIRMA has 4 annotated isoforms, but the supplied evidence does not locate this antibody’s epitope within them (UniProt Q69YN4 isoforms; datasheet A32283-1). Therefore, staining cannot identify an isoform or establish whether an unstained cell lacks every VIRMA isoform (UniProt Q69YN4 isoforms; standard IHC interpretation). The protein has no annotated transmembrane segment, and its listed modifications include phosphorylation near the N terminus; neither fact establishes this antibody’s epitope accessibility (UniProt Q69YN4 topology and modified residues). If results differ across sections, check the antibody’s documented immunogen or epitope information before assigning the difference to splicing or modification (standard IHC practice).
How can I assess VIRMA localisation by IF alongside chromogenic IHC?
For IF/ICC, pair VIRMA with a validated marker of the expected cell type, such as a glandular-cell marker when assessing adrenal gland or stomach, and inspect each channel separately (HPA tissue IHC; standard IF practice). Choose a fluorophore away from the specimen’s strongest autofluorescence, often toward the far-red range, and include single-channel controls to assess bleed-through (standard IF practice). Use a permeabilisation condition compatible with access to nuclear epitopes, since VIRMA has no transmembrane segment and is mainly nuclear (UniProt Q69YN4 topology and localisation; standard IF practice). Compare nuclear puncta with the reported nuclear-body and nucleoplasmic locations, without assuming the paraffin-section antibody conditions transfer to IF (HPA subcellular; datasheet A32283-1).
What causes widespread brown background in VIRMA chromogenic IHC?
First compare the stained section with a no-primary control to separate antibody-associated staining from endogenous enzyme activity and nonspecific detection signal (standard IHC practice). The selected paraffin-section example used 10% goat serum, a biotinylated secondary antibody, streptavidin–biotin detection, and DAB (datasheet A32283-1). For persistent background, review serum blocking, washes, endogenous peroxidase blocking, and the detection system’s tissue-dependent background; peroxidase blocking is a general chromogenic IHC step (standard IHC practice). Judge improvements by preservation of nuclear signal and tissue morphology, since VIRMA is mainly nuclear and HPA also reports cytoplasmic expression (UniProt Q69YN4 localisation; HPA tissue IHC).
How should I score VIRMA staining across heterogeneous tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, then report nuclear percent positive and intensity or an H-score on the 0–300 scale (standard IHC scoring; UniProt Q69YN4 localisation). Record cytoplasmic signal separately because VIRMA is mainly nuclear but has a cytoplasmic fraction (UniProt Q69YN4 localisation). Normalise positive-cell counts to the number of evaluable cells in the same annotated region, or report positive-cell density per mm² of evaluable tissue (standard IHC quantification). Apply one threshold and imaging or scoring procedure across specimens, excluding folds, necrosis, and poorly preserved areas while retaining a matched control section (standard IHC practice).
When does apparent VIRMA positivity warrant further validation?
A plausible positive shows reproducible nuclear staining in intact cells, potentially with cytoplasmic signal, rather than signal confined to tissue edges or necrotic regions (UniProt Q69YN4 localisation; standard IHC interpretation). HPA reports high staining in adrenal and stomach glandular cells, while cardiomyocytes and smooth muscle cells were not detected in its listed samples; these are comparison points, not universal controls (HPA tissue IHC). Examine no-primary and peroxidase-control sections when brown signal follows blood-rich areas or persists without primary antibody (standard chromogenic IHC practice). Because HPA rates staining–RNA agreement as medium, corroborate unexpected compartments or cell populations with an independent assay before assigning biological meaning (HPA tissue IHC; standard IHC interpretation).
Boster reagents

Best VIRMA / Protein virilizer homolog IHC Antibodies

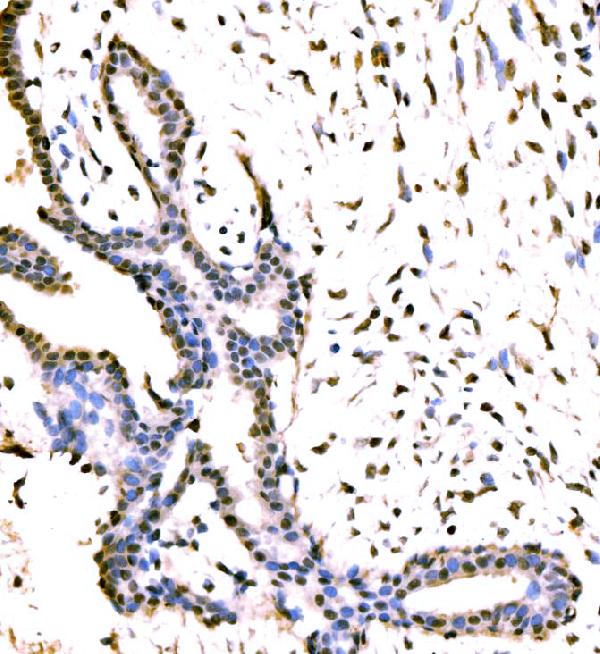
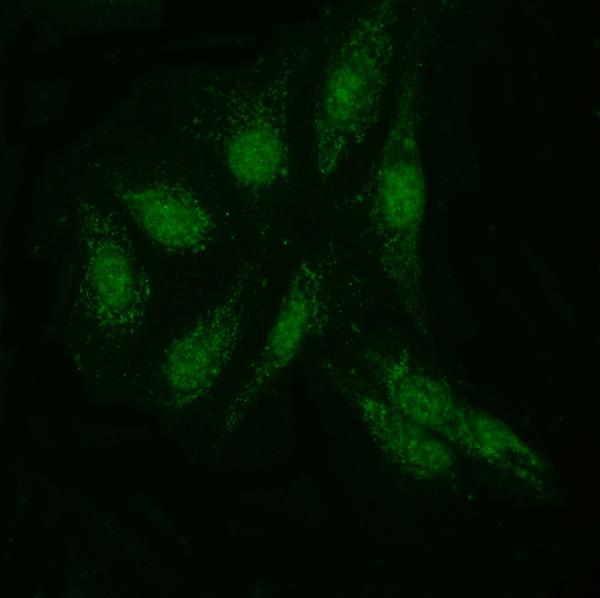
Human paraffin-section IHC data cover bladder epithelial carcinoma and breast cancer tissue; IF data cover U20S cells (A32283-1 image captions).

Real IHC data IHC analysis of KIAA1429/VIRMA using anti-KIAA1429/VIRMA antibody (A32283-1). KIAA1429/VIRMA was detected in a paraffin-embedded section of human bladder epithelial carcinoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-KIAA1429/VIRMA Antibody (A32283-1) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-KIAA1429/VIRMA Antibody ®
Cat # A32283-1

A32283-1 has IHC images from paraffin-embedded human bladder epithelial carcinoma and breast cancer tissue (A32283-1 IHC image captions). A32283-1 is also listed for ICC and IF, with an IF image in U20S cells (catalog applications; A32283-1 IF image caption).

Which to pick: Choose A32283-1 for paraffin-section tissue IHC: its images document EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody (A32283-1 IHC image captions). For IF/ICC, A32283-1 is listed for both applications and has a U20S-cell IF image using 5 μg/ml primary antibody (catalog applications; A32283-1 IF image caption). No cross-species option is documented: A32283-1 lists human reactivity, a rabbit host and no clone designation; its IHC captions do not report a fixative (catalog reactivity/host/clone; A32283-1 IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q69YN4 (VIR_HUMAN, Protein virilizer homolog).
  2. Human Protein Atlas. VIRMA tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. VIRMA subcellular location (ICC-IF): Mainly localized to the nuclear bodies. In addition localized to the nucleoplasm..
  4. Human Protein Atlas. VIRMA antibody validation summary (1 antibodies).
  5. Total m6A RNA levels and VIRMA expression as potential diagnostic and prognostic markers in oral squamous cell carcinoma. Diagnostic pathology 2025 — PMC12226839.
  6. VIRMA promotes NSCLC progression by modifying ADAR m(6)A and increasing the activity of the TGF-β signaling pathway. Scientific reports 2025 — PMC12010004.
  7. VIRMA promotes nasopharyngeal carcinoma, tumorigenesis, and metastasis by upregulation of E2F7 in an m6A-dependent manner. The Journal of biological chemistry 2023 — PMC10235437.
  8. m(6)A RNA modification and its writer/reader VIRMA/YTHDF3 in testicular germ cell tumors: a role in seminoma phenotype maintenance. Journal of translational medicine 2019 — PMC6416960.
  9. PubMed PMID:17974005 — UniProt-cited evidence.
  10. PubMed PMID:15489334 — UniProt-cited evidence.
  11. PubMed PMID:10718198 — UniProt-cited evidence.