WNK1 / Serine/threonine-protein kinase WNK1 · IHC design guide

Design Immunohistochemistry for WNK1

Plan chromogenic WNK1 IHC on paraffin sections using its widespread cytoplasmic tissue pattern (HPA tissue IHC). This guide helps select tissue controls and interpret cell specific gaps in staining (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for WNK1 (IHC for WNK1): expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody PB9964, validated IHC image, and IHC protocol steps
Printable WNK1 IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody PB9964, controls and protocol steps. Open the full WNK1 IHC guide →

WNK1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Widespread cytoplasmic staining across cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet PB9964)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Adipocytes may lack staining despite broad expression (HPA tissue IHC)
Regulation Hyperosmotic stress concentrates WNK1 (UniProt)
Isoform / epitope 6 isoforms; epitope coverage is unspecified (UniProt)
Section 1

Recommended WNK1 IHC & IF Protocols

Compare the catalog antibody’s EDTA pH 8.0 IHC protocol (datasheet: PB9964) with published WNK1 staining methods for mouse brain (PMC12694637) and mouse cortical sections (PMC12923593).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded mouse testis tissue; fixative not specified (datasheet PB9964)
FixationImage fixative and duration unreported (datasheet PB9964); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet PB9964); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet PB9964)
Primary antibodyRabbit anti-WNK1, 0.5-1μg/ml (datasheet PB9964)
Primary incubationOvernight at 4 °C (datasheet PB9964)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet PB9964)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultWNK1-positive staining in lymphoid tissue of appendix (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 heat retrieval for the catalog antibody (datasheet: PB9964). The mouse cortical protocol used citrate retrieval at 100 °C for 20 minutes (PMC12923593).
Section 2

What Is the Expected WNK1 Staining Pattern?

WNK1 is chiefly cytoplasmic, with supported cytosolic localisation by ICC-IF; UniProt also reports nuclear and mitotic-spindle localisation (HPA: subcellular; UniProt Q9H4A3). In paraffin-section IHC, expect staining across many cell types, with stronger signal in selected populations such as esophageal squamous epithelium and splenic red pulp cells (HPA: ubiquitous cytoplasmic expression; High in both populations). WNK1 has no transmembrane segment, so a purely membrane-restricted pattern is unexpected (UniProt Q9H4A3 topology).

What am I looking at on my slide?
Cytoplasmic chromogen in esophageal squamous epithelial cells or splenic red pulp cells; other tissue compartments also stain (HPA: High in these cells; ubiquitous cytoplasmic expression).This fits the reported IHC pattern. Compare intensity within the same section: the tissue profile is widespread, so a stained cell is informative through its compartment and cell identity as well as its colour intensity (HPA: tissue IHC).
Predominantly crisp plasma-membrane outlines or uniform nuclear-only staining in interphase cells (HPA: cytoplasmic IHC profile; UniProt Q9H4A3 topology).Treat the compartment mismatch as suspect and inspect morphology and controls. UniProt reports some nuclear localisation, so isolated nuclear signal is possible; it does not make a nuclear-only field the expected routine IHC pattern (UniProt Q9H4A3 subcellular location).
Strong staining in adipocytes or salivary-gland glandular cells (HPA: Not detected in these cell populations).Consider antibody cross-reactivity, detection background, or mistaken cell identification. A ‘Not detected’ HPA entry is an observed cell-specific result, not proof that every specimen or condition must be negative (HPA: tissue IHC).
Diffuse colour across stroma, lumens, or the whole section, without clear cellular boundaries (HPA: cytoplasmic IHC profile).This does not resemble the reported cell-associated pattern. Check the no-primary control and detection steps for nonspecific signal; assess section quality and counterstain before assigning WNK1-positive cells (general IHC practice).
No cytoplasmic signal in a well-preserved esophageal squamous epithelium section (HPA: High in squamous epithelial cells).First verify that the expected cells are present, then compare a positive-control section and the antibody's documented IHC conditions. Absent signal alone cannot distinguish a technical failure from specimen variation (general IHC practice; HPA: tissue IHC).
💡Expected WNK1 appearanceCall positive when cell-associated cytoplasmic staining is conspicuous in esophageal squamous epithelium or splenic red pulp cells (HPA: High); diffuse section-wide colour or sharp membrane-only outlines are suspect (HPA: cytoplasmic IHC profile; UniProt Q9H4A3 topology).
How each factor affects the staining
Tissue and cell selection (HPA: tissue IHC)Use a reported High population to judge sensitivity, such as esophageal squamous epithelium; adipocytes are listed as Not detected and offer a cell-specific comparison. HPA also reports low staining in hepatocytes, so weak liver signal alone is a poor failure test (HPA: tissue IHC).
Subcellular context (HPA: subcellular; UniProt Q9H4A3)HPA's supported ICC-IF location is cytosol, and its IHC profile is cytoplasmic. UniProt additionally reports nuclear and mitotic-spindle localisation; interpret such findings with cell state and controls rather than expecting every cell to show them (HPA: subcellular and tissue IHC; UniProt Q9H4A3).
Stress-dependent distribution (UniProt Q9H4A3)WNK1 can form and localise to cytoplasmic membraneless compartments during hyperosmotic stress. This supports a biological explanation for some cytoplasmic redistribution, but the supplied HPA tissue profile does not establish a routine punctate paraffin-section pattern (UniProt Q9H4A3; HPA: tissue IHC).
Antibody evidence by application (HPA: antibodies)HPA059157 has Enhanced IHC validation; HPA046541 has Supported ICC validation with no IHC status listed. Those statuses apply to their stated applications and cannot be transferred between IHC and IF (HPA: antibody validation).
Protein forms and topology (UniProt Q9H4A3)UniProt lists 6 isoforms, a single 1–2382 chain, no signal peptide or propeptide, and no transmembrane segment. These facts do not identify which isoforms an antibody detects; consult its documented epitope before interpreting selective staining (UniProt Q9H4A3).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Positive-control epithelium is blank (HPA: High in esophageal squamous epithelial cells).Possible IHC workflow or antibody failure; the HPA level does not identify a target-specific fixation effect (HPA: tissue IHC).Confirm cell identity and section quality, then review the IHC-validated antibody's instructions and run a documented positive control alongside the sample (general IHC practice).
All compartments show similar brown haze, including acellular areas (HPA: cytoplasmic IHC profile).Nonspecific background or detection activity may obscure a cellular pattern (general IHC practice).Inspect the no-primary control, wash and blocking steps, and chromogen development; adjust only with matched controls (general IHC practice).
Adipocytes stain as strongly as the intended positive population (HPA: Not detected in adipocytes).Cross-reactivity, background, or cell misclassification is plausible; HPA's negative call is cell-specific (HPA: tissue IHC).Recheck morphology and compare no-primary and positive-control sections before scoring adipocytes as WNK1-positive (general IHC practice).
Signal forms sharp cell-surface rims with little cytoplasm (HPA: ubiquitous cytoplasmic expression).The pattern conflicts with HPA IHC and the lack of a transmembrane segment; staining artefact is possible (HPA: tissue IHC; UniProt Q9H4A3 topology).Check the no-primary control, tissue edges and detection development; reassess whether cytoplasmic signal is present in known-positive cells (general IHC practice).
A small subset of cells shows nuclear or punctate cytoplasmic signal (UniProt Q9H4A3 subcellular location).UniProt reports nuclear localisation and stress-related cytoplasmic compartments, but these records do not confirm the cause in this section (UniProt Q9H4A3).Record the cell type and distribution; compare controls and the surrounding cytoplasm before treating the unusual pattern as specific (general IHC practice).
An IF/ICC image seems to disagree with the chromogenic IHC result (HPA: subcellular and tissue IHC).The assays and antibody validations differ; HPA reports supported cytosolic ICC-IF, while IHC staining is described as ubiquitous cytoplasmic (HPA: subcellular, tissue IHC, antibodies).Interpret each assay against its own validation and controls. Use the separate IF/ICC guide for that assay's workflow (HPA: antibody validation; general IHC/IF practice).

Sample controls for WNK1 IHC & IF

🧪Run appendix first and score its lymphoid tissue for WNK1 staining (HPA: High in appendix lymphoid tissue). Use adipose tissue adipocytes as a negative comparison (HPA: Not detected in adipocytes); on the appendix slide, unstained cells outside the positive lymphoid areas can show background levels, but HPA does not identify a validated internal negative cell type there.
Positive control tissue: Appendix (Lymphoid tissue, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show WNK1 in A-549, HeLa, U2OS, with annotated localisation: Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only slide, a rabbit IgG control matched to the catalog antibody’s clonality, and WNK1-knockout material if available (selected-SKU caption: rabbit anti-WNK1 antibody). For appendix IHC, quench endogenous peroxidase and check for endogenous biotin before interpreting DAB signal from the biotin-based detection system (selected-SKU caption: biotinylated secondary, SABC and DAB).
⚠️Feasibility: The selected-SKU paraffin-section caption reports no fixative, and the supplied evidence reports no WNK1-specific fixation window or fixation effect (selected-SKU caption: fixative not stated). Heat retrieval in EDTA at pH 8.0 was used for the documented testis IHC example; its necessity in appendix has not been established (selected-SKU caption: heat-mediated EDTA retrieval). That caption supports a paraffin IHC starting point, while the supplied evidence does not establish whether frozen sections or IF would be easier; endogenous peroxidase in lymphoid tissue can complicate DAB interpretation (HPA: High in appendix lymphoid tissue; selected-SKU caption: SABC–DAB detection).

HPA tissue IHC evidence for WNK1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Lymphoid tissue High Protein (IHC) HPA →
Cerebellum Bergmann glia - cytoplasm/membrane High Protein (IHC) HPA →
Cerebral cortex Glial cells High Protein (IHC) HPA →
Esophagus Squamous epithelial cells High Protein (IHC) HPA →
Oral mucosa Squamous epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Colon Endothelial cells Not detected Protein (IHC) HPA →
Ovary Ovarian stroma cells Not detected Protein (IHC) HPA →
Salivary gland Glandular cells Not detected Protein (IHC) HPA →
Soft tissue Chondrocytes Not detected Protein (IHC) HPA →
Section 3

Advanced WNK1 IHC Tips

Use the catalog antibody’s documented paraffin section conditions as the IHC starting point, then assess staining by cell type, compartment, and controls.

What retrieval should I try first when WNK1 staining is weak in paraffin sections?
Start with heat mediated retrieval in EDTA pH 8.0 for paraffin sections (datasheet PB9964). The documented mouse testis image used that retrieval, followed by 10% goat serum blocking and 1 μg/ml primary antibody overnight at 4°C (caption PB9964). If staining remains weak, compare retrieval heating times on adjacent sections while keeping antibody concentration, detection, and imaging conditions fixed (standard IHC practice). Include a section processed without primary antibody to distinguish weak WNK1 staining from detection background (standard IHC practice). Record whether improvement occurs in cytoplasm, the predominant tissue staining compartment, rather than judging total brown signal alone (HPA: ubiquitous cytoplasmic expression).
Could fixation explain weak or uneven WNK1 staining?
The selected paraffin section caption does not report a fixative, so WNK1 specific fixation sensitivity is unknown for this antibody (caption PB9964). Compare sections with documented fixation histories and process them together using EDTA pH 8.0 heat retrieval (datasheet PB9964; standard IHC practice). Keep section thickness, 1 μg/ml primary antibody concentration, and overnight incubation at 4°C consistent with the documented example during that comparison (caption PB9964; standard IHC practice). Check for gradients across each section and include a no primary control before attributing uneven color to fixation (standard IHC practice). Report the actual fixative and fixation duration for every specimen; the caption supplies neither value (caption PB9964).
How should I assess nuclear or punctate WNK1 staining?
Assess cytoplasmic staining first because tissue IHC shows ubiquitous cytoplasmic expression, while the supported cell imaging location is cytosol (HPA: tissue IHC profile; HPA: cytosol supported). Nuclear localisation is reported, and cytoplasmic membraneless compartments can form during hyperosmotic stress (UniProt Q9H4A3: localisation). WNK1 can also localise to the mitotic spindle during mitosis, so annotate cell state when evaluating unusual patterns (UniProt Q9H4A3: localisation). Compare suspicious nuclear or punctate staining with adjacent cells, counterstain, and no primary controls under identical EDTA pH 8.0 retrieval (datasheet PB9964; standard IHC practice). Do not treat a change in compartment alone as evidence of altered kinase activity (standard IHC interpretation).
How can I tell whether this antibody detects all WNK1 isoforms?
WNK1 has 6 listed isoforms, and its protein kinase domain spans residues 221–479 (UniProt Q9H4A3: isoforms and domains). The supplied caption does not identify this antibody’s epitope, so staining cannot establish which isoforms it detects (caption PB9964). Obtain the immunogen or epitope sequence and align it to the isoform sequences before making an isoform specific claim (standard antibody validation practice). If that information is unavailable, score staining as WNK1 immunoreactivity and retain the same antibody and EDTA pH 8.0 retrieval across comparisons (datasheet PB9964; standard IHC practice). Differential staining may also reflect epitope accessibility or sample processing, which requires separate validation (standard IHC practice).
What checks help interpret WNK1 signal in multiplex IF or ICC?
For multiplex IF or ICC, pair WNK1 with a marker identifying the cell population under study; glial cells are one documented high staining population in tissue IHC (HPA: cerebral cortex glial cells, high). Choose a red or far red fluorophore and inspect an unstained specimen in every channel to assess tissue autofluorescence (standard IF practice). WNK1 is primarily cytosolic and has no transmembrane segment, so assess detergent permeabilisation for access to its intracellular epitope; the antibody epitope is not supplied (HPA: cytosol supported; UniProt Q9H4A3: topology; caption PB9964). A comparison around 0.1% detergent can help reveal extraction or redistribution, with matched imaging settings (standard IF practice). Confirm apparent nuclear or punctate signal against single stain controls (standard IF practice).
How do I reduce diffuse brown staining without losing WNK1 signal?
First compare stained sections with a no primary control and inspect whether background follows tissue edges, folds, or all cells indiscriminately (standard IHC practice). The documented workflow uses a biotinylated secondary, streptavidin biotin complex, and DAB, so assess background from the detection sequence as well as primary antibody binding (caption PB9964; standard IHC practice). Apply an appropriate peroxidase block for the DAB workflow and assess endogenous biotin where relevant; these are general controls, not WNK1 specific findings (standard chromogenic IHC practice). Retain the documented 10% goat serum block and 1 μg/ml primary concentration initially (caption PB9964). Then adjust washing or primary concentration one variable at a time while checking cytoplasmic signal (HPA: tissue IHC profile; standard IHC practice).
Which measurements make WNK1 IHC comparisons defensible? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, since tissue IHC describes ubiquitous cytoplasmic expression with cell type differences (HPA: tissue IHC profile). For intensity comparisons, use an H-score from 0–300 or report the percentage of positive cells with a prespecified threshold (standard IHC scoring practice). For spatial questions, report positive cell density per mm² of viable tissue and normalise to the counted area or total cells in that compartment (standard IHC quantification practice). Keep EDTA pH 8.0 retrieval and detection conditions matched across specimens (datasheet PB9964; standard IHC practice). Record cell type separately because HPA reports high staining in glial cells but no detection in adipocytes (HPA: cerebral cortex glial cells, high; HPA: adipocytes, not detected).
How can I distinguish credible WNK1 staining from artefact?
Look for cell associated cytoplasmic staining with clear morphology: this matches the broad tissue profile and supported cytosolic location (HPA: ubiquitous cytoplasmic expression; HPA: cytosol supported). Interpret cell identity explicitly, because HPA reports high staining in squamous epithelial cells of the esophagus but no detection in adipocytes (HPA: esophagus squamous epithelial cells, high; HPA: adipocytes, not detected). Nuclear or punctate staining is possible in specific contexts, but requires morphology and controls before attribution to WNK1 (UniProt Q9H4A3: localisation; standard IHC practice). Exclude staining confined to edges, folds, or necrotic areas, and compare with a no primary control for endogenous enzyme or detection signal (standard chromogenic IHC practice). Consistent staining after EDTA pH 8.0 retrieval strengthens technical reproducibility, not molecular identity by itself (datasheet PB9964; standard IHC interpretation).
Boster reagents

Best WNK1 / Serine/threonine-protein kinase WNK1 IHC Antibodies

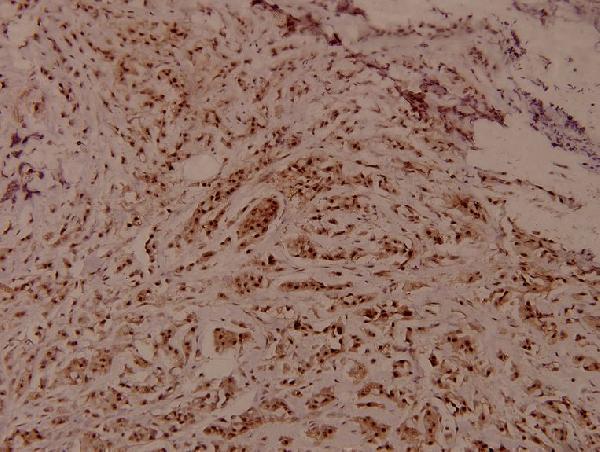
Real IHC images cover paraffin-embedded mouse and rat testis, human intestinal cancer, and human breast carcinoma (PB9964 and A01422T60 image captions). No IF images are supplied (catalog).

Real IHC data IHC analysis of WNK1 using anti-WNK1 antibody (PB9964). WNK1 was detected in a paraffin-embedded section of mouse testis tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1 μg/ml rabbit anti-WNK1 Antibody (PB9964) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-WNK1 Antibody ®
Cat # PB9964
Real IHC data Immunohistochemistry (IHC) analyzes of p-WNK1 (T60) pAb in paraffin-embedded human breast carcinoma tissue at 1:100.
Anti-WNK1 (phospho-T60) Antibody
Cat # A01422T60

PB9964 will render with a mouse testis IHC figure; its other captions show rat testis and human intestinal cancer, all in paraffin-embedded sections (PB9964 image captions). A01422T60 will render with a paraffin-embedded human breast carcinoma IHC figure showing phospho-WNK1 at T60 (A01422T60 image caption).

Which to pick: Choose PB9964 for tissue IHC when detecting WNK1 across human, mouse, or rat samples: its reactivity list covers all three, and its own paraffin-section captions show each species (PB9964 catalog and image captions). Choose A01422T60 when the target is phospho-WNK1 at T60; its own IHC caption shows paraffin-embedded human breast carcinoma, and its catalog lists human, mouse, and rat reactivity (A01422T60 catalog and image caption). Neither SKU lists IF/ICC or supplies an IF image, so there is no supported IF/ICC pick here; the IHC captions do not report a fixative (catalog and image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9H4A3 (WNK1_HUMAN, Serine/threonine-protein kinase WNK1).
  2. Human Protein Atlas. WNK1 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. WNK1 subcellular location (ICC-IF): Localized to the cytosol..
  4. Human Protein Atlas. WNK1 antibody validation summary (2 antibodies).
  5. Potassium-regulated distal tubule WNK bodies are kidney-specific WNK1 dependent. Molecular biology of the cell 2018 — PMC6014176.
  6. Lnc_011797 promotes ferroptosis and aggravates white matter lesions. Neural regeneration research 2026 — PMC12694637.
  7. Knock-down of the long isoform of the WNK1 kinase mitigates the anti-glomerular basement membrane glomerulonephritis in mice. Scientific reports 2026 — PMC12923593.
  8. WNK1 is required during male pachynema to sustain fertility. iScience 2023 — PMC10485039.
  9. PubMed PMID:11571656 — UniProt-cited evidence.
  10. PubMed PMID:22701532 — UniProt-cited evidence.
  11. PubMed PMID:16541075 — UniProt-cited evidence.