This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan paraffin-section IHC for ZC3H12C using the catalog antibody at a starting concentration of 5 μg/mL (datasheet). Compare cytoplasmic staining in respiratory epithelial cells (HPA tissue IHC), while accounting for low consistency between antibody staining and RNA expression (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining in tissue (HPA tissue IHC) | |
| Staining pattern | Respiratory epithelial cells show high cytoplasmic staining (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Bronchus+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Staining has low consistency with RNA expression (HPA tissue IHC) | |
| Regulation | Expression regulation is unreported (UniProt) | |
| Isoform / epitope | 2 isoforms; verify antibody epitope coverage (UniProt) |
The catalog antibody’s IHC-P protocol is accompanied by one published ZC3H12C IHC method using paraffin sections (PMC10809481).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A13406); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-ZC3H12C, 5 μg/mL (datasheet A13406) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | ZC3H12C-positive staining in respiratory epithelial cells of bronchus (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression, most abundant in thyroid gland. No signal in the no-primary control. |
For paraffin-section IHC, expect ZC3H12C staining mainly in the cytoplasm, with high staining in bronchial and nasopharyngeal respiratory epithelial cells (HPA: tissue IHC). HPA describes the tissue pattern as ubiquitous and most abundant in thyroid gland, but rates its reliability Approved with low consistency against RNA expression data and pending external verification (HPA: tissue IHC). ZC3H12C has no annotated transmembrane segment (UniProt Q9C0D7 topology).
| Clear cytoplasmic staining in respiratory epithelial cells, with limited background in surrounding tissue (HPA: High in bronchus and nasopharynx). | This matches the strongest cell-specific examples supplied for tissue IHC (HPA: tissue IHC). Compare the positive cells with adjacent structures on the same slide; a dark deposit without identifiable cellular boundaries is less persuasive (general IHC interpretation). |
| Predominantly nuclear, membranous, or punctate staining replaces the expected cytoplasmic tissue pattern (HPA: tissue IHC). | Treat a compartment mismatch as possible artefact and check control sections and detection background (general IHC practice). Nuclear membrane and Golgi localisation comes from ICC-IF, so that result alone does not establish the expected paraffin-section pattern (HPA: subcellular ICC-IF). |
| Strong deposit appears in adipocytes, cardiomyocytes, or alveolar cells (HPA: Not detected in those cells). | Unexpected staining can reflect cross-reactivity or endogenous detection activity; assess whether it follows cellular contours or occurs across unrelated structures (general IHC practice). An HPA 'Not detected' call is a reference observation, not proof that every specimen must be negative (HPA: tissue IHC). |
| Pale, widespread chromogen obscures tissue structure and the expected positive cells (general IHC observation). | Diffuse background weakens the interpretation of any cytoplasmic signal (general IHC practice). Evaluate a no-primary control, blocking, antibody concentration, and chromogen development before assigning the deposit to ZC3H12C (general IHC practice). |
| No epithelial signal is visible in bronchus or nasopharynx (HPA: High in respiratory epithelial cells). | First consider an assay failure and inspect section quality, retrieval, antibody incubation, and detection controls (general IHC practice). HPA's Approved rating carries low RNA-staining consistency, so one negative section cannot independently settle target absence (HPA: tissue IHC reliability). |
| Tissue IHC reference and confidence | HPA reports ubiquitous cytoplasmic staining, greatest abundance in thyroid gland, and low tissue RNA specificity (HPA: tissue IHC). Its Approved label includes low antibody-staining versus RNA consistency and pending external verification; interpret unusual results with controls rather than treating the atlas pattern as definitive (HPA: reliability; general IHC practice). |
| Choice of comparison cells | Bronchial or nasopharyngeal respiratory epithelial cells provide High-staining comparisons; adipocytes, cardiomyocytes, and alveolar cells are listed as Not detected (HPA: tissue IHC). Compare the named cell populations, since 'lung alveolar cells' and 'bronchus respiratory epithelial cells' are different atlas observations (HPA: tissue IHC). |
| Antibody evidence | HPA038836 and HPA038837 each have Approved IHC status; the supplied records do not assign either an Enhanced IHC status (HPA: antibody records). Approval supports using the atlas images as a comparison, while the stated RNA-staining inconsistency still limits how confidently an unexpected deposit identifies ZC3H12C (HPA: tissue IHC reliability). |
| IF/ICC expectation? | HPA reports approved nuclear membrane and Golgi localisation in ICC-IF images from A-431, U-251MG, and U2OS (HPA: subcellular ICC-IF). Those cultured-cell observations answer the IF/ICC localisation question; use the cytoplasmic tissue profile to judge paraffin-section IHC (HPA: tissue IHC). |
| Protein features | UniProt lists two isoforms, one 1–883 chain, no signal peptide, no propeptide, and no transmembrane segment (UniProt Q9C0D7). These annotations do not identify the antibody epitope or establish isoform-specific staining, shedding, or a target-specific antigen-retrieval requirement (UniProt Q9C0D7; supplied antibody records). |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected respiratory epithelial cells are blank (HPA: High in bronchus and nasopharynx). | Weak or failed staining may arise at retrieval, antibody incubation, or detection steps (general IHC practice); target-specific fixation sensitivity is unreported in the supplied evidence. | Check a known-positive section in the same run, confirm the catalog antibody's IHC-P instructions, and verify chromogen and counterstain performance (general IHC practice). Interpret a single blank specimen cautiously given HPA's low RNA-staining consistency (HPA: reliability). |
| Signal is mainly nuclear or outlines cell surfaces in paraffin sections (HPA: cytoplasmic tissue IHC). | The compartment differs from the tissue reference; nonspecific deposit or misidentified cellular borders is possible (general IHC interpretation). ICC-IF nuclear membrane and Golgi localisation does not resolve an IHC discrepancy (HPA: subcellular ICC-IF). | Review morphology at higher magnification and compare matched controls and another HPA-positive cell population (general IHC practice; HPA: tissue IHC). Avoid calling the compartment ZC3H12C-specific from location alone. |
| Adipocytes, cardiomyocytes, or alveolar cells stain as strongly as expected positive epithelium (HPA: tissue IHC). | Those named populations are Not detected in the supplied HPA observations; cross-reactivity or endogenous detection activity is possible (HPA: tissue IHC; general IHC practice). | Run a no-primary control and assess blocking and detection chemistry (general IHC practice). Record the unexpected staining by cell type rather than labeling the entire tissue positive (general IHC scoring practice). |
| Chromogen is diffuse across cells and extracellular spaces (general IHC observation). | Excess primary antibody, insufficient blocking or washing, or prolonged chromogen development can raise background (general IHC practice). The pattern is difficult to reconcile with distinct cytoplasmic cell staining (HPA: tissue IHC). | Compare a no-primary control; then adjust blocking, washing, antibody concentration, or development time using the validated IHC-P workflow (general IHC practice). Score only cellular signal that remains distinguishable from background. |
| Thyroid staining differs from respiratory epithelium (HPA: thyroid most abundant; respiratory epithelium High). | HPA's thyroid statement is a tissue-level summary, while its supplied respiratory entries identify a particular cell type (HPA: tissue IHC). Differences in specimen and cell composition can complicate a direct intensity comparison (general IHC interpretation). | Describe the stained thyroid structures and compare like cell populations within each section (general IHC scoring practice). Do not infer a thyroid cell-specific expectation from the supplied HPA summary. |
| ICC-IF images show nuclear membrane or Golgi signal while the IHC section looks cytoplasmic (HPA: subcellular ICC-IF; tissue IHC). | The supplied HPA observations come from different assay formats and sample contexts; neither result alone proves that the other is erroneous (HPA: subcellular ICC-IF; tissue IHC). | Use the corresponding HPA assay reference for each interpretation and document the discrepancy (HPA: tissue IHC; subcellular ICC-IF). For IHC scoring, retain the named tissue and cell comparisons and assess staining specificity with controls (general IHC practice). |

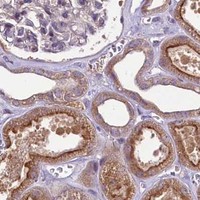

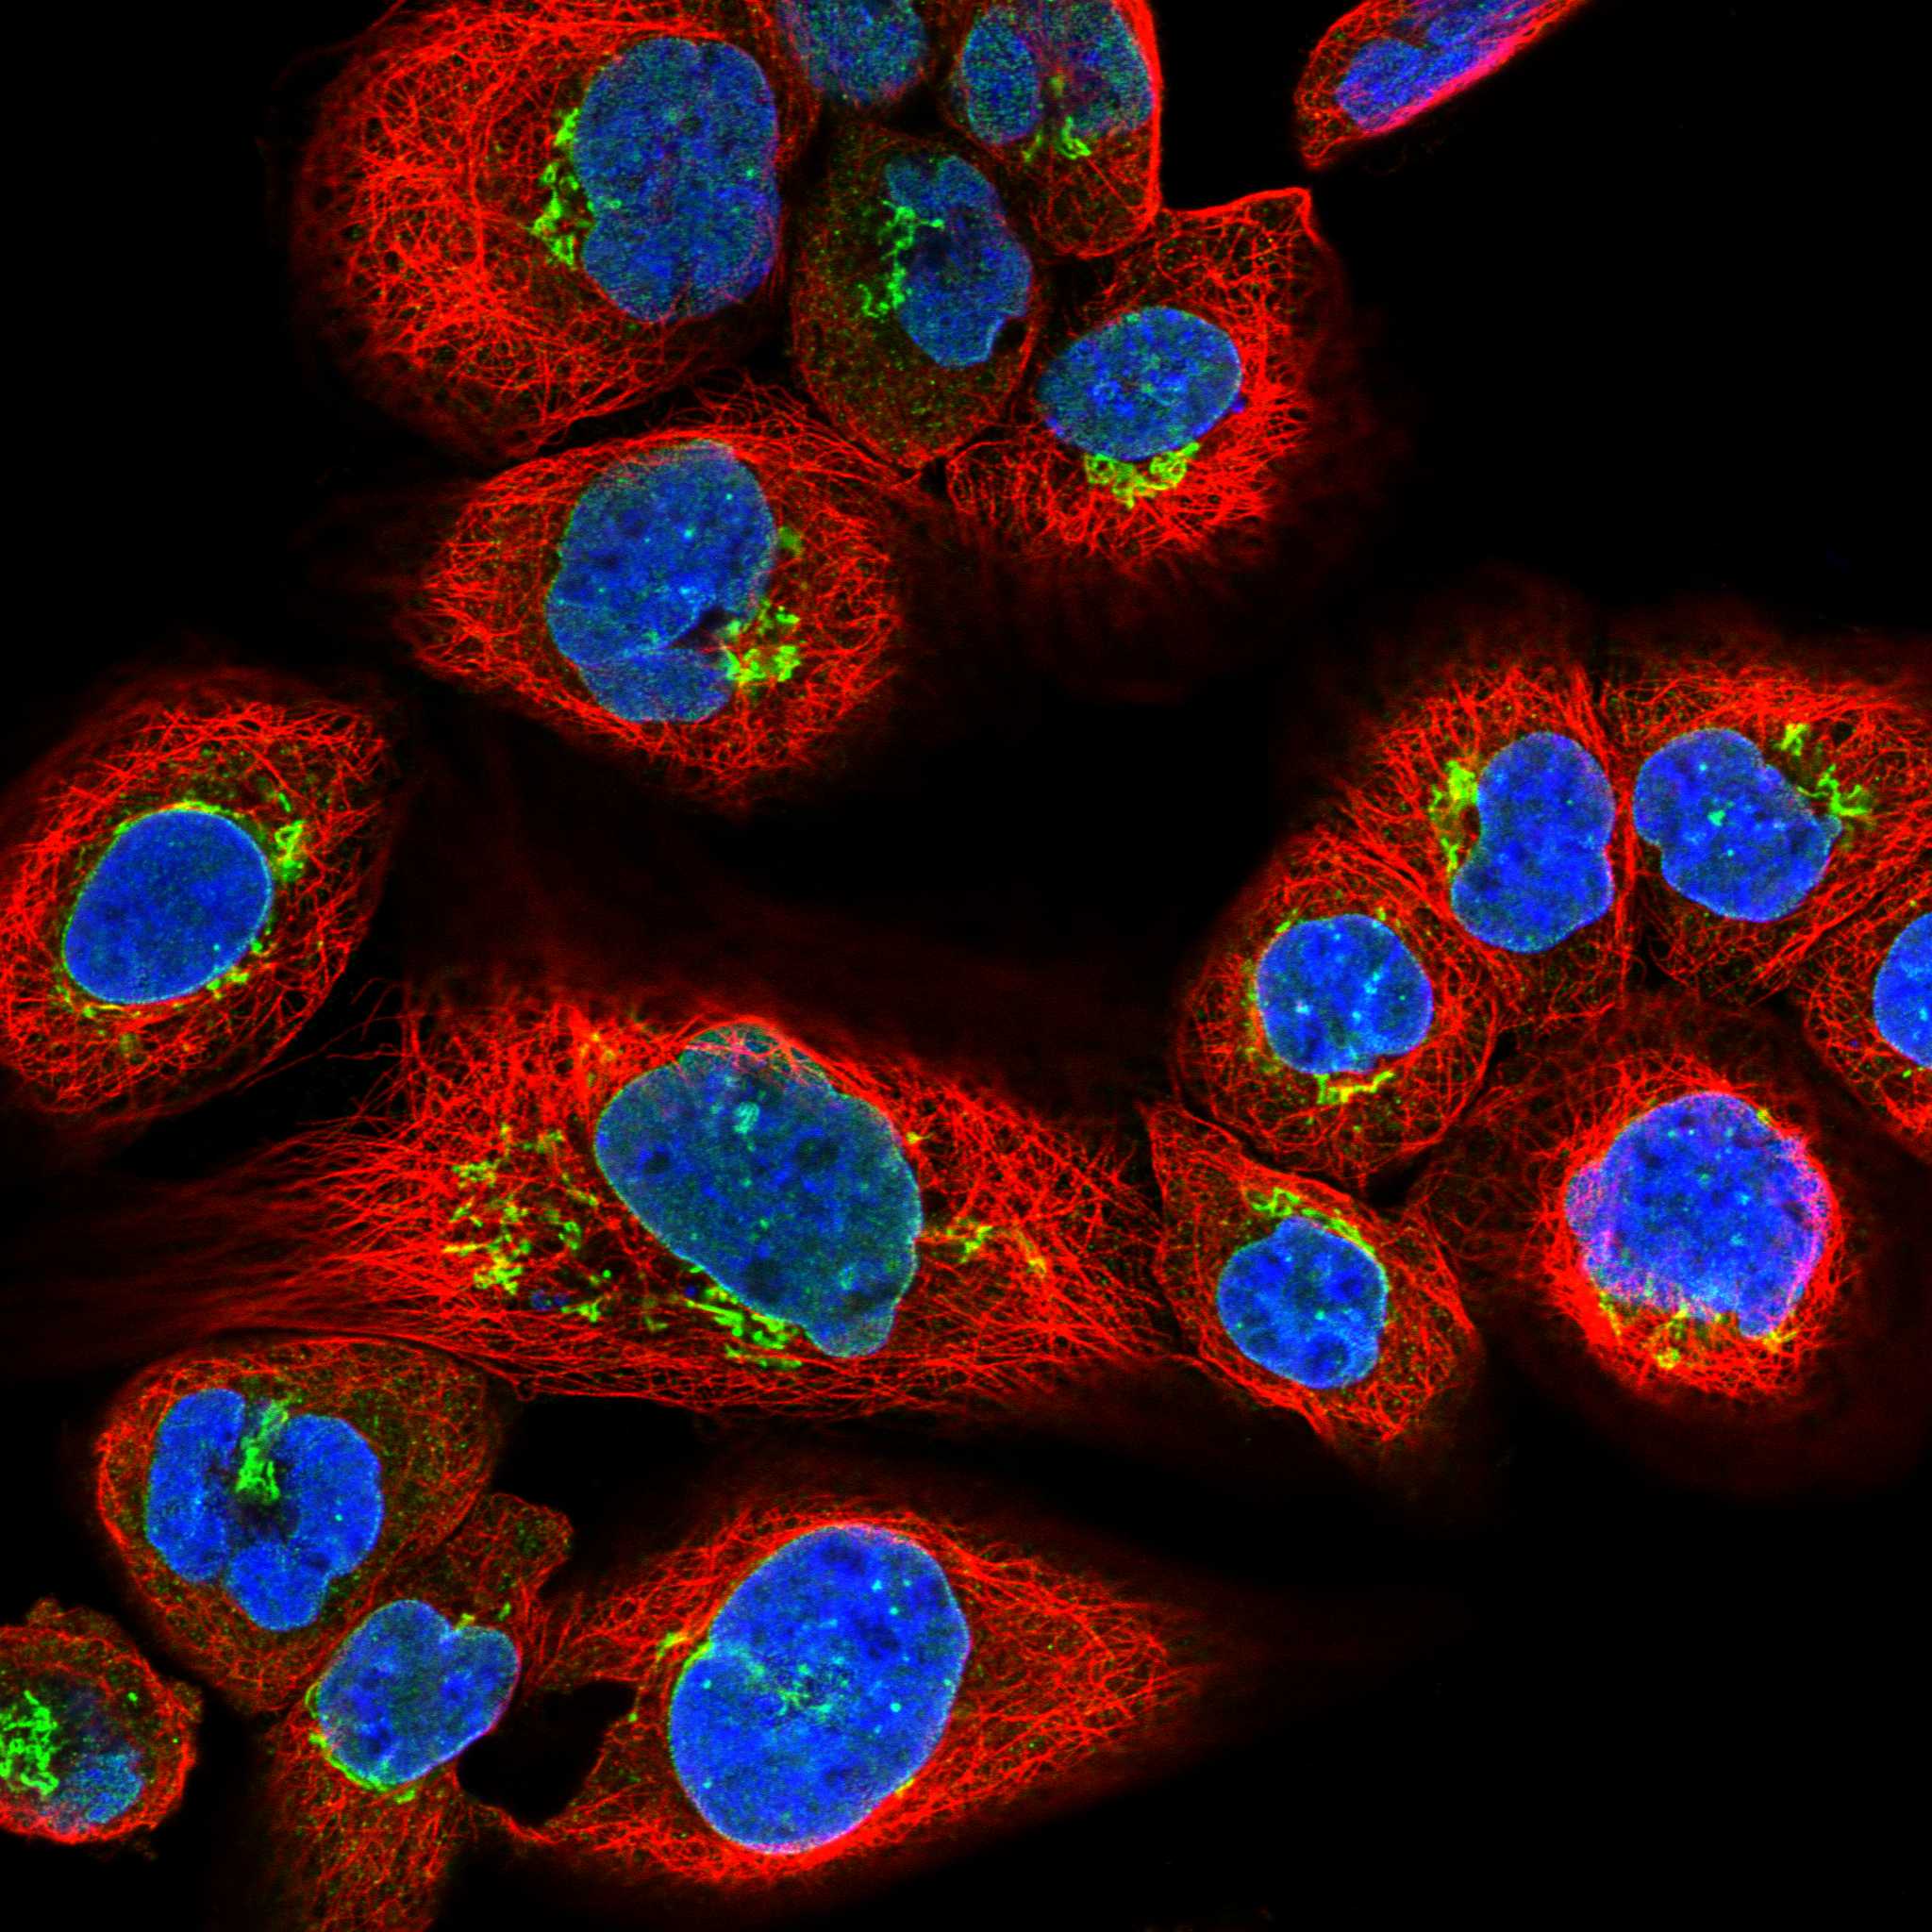
Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Nasopharynx | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Breast | Glandular cells | Medium | Protein (IHC) | HPA → |
| Caudate | Neuronal cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Heart muscle | Cardiomyocytes | Not detected | Protein (IHC) | HPA → |
| Lung | Alveolar cells | Not detected | Protein (IHC) | HPA → |
| Ovary | Ovarian stroma cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot ZC3H12C staining in paraffin sections by checking retrieval, compartment, cell identity and controls before comparing chromogenic signal across samples.
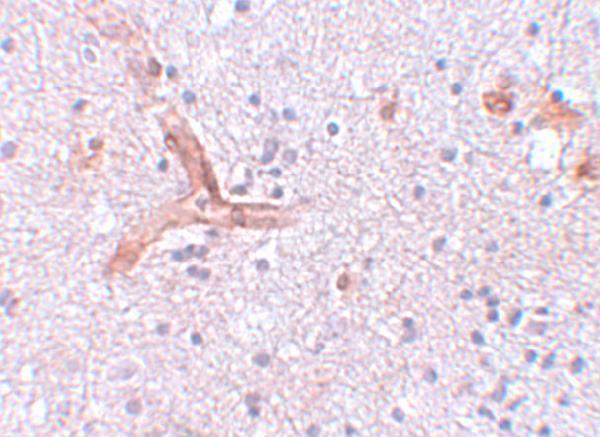
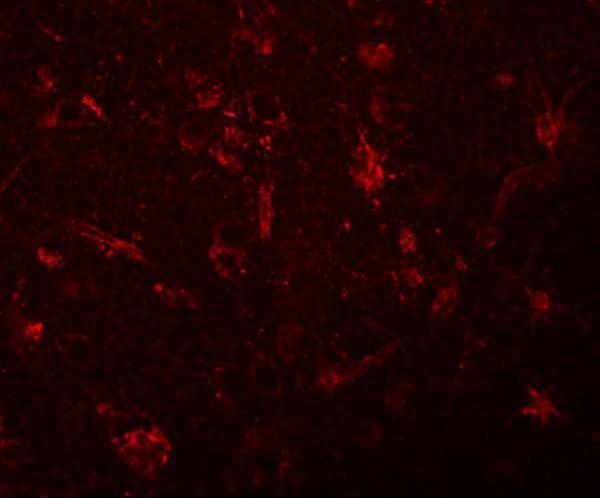
A13406 has real IHC and IF images from human brain tissue (catalog image captions); its listed reactivity covers human, mouse and rat (catalog: reactivity).
A13406 is listed for IHC-P and IF (catalog: applications), with IHC shown in human brain tissue at 5 μg/mL (catalog: IHC image caption). Its IF image shows human brain tissue at 20 μg/mL (catalog: IF image caption); mouse and rat are listed as reactive species (catalog: reactivity).
Which to pick: Choose A13406 for paraffin-section IHC (catalog: IHC-P application); its own IHC image shows human brain tissue at 5 μg/mL (catalog: IHC image caption), and the fixative is unreported (catalog: IHC image caption). For IF, A13406 has a human brain tissue image at 20 μg/mL (catalog: IF image caption); ICC validation is unreported (catalog: applications). For mouse or rat work, A13406 lists both species as reactive (catalog: reactivity), while the supplied IHC and IF images show human tissue (catalog: image captions).