ZFHX4 / Zinc finger homeobox protein 4 · IHC design guide

Design Immunohistochemistry for ZFHX4

Plan chromogenic IHC for ZFHX4 using its reported nuclear tissue staining (HPA tissue IHC). This guide covers fixation, antigen retrieval and scoring while accounting for the uncertain staining reliability (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
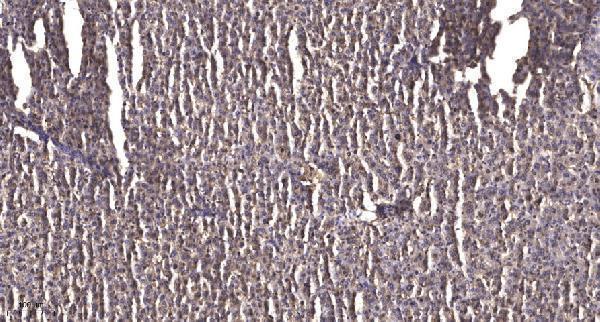
Immunohistochemistry protocol sheet for ZFHX4 (IHC for ZFHX4): expected localisation Nuclear tissue staining; reliability uncertain (HPA tissue IHC), antibody A09122, validated IHC image, and IHC protocol steps
Printable ZFHX4 IHC protocol sheet — expected localisation Nuclear tissue staining; reliability uncertain (HPA tissue IHC), antibody A09122, controls and protocol steps. Open the full ZFHX4 IHC guide →

ZFHX4 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear tissue staining; reliability uncertain (HPA tissue IHC)
Staining pattern Widespread nuclear staining across tissue cell types (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A09122)
Positive control ⓘ Adipose tissue+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Low staining–RNA concordance; verification pending (HPA tissue IHC)
Regulation Very low expression in stomach (UniProt)
Isoform / epitope Five isoforms; epitope coverage is unknown (UniProt)
Section 1

Recommended ZFHX4 IHC & IF Protocols

Start with the catalog antibody’s IHC-P protocol (datasheet A09122); the published lung adenocarcinoma protocol provides a citrate-retrieval comparison (PMC6811597).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human liver cancer tissue; fixative not specified (datasheet A09122)
FixationImage fixative and duration unreported (datasheet A09122); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Tris-EDTA pH 9.0 (datasheet A09122); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-ZFHX4, 1:200 (datasheet A09122)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultZFHX4-positive staining in adipocytes of adipose tissue (HPA tissue IHC: High). HPA tissue profile: Ubiquitous nuclear expression. No signal in the no-primary control.
💡Decision noteTry Tris-EDTA at pH 9.0 first (datasheet A09122); compare citrate at pH 6.0 if staining needs optimization (PMC6811597).
Section 2

What Is the Expected ZFHX4 Staining Pattern?

ZFHX4 is a nuclear protein with no transmembrane segment (UniProt Q86UP3: subcellular location and topology). In tissue IHC, expect nuclear staining across multiple cell types, including adipocytes, glandular cells, respiratory epithelial cells, hematopoietic cells and glial cells reported as High by HPA (HPA: tissue IHC). Treat this as a provisional pattern: HPA rates its tissue IHC reliability Uncertain because antibody staining has low consistency with RNA expression (HPA: reliability).

What am I looking at on my slide?
Distinct nuclear chromogen in adipocytes, glandular cells or glial cells.This fits the reported compartment and cell types (UniProt Q86UP3: Nucleus; HPA: High in adipocytes, glandular cells and caudate glial cells). A plausible pattern alone does not establish antibody specificity: the tissue IHC profile remains Uncertain (HPA: reliability).
Predominantly cytoplasmic or membrane staining while nuclei are clear.That distribution conflicts with the annotated nuclear location and lack of a transmembrane segment (UniProt Q86UP3: location and topology). Review staining controls and scoring before treating it as ZFHX4; the record does not support a cytoplasmic or membrane pattern.
Strong signal in a cell population outside the listed HPA examples.The examples are not an exclusive cell-type list: HPA describes ubiquitous nuclear expression and lists no negative tissues (HPA: tissue IHC). Unexpected staining may reflect cross-reactivity or endogenous detection activity (general IHC practice); assess its compartment and controls before assigning identity.
Diffuse chromogen covers tissue structures and obscures nuclear boundaries.This is difficult to score as the expected nuclear result (UniProt Q86UP3: Nucleus). General IHC practice: assess background with an appropriate negative detection control and review blocking, antibody concentration and washing before interpreting weak nuclei.
No nuclear signal in an HPA High example, such as adrenal glandular cells.The result differs from the reported tissue image pattern (HPA: High in adrenal glandular cells), but one negative section cannot establish absent ZFHX4. HPA rates tissue IHC Uncertain (HPA: reliability); check run controls and detection before drawing a biological conclusion.
💡Expected ZFHX4 appearanceCall a result provisionally positive when chromogen is concentrated in nuclei of a reported High cell population, such as adipocytes or glandular cells (UniProt Q86UP3: Nucleus; HPA: High in those cells); predominantly cytoplasmic, membrane or diffuse background staining does not match that pattern, and HPA tissue IHC remains Uncertain (HPA: reliability).
How each factor affects the staining
Tissue IHC confidenceHPA describes ubiquitous nuclear expression but rates its tissue IHC profile Uncertain because staining and RNA expression have low consistency (HPA: tissue IHC reliability). Treat a matching slide as supportive rather than independently validated evidence of specificity.
Choice of comparison tissueHPA reports High staining in adipocytes, adrenal and appendix glandular cells, respiratory epithelial cells, hematopoietic cells and selected brain cells (HPA: tissue IHC). It supplies no negative or low tissue examples, so these data do not define a validated negative tissue control.
Nuclear compartmentUniProt assigns ZFHX4 to the nucleus and reports no transmembrane segment or signal peptide (UniProt Q86UP3: location, topology and processing). A prominent membrane or cytoplasmic result therefore needs independent scrutiny; these annotations alone cannot identify the source of such signal.
Subnuclear detailHPA approves nucleoplasm and nucleoli fibrillar center localization in ICC-IF (HPA: subcellular ICC-IF). That cell-image evidence can inform compartment interpretation, but it does not establish that both structures must resolve in chromogenic paraffin-section IHC.
Isoforms and target coverageUniProt lists five ZFHX4 isoforms and one annotated chain spanning residues 1–3567 (UniProt Q86UP3: isoforms and processing). The supplied record gives no antibody epitope, so it cannot establish which isoforms a particular IHC result detects.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No staining in an HPA High tissue example.Possible run or detection failure, or a genuine discrepancy; HPA tissue IHC is Uncertain (HPA: reliability).General IHC practice: verify the run control, reagent coverage, retrieval and detection steps, then repeat with a suitable positive control. Compare the same cell population and nuclear compartment before interpreting absence.
Brown signal is mainly cytoplasmic or membranous.This conflicts with the annotated nuclear location and absence of a transmembrane segment (UniProt Q86UP3: location and topology); its cause is undetermined.General IHC practice: inspect morphology and a negative detection control, check for nonspecific staining, and score nuclear and extranuclear signal separately. Do not count extranuclear chromogen alone as the expected positive pattern.
Diffuse background makes weak nuclei hard to distinguish.Nonspecific binding or endogenous detection activity can create background (general IHC practice); the supplied sources do not identify a ZFHX4-specific cause.General IHC practice: check the negative detection control, blocking, washing and antibody concentration. Reassess only after nuclear boundaries are readable; HPA's reported pattern is nuclear (HPA: tissue IHC).
An unexpected cell population stains strongly.It could reflect broader expression or an assay artifact: HPA calls the tissue pattern ubiquitous but Uncertain (HPA: profile and reliability).Compare nuclear localization with nearby cells and use appropriate controls (general IHC practice). Avoid calling the population negative solely because it is absent from HPA's High examples; no negative tissues are listed (HPA: tissue IHC).
A reported High population stains, but only weakly.HPA's High designation is an observed tissue staining level, not a required intensity for every section or assay (HPA: tissue IHC).General IHC practice: compare sections processed in the same run and check controls and counterstain before scoring. Record nuclear intensity and the fraction of stained cells separately; retain HPA's Uncertain reliability caveat (HPA: reliability).
IF/ICC Q: Which fluorescent compartment should be assessed?A: HPA approves nucleoplasm and nucleoli fibrillar center localization in ICC-IF (HPA: subcellular ICC-IF).Assess fluorescence against those nuclear compartments and appropriate controls (general IF practice). Treat this as localization guidance only; HPA's ICC-IF result does not resolve the Uncertain tissue IHC assessment (HPA: tissue IHC reliability).

Sample controls for ZFHX4 IHC & IF

🧪Run adipose tissue first and score adipocyte nuclei, which are reported as High for ZFHX4 (HPA: adipose tissue, adipocytes High; UniProt Q86UP3: nucleus). HPA detects ZFHX4 in all 45 scored tissues, so there is no supported negative tissue; use no-primary and isotype controls, and expect lipid spaces and anucleate erythrocytes on the positive slide to lack nuclear staining (HPA: no negative tissue; standard IHC practice).
Positive control tissue: Adipose tissue (Adipocytes, HPA High)
Negative control tissue: None in HPA: ZFHX4 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show ZFHX4 in A-549, U-251MG, U2OS, NIH 3T3, with annotated localisation: Nucleoplasm (approved), Nucleoli fibrillar center (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only slide and a concentration-matched isotype antibody of the same host species and clonality; validate specificity with ZFHX4 knockout material or a matching immunizing-peptide block if available (standard IHC practice). For chromogenic detection, block endogenous peroxidase and check that any signal in adipose tissue is nuclear rather than pigment or background (standard IHC practice; UniProt Q86UP3: nucleus).
⚠️Feasibility: A target-specific fixation window and fixation effect are unreported, and the selected paraffin-section caption does not state a fixative (selected SKU A09122 caption). That caption uses Tris-EDTA retrieval at pH 9.0 and primary antibody at 1:200 overnight at 4°C; it provides a starting condition but does not establish that retrieval is required (selected SKU A09122 caption). The supplied evidence does not establish whether frozen sections or IF are easier; adipocyte nuclei are thin and peripheral, so distinguish nuclear signal from the large unstained lipid space when scoring (HPA: adipose tissue, adipocytes High; standard histology practice).

HPA tissue IHC evidence for ZFHX4

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes High Protein (IHC) HPA →
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Adipocytes High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: ZFHX4 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced ZFHX4 IHC Tips

Troubleshoot ZFHX4 staining by checking retrieval, nuclear localisation, controls and scoring against the available paraffin-section evidence (caption A09122; UniProt Q86UP3).

Which retrieval condition should I start with for ZFHX4 paraffin-section IHC?
Use heat-mediated Tris-EDTA, pH 9.0, for antigen retrieval before chromogenic IHC (datasheet A09122). The selected paraffin-section image used this buffer, primary antibody at 1:200 overnight at 4 °C, and secondary antibody at 1:200 for 45 min at room temperature (caption A09122). Hold section thickness, heating duration, cooling and detection constant while adjusting retrieval intensity; excessive heating can damage morphology or increase background (standard IHC practice). If nuclear staining remains weak, compare a milder retrieval condition as a fallback on matched sections, with a no-primary control (standard IHC practice).
Does fixation explain weak ZFHX4 staining in paraffin sections?
The selected image shows paraffin-embedded human liver cancer, but its fixative is unreported (caption A09122). ZFHX4-specific sensitivity to fixation is therefore unknown; the tissue staining profile and nuclear annotation do not establish a preferred fixative (HPA tissue IHC; UniProt Q86UP3). Record the fixation reagent and duration, then compare matched sections processed identically while holding retrieval at Tris-EDTA, pH 9.0 (datasheet A09122; standard IHC practice). Assess nuclear signal, morphology and background together, since fixation can alter epitope accessibility in general (standard IHC practice). Assign a ZFHX4-specific fixation effect only if replicated comparisons support it (standard IHC practice).
Where should convincing ZFHX4 chromogenic staining appear?
Prioritise staining within nuclei: ZFHX4 is annotated as nuclear, and the HPA tissue profile describes ubiquitous nuclear expression (UniProt Q86UP3; HPA tissue IHC). HPA subcellular images further place it in the nucleoplasm and nucleoli fibrillar center, although those observations do not validate the catalog antibody in paraffin sections (HPA subcellular; caption A09122). Compare signal with a nuclear counterstain and inspect individual cells at high magnification before calling a section positive (standard IHC practice). Diffuse cytoplasmic staining or a rim limited to section edges warrants a background check rather than a ZFHX4 localisation call (UniProt Q86UP3; standard IHC practice).
Could isoform or epitope differences explain inconsistent nuclear staining?
ZFHX4 has 5 annotated isoforms, so epitope coverage matters when comparing antibodies or specimens (UniProt Q86UP3). The supplied evidence gives no catalog-antibody epitope coordinates or isoform coverage; a negative stain cannot identify which isoform is absent (datasheet A09122; UniProt Q86UP3). Request the immunogen sequence or mapped epitope and compare it with the isoforms before interpreting discordant staining (standard IHC practice; UniProt Q86UP3). The protein has no annotated transmembrane segment, and its listed modifications include N-terminal acetylation and phosphoserine at residue 2663; neither establishes epitope masking in these sections (UniProt Q86UP3).
How should I assess ZFHX4 in a multiplex IF experiment?
Use IF as a separate validation experiment: the selected antibody evidence describes paraffin-section chromogenic IHC, while HPA reports ZFHX4 in the nucleoplasm and nucleoli fibrillar center (caption A09122; HPA subcellular). Pair ZFHX4 with a validated glial-cell marker when examining caudate, where HPA reports high staining in glial cells (HPA tissue IHC; standard IF practice). Choose a spectrally separated far-red fluorophore and inspect an unstained section to assess tissue autofluorescence (standard IF practice). Because ZFHX4 is nuclear and lacks a transmembrane segment, optimise permeabilisation for access through the plasma and nuclear boundaries, then verify localisation with a nuclear counterstain (UniProt Q86UP3; standard IF practice).
How can I distinguish background from ZFHX4 DAB staining?
Inspect a no-primary control processed through the same secondary antibody and DAB steps to identify detection-system background (standard IHC practice). Include a peroxidase block before chromogenic detection and compare it with an appropriately controlled run, since endogenous enzyme activity can produce DAB signal (standard IHC practice). Titrate the primary antibody around the image condition of 1:200 while keeping retrieval at Tris-EDTA, pH 9.0, and detection time fixed (caption A09122; standard IHC practice). Judge improvement by nuclear contrast and preserved morphology, rather than total brown area, because the expected ZFHX4 compartment is nuclear (UniProt Q86UP3; standard IHC practice).
How should I quantify ZFHX4 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Score only interpretable nuclei within a predefined tissue region, using the counterstain to define the cell denominator (UniProt Q86UP3; standard IHC practice). Report the percentage of positive nuclei and staining intensity, or calculate an H-score from 0–300 using intensity categories from 0–3 (standard IHC practice). For cell-rich regions, positive nuclei per mm² can supplement the percentage, provided the analysed area is recorded (standard IHC practice). Keep retrieval, antibody dilution, DAB development, imaging and thresholds consistent across sections; exclude folds and necrotic regions by a prespecified rule (datasheet A09122; standard IHC practice).
What makes a ZFHX4-positive IHC result credible?
A credible result has cell-resolved nuclear staining with suitable control performance, consistent with ZFHX4's nuclear annotation (UniProt Q86UP3; standard IHC practice). Compare the stained cells with the tissue context: HPA reports high staining in caudate glial cells, but rates its tissue IHC reliability uncertain because staining and RNA expression have low consistency (HPA tissue IHC). Check suspicious cytoplasmic signal, section-edge enhancement and necrotic areas against morphology and a no-primary control (UniProt Q86UP3; standard IHC practice). Exclude endogenous peroxidase signal before interpreting brown deposits as ZFHX4, and describe the observed cells and compartment rather than treating stain intensity alone as confirmation (standard IHC practice).
Boster reagents

Best ZFHX4 / Zinc finger homeobox protein 4 IHC Antibodies

A09122 has an IHC image from paraffin-embedded human liver cancer (IHC image caption). Human and mouse reactivity and IF use are listed, but no IF image is supplied (catalog applications/reactivity; IF image alts).

Real IHC data Immunohistochemical analysis of paraffin-embedded human liver cancer. 1, Antibody was diluted at 1:200 (4° overnight). 2, Tris-EDTA, pH9.0 was used for antigen retrieval. 3, Secondary antibody was diluted at 1:200 (room temperature, 45min).
Anti-Zinc finger homeobox protein 4 ZFHX4 Antibody
Cat # A09122

A09122 will render with its paraffin-embedded human liver cancer IHC figure, using 1:200 primary antibody and Tris-EDTA retrieval at pH 9.0 (IHC image caption). IF is listed for A09122, with human and mouse reactivity, but the payload supplies no IF image or mouse-sample figure (catalog applications/reactivity; image alts).

Which to pick: Choose A09122 for paraffin-section IHC because its own figure documents that preparation; the fixative is unreported (IHC image caption). For IF, A09122 is listed at 1:50, but IF/ICC image validation is not supplied (catalog applications/dilution; IF image alts). For human or mouse samples, A09122 lists both species as reactive; the supplied tissue figure demonstrates human tissue only, and clonality is unreported (catalog reactivity/clone; IHC image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q86UP3 (ZFHX4_HUMAN, Zinc finger homeobox protein 4).
  2. Human Protein Atlas. ZFHX4 tissue IHC expression (reliability: Uncertain).
  3. Human Protein Atlas. ZFHX4 subcellular location (ICC-IF): Localized to the nucleoplasm and nucleoli fibrillar center..
  4. Human Protein Atlas. ZFHX4 antibody validation summary (1 antibodies).
  5. The TWIST1-centered competing endogenous RNA network promotes proliferation, invasion, and migration of lung adenocarcinoma. Oncogenesis 2019 — PMC6811597.
  6. The histone demethylase Kdm6b regulates subtype diversification of mouse spinal motor neurons during development. Nature communications 2022 — PMC8854633.
  7. Zfhx4 regulates endochondral ossification as the transcriptional platform of Osterix in mice. Communications biology 2021 — PMC8566502.
  8. Expression analysis of genes including Zfhx4 in mice and zebrafish reveals a temporospatial conserved molecular basis underlying craniofacial development. Developmental dynamics : an official publication of the American Association of Anatomists 2025 — PMC11877995.
  9. PubMed PMID:16946494 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:16421571 — UniProt-cited evidence.