ZNF263 / Zinc finger protein 263 · IHC design guide

Design Immunohistochemistry for ZNF263

Plan ZNF263 paraffin-section IHC around the observed cytoplasmic tissue pattern (HPA tissue IHC) and annotated nuclear location (UniProt). The human-reactive IHC-validated antibody A11578 has a listed dilution of 1:50–1:200 (datasheet); compare cell compartments and staining intensity across consistently fixed specimens.

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ZNF263 (IHC for ZNF263): expected localisation Cytoplasmic tissue staining (HPA tissue IHC); nuclear location (UniProt), antibody A11578, validated IHC image, and IHC protocol steps
Printable ZNF263 IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC); nuclear location (UniProt), antibody A11578, controls and protocol steps. Open the full ZNF263 IHC guide →

ZNF263 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC); nuclear location (UniProt)
Staining pattern Generally cytoplasmic across multiple cell types (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen)
Positive control ⓘ Breast+4 more · see all
Negative control ⓘ Adipose tissue+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A11578)
Caveat Nuclear location (UniProt) contrasts with cytoplasmic staining (HPA tissue IHC)
Regulation No specific expression regulator listed (UniProt)
Isoform / epitope No listed isoforms; single 1–683 chain (UniProt)
Section 1

Recommended ZNF263 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol with published ZNF263 protocols for colorectal and mouse gastric paraffin sections (PMC11410824; PMC6851613).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded Human colon tissue; fixative not specified (datasheet A11578)
FixationImage fixative and duration unreported (datasheet A11578); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-ZNF263, 1:50-1:200 (datasheet A11578)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultZNF263-positive staining in glandular cells of breast (HPA tissue IHC: Medium). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with Tris-EDTA pH 9.0 HIER at 95–98 °C for 20 min (page antigen retrieval); the published protocols provide citrate retrieval alternatives (PMC11410824; PMC6851613).
Section 2

What Is the Expected ZNF263 Staining Pattern?

For paraffin-section IHC, expect predominantly cytoplasmic ZNF263 staining in selected cell populations, including breast glandular cells, bronchial respiratory epithelial cells and caudate neurons (HPA tissue IHC: Medium; general cytoplasmic expression). Interpret this alongside UniProt’s nuclear localisation and HPA’s ICC-IF nucleoplasmic signal; a nuclear component is plausible (UniProt O14978: nucleus; HPA ICC-IF: nucleoplasm). HPA rates the tissue IHC profile Approved, with medium consistency between staining and RNA expression (HPA tissue IHC: reliability).

What am I looking at on my slide?
Clear cytoplasmic colour in breast glandular cells, bronchial respiratory epithelial cells or caudate neurons.This matches HPA’s reported Medium staining in those cells and its general cytoplasmic IHC profile (HPA tissue IHC). Compare signal with a matched negative control and assess the named cells, rather than judging the whole section as uniformly positive (general IHC practice).
Signal appears confined to cell borders or extracellular material, without a convincing intracellular pattern.A membrane or extracellular pattern is inconsistent with the reported cytoplasmic IHC profile and with a protein lacking a transmembrane segment or signal peptide (HPA tissue IHC; UniProt O14978: topology, processing). Check morphology and detection controls before assigning this colour to ZNF263 (general IHC practice). Nuclear staining alone needs separate review because UniProt reports nuclear localisation and HPA ICC-IF reports nucleoplasmic signal (UniProt O14978; HPA ICC-IF).
Prominent colour occurs in adipocytes, soft-tissue fibroblasts or splenic red-pulp cells.These cell populations were Not detected in the supplied HPA tissue IHC examples (HPA tissue IHC). Consider cross-reactivity or endogenous detection activity, especially if the control shows the same colour (general IHC practice). The examples do not establish that every specimen of these tissues must be negative (HPA tissue IHC: observed examples).
A diffuse wash of colour obscures both cells and spaces between them.The distribution is difficult to score as cellular ZNF263 staining (general IHC practice). Examine the negative control, washing and detection background before interpreting intensity (general IHC practice). HPA’s reported pattern describes cellular cytoplasmic staining, so diffuse colour by itself does not confirm the target (HPA tissue IHC).
No signal appears in a section containing an HPA-reported Medium-staining cell population.An absent signal does not establish absent ZNF263: HPA reports Medium staining in specified cells, while its IHC reliability is Approved with medium staining–RNA consistency (HPA tissue IHC). First check that the expected cells are present, then review controls and the validated staining conditions (general IHC practice).
💡Expected ZNF263 appearanceA credible positive is distinct, predominantly cytoplasmic chromogenic staining of the relevant cells at approximately Medium intensity in HPA’s positive examples; isolated membrane or extracellular colour, or matching colour in the negative control, is suspect (HPA tissue IHC; UniProt O14978: topology; general IHC practice).
How each factor affects the staining
IHC localisation versus annotated localisationHPA describes general cytoplasmic staining in tissue IHC, whereas UniProt annotates the nucleus (HPA tissue IHC; UniProt O14978: subcellular location). Record cytoplasmic and nuclear staining separately when scoring; these sources do not justify requiring exclusively nuclear IHC staining.
Cell population and tissue choiceHPA reports Medium staining in several distinct cell populations, Low staining in listed glandular, alveolar and urothelial cells, and Not detected staining in its adipocyte, fibroblast and splenic red-pulp examples (HPA tissue IHC). Select the actual cell population for comparison; HPA also reports low tissue specificity at the RNA level (HPA tissue IHC).
Protein topology and processingUniProt reports no transmembrane segment, signal peptide or propeptide, and lists one chain spanning residues 1–683 (UniProt O14978: topology, processing). These annotations support scrutiny of a membrane-only pattern; they do not establish any target-specific effect of formalin fixation or antigen retrieval.
Antibody validation scopeHPA lists HPA035085 and HPA035086 as Approved for IHC, while the tissue profile has medium consistency with RNA expression (HPA antibodies; HPA tissue IHC: reliability). Approved status supports using the reported pattern as a reference, but it does not resolve every discordant compartment or specimen.
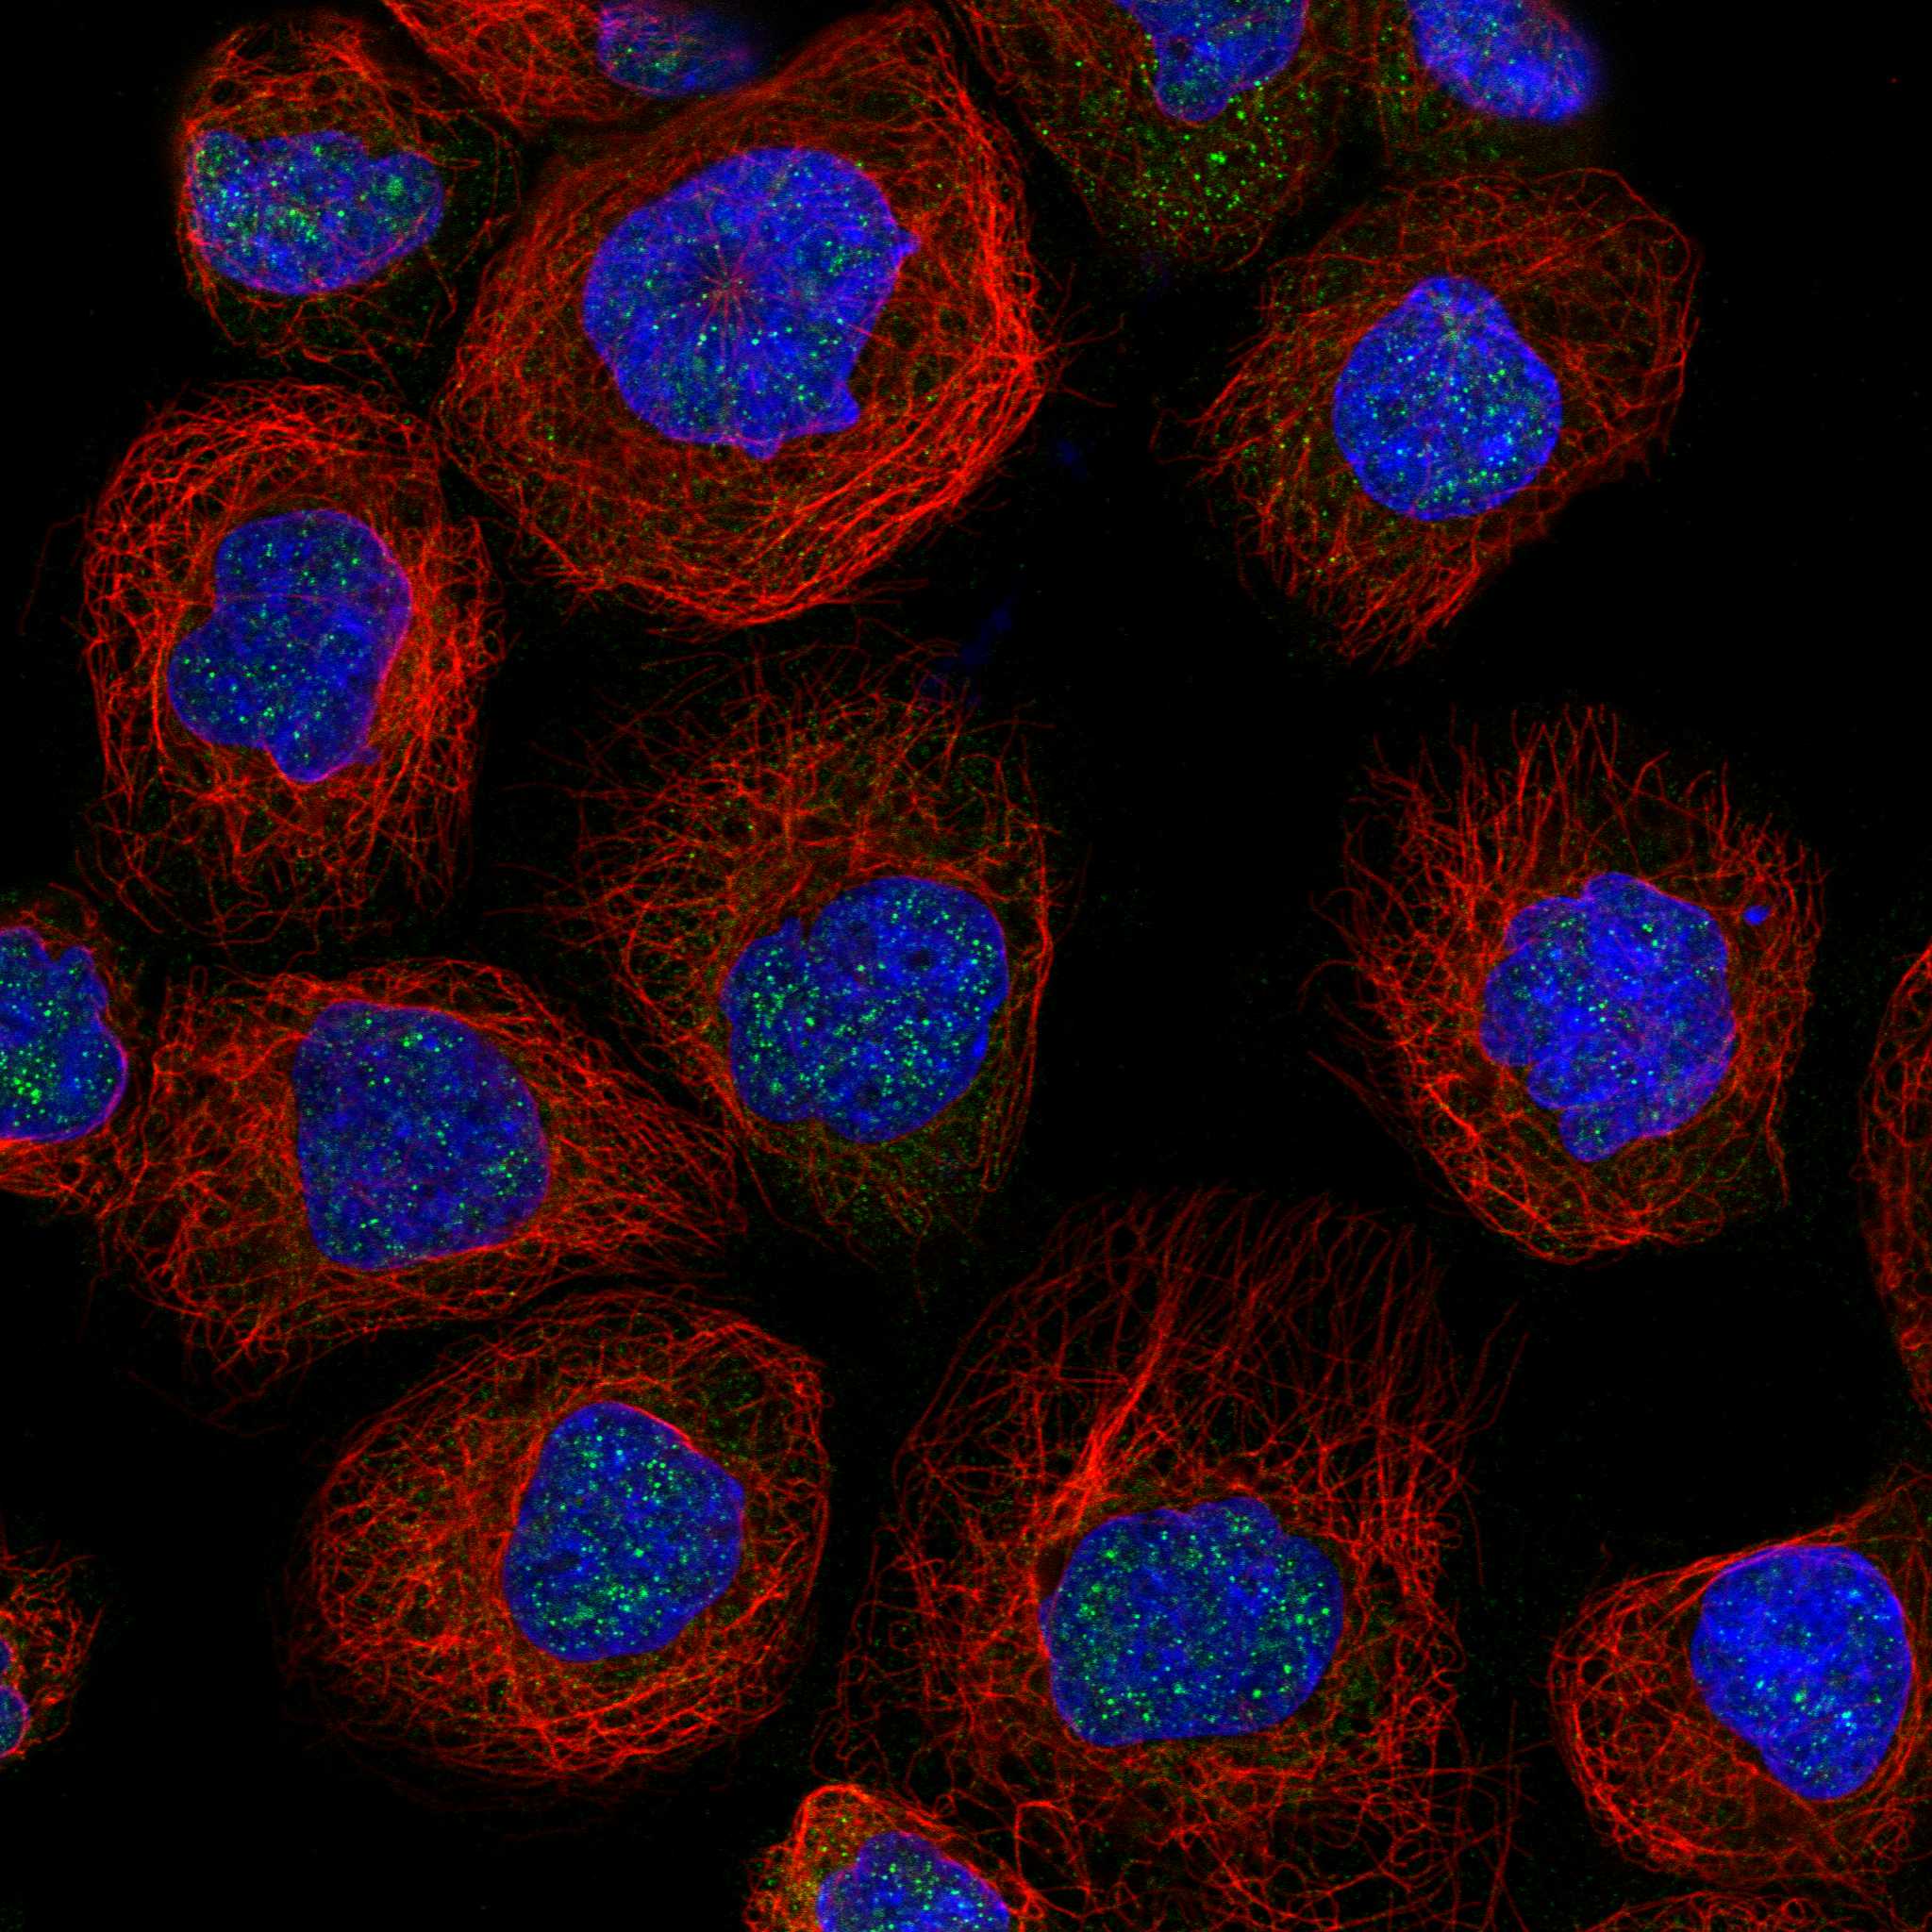
IF/ICC Q&A: should IF show only cytoplasmic signal?No. HPA ICC-IF reports cytosol as the supported main location, with nucleoplasm and mitotic spindle as approved additional locations; images are listed for A-431, U-251MG and U2OS (HPA ICC-IF). This describes IF interpretation only; the IF/ICC guide covers its staining workflow.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A reported positive cell population is unstained.The expected cells may be absent from the examined field, or the IHC run may have failed (HPA tissue IHC: cell-specific examples; general IHC practice).Confirm cell identity on the counterstained section, then inspect the run’s positive control and the catalog antibody’s IHC-P instructions before changing conditions (general IHC practice).
Every cell looks strongly positive, including HPA Not detected examples.Widespread signal conflicts with the supplied cell-specific observations; background or endogenous detection activity is possible (HPA tissue IHC; general IHC practice).Compare a negative control, review blocking and detection steps, and reassess colour within identified cell types (general IHC practice).
Colour is diffuse across tissue and empty spaces.Detection background or inadequate washing can obscure cellular staining (general IHC practice).Inspect the negative control and repeat with careful washing and the detection system’s recommended blocking steps (general IHC practice).
Only nuclei stain in IHC.UniProt annotates nuclear localisation, and HPA ICC-IF includes nucleoplasm, but HPA’s tissue IHC profile is generally cytoplasmic (UniProt O14978; HPA ICC-IF; HPA tissue IHC).Record nuclear and cytoplasmic compartments separately; check controls and morphology before accepting a nuclear-only result as the expected IHC pattern (general IHC practice).
Signal outlines cell borders or coats extracellular material.That pattern conflicts with HPA’s cytoplasmic IHC profile and UniProt’s lack of a transmembrane segment and signal peptide (HPA tissue IHC; UniProt O14978: topology, processing).Review the negative control, tissue morphology and detection background before scoring the outlined material as target staining (general IHC practice).
Low-staining tissue is difficult to score.HPA reports Low staining in several listed populations, including lung alveolar and urinary-bladder urothelial cells (HPA tissue IHC).Compare the same cell type across test and control sections, and use an HPA Medium-staining example to assess whether the run produced detectable signal (HPA tissue IHC; general IHC practice).

Sample controls for ZNF263 IHC & IF

🧪Run breast first and assess staining in glandular cells (HPA: Medium in breast glandular cells). Use adipose tissue as the negative tissue (HPA: Not detected in adipocytes); adipocytes within the breast section, if present, can serve as internal negative cells and should lack specific staining (HPA: Not detected in adipocytes).
Positive control tissue: Breast (Glandular cells, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show ZNF263 in A-431, U-251MG, U2OS, with annotated localisation: Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a matched rabbit polyclonal IgG isotype control (catalog caption: rabbit pAb). A ZNF263 knockout sample, if available, provides a biological negative; block endogenous peroxidase before chromogenic detection and assess background in the breast section (standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A11578 colon paraffin-section caption does not state a fixative (catalog caption: fixative unreported). That caption documents microwave retrieval in 10 mM PBS, pH 7.2 for colon, but does not establish a retrieval requirement for breast (catalog caption: colon IHC); supplied evidence does not show that frozen sections or IF are easier, although ICC-IF images exist for A-431, U-251MG and U2OS (HPA: ICC-IF images). In breast paraffin sections, adipocyte lipid spaces can appear empty, so assess an adipocyte negative control by its intact cell morphology rather than the empty space alone (standard IHC practice).

HPA tissue IHC evidence for ZNF263

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Breast Glandular cells Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →
Caudate Neuronal cells Medium Protein (IHC) HPA →
Cerebellum Purkinje cells Medium Protein (IHC) HPA →
Cerebral cortex Endothelial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Soft tissue Fibroblasts Not detected Protein (IHC) HPA →
Spleen Cells in red pulp Not detected Protein (IHC) HPA →
Section 3

Advanced ZNF263 IHC Tips

Troubleshoot ZNF263 staining in paraffin sections by checking retrieval, compartment, controls, and scoring alongside the antibody’s documented tissue IHC evidence.

What should I change if ZNF263 staining is weak after antigen retrieval?
Use Tris-EDTA pH 9.0 HIER at 95–98 °C for 20 min as this page’s starting retrieval condition (page retrieval setting). If staining remains weak, compare it on adjacent sections with microwave retrieval in 10 mM PBS at pH 7.2, the condition documented for catalog antibody A11578 in paraffin-embedded human colon (A11578 tissue-IHC caption). Keep antibody concentration and detection identical across the comparison so retrieval is the variable being tested (standard IHC practice). Include a no-primary control, and assess signal separately in nuclei and cytoplasm because published localisation evidence differs between sources (UniProt O14978; HPA subcellular).
Could fixation be masking ZNF263 in my paraffin sections?
Target-specific sensitivity to fixation is unknown: the A11578 colon caption identifies paraffin-embedded tissue but does not state its fixative (A11578 tissue-IHC caption). Record the fixative, time in fixative, tissue thickness, and processing history for each block before comparing staining (standard IHC practice). For newly prepared formalin-fixed specimens, use a consistent neutral buffered formalin workflow and compare matched blocks if fixation duration is suspected (standard IHC practice). Evaluate those blocks with the same retrieval, antibody dilution, and detection run; differences then support a processing effect without assigning ZNF263 a fixation sensitivity that has not been demonstrated (standard IHC practice).
Should convincing ZNF263 staining be nuclear or cytoplasmic?
Score nuclear and cytoplasmic chromogenic signal separately, since UniProt lists ZNF263 in the nucleus while HPA tissue IHC describes general cytoplasmic expression (UniProt O14978; HPA tissue IHC). HPA cell imaging mainly places it in the cytosol, with additional nucleoplasmic and mitotic-spindle localisation, so cytoplasmic staining alone is not automatically an artefact (HPA subcellular). Examine individual cells against a nuclear counterstain and document whether staining follows cell boundaries or appears diffuse across damaged tissue (standard IHC practice). Require a reproducible cell-specific pattern and appropriate controls before interpreting either compartment as ZNF263, especially where the two reference sources disagree (UniProt O14978; HPA subcellular; standard IHC practice).
How can I investigate an unexpected staining pattern without a mapped epitope?
The supplied record lists 0 isoforms and a single 1–683 chain, so it provides no basis for assigning different IHC patterns to splice variants (UniProt O14978). ZNF263 contains a SCAN box at residues 41–123 and a KRAB domain at 217–289, but the A11578 caption does not identify the antibody epitope (UniProt O14978; A11578 tissue-IHC caption). Phosphoserines at positions 166 and 178 are recorded; their effects on this antibody’s binding are unknown (UniProt O14978; A11578 tissue-IHC caption). Compare retrieval conditions on adjacent sections and seek epitope documentation before attributing changed staining to a domain or modification (standard IHC practice).
How should I follow up the IHC pattern with multiplex IF?
Use IF as an independent follow-up to the chromogenic IHC result, pairing ZNF263 with a validated marker for the cell population identified in the section (standard IF practice). HPA reports medium staining in colon endothelial cells and breast glandular cells, which are possible populations to examine when those tissues are used (HPA tissue IHC). Select fluorophores after checking tissue autofluorescence and reserve the clearest channel for the weaker signal (standard IF practice). ZNF263 has no transmembrane segment and is reported in cytosol and nucleoplasm, so permeabilise fixed cells sufficiently to assess intracellular compartments and inspect marker overlap in each compartment (UniProt O14978; HPA subcellular; standard IF practice).
How do I reduce diffuse brown staining without losing ZNF263 signal?
First compare the stained section with a no-primary control to identify signal from detection reagents or endogenous enzyme activity (standard chromogenic IHC practice). Quench endogenous peroxidase before peroxidase-based detection, block nonspecific binding, and shorten DAB development if background rises across the section (standard chromogenic IHC practice). For catalog antibody A11578, 1:100 is the dilution documented in its paraffin-embedded human colon caption; test nearby concentrations against that reference rather than assuming it suits every section (A11578 tissue-IHC caption; standard IHC practice). Check section edges, folds, and damaged areas separately, because staining concentrated there does not establish cell-specific ZNF263 expression (standard IHC practice).
What is a defensible way to quantify ZNF263 staining across samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define the tissue compartment and eligible cell population before scoring, then report nuclear and cytoplasmic staining separately because the reference localisation profiles differ (UniProt O14978; HPA tissue IHC; standard IHC practice). For cell-based scoring, record the percentage of positive eligible cells and an H-score from intensity categories; normalise each to the number of evaluable cells, not the whole section (standard IHC practice). If the question concerns a spatially defined population, report positive-cell density per mm² of viable, annotated tissue (standard IHC practice). Keep retrieval, imaging, counterstain, thresholds, and excluded damaged regions consistent across samples, and retain control-section results with the scores (standard IHC practice).
When does an apparent positive ZNF263 result need further validation?
Treat a reproducible cellular pattern as more persuasive when it occurs in a defined population and remains absent from the no-primary control (standard IHC practice). HPA reports medium staining in colon endothelial cells and no detection in adipocytes or splenic red-pulp cells; these are observations for their tested material, not universal controls for every antibody (HPA tissue IHC). Nuclear staining accords with UniProt, while cytoplasmic staining accords with HPA, so compartment alone cannot settle specificity (UniProt O14978; HPA tissue IHC; HPA subcellular). Recheck signals confined to section edges, necrotic areas, or endogenous-peroxidase-rich regions with matched controls before calling them ZNF263-positive (standard chromogenic IHC practice).
Boster reagents

Best ZNF263 / Zinc finger protein 263 IHC Antibodies

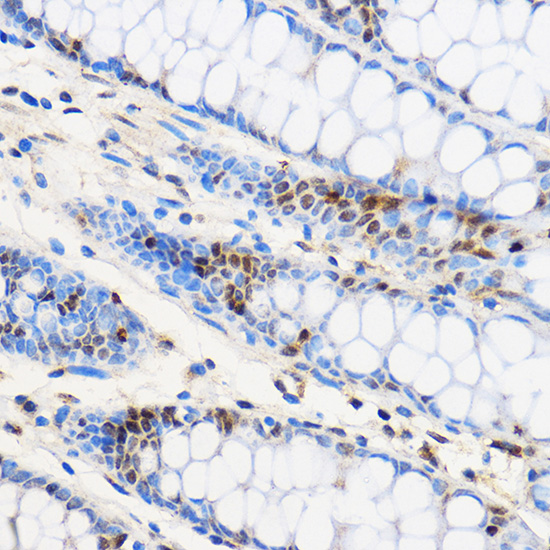
A11578 has real IHC data from paraffin-embedded human colon (image caption); the catalog lists human reactivity (catalog: Human). No IF figure is provided (catalog: IF images absent).

Real IHC data Immunohistochemistry of paraffin-embedded Human colon using ZNF263 Rabbit pAb at dilution of 1:100 .Perform microwave antigen retrieval with 10 mM PBS buffer pH 7.2 before commencing with IHC staining protocol.
Anti-Zinc finger protein 263 ZNF263 Antibody
Cat # A11578

A11578 is listed for human IHC (catalog: applications and reactivity). Its IHC figure shows paraffin-embedded human colon stained at 1:100 after microwave retrieval in 10 mM PBS, pH 7.2 (image caption).

Which to pick: Choose A11578 for paraffin-section tissue IHC; it is a rabbit polyclonal antibody with human reactivity and an IHC application listing (catalog: host, clonality, reactivity, applications). Its colon image supports paraffin sections, but the fixative is unreported (image caption). No listed SKU has an IF/ICC application or non-human reactivity, so the payload does not support an IF/ICC or cross-species pick (catalog: applications and reactivity).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O14978 (ZN263_HUMAN, Zinc finger protein 263).
  2. Human Protein Atlas. ZNF263 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. ZNF263 subcellular location (ICC-IF): Mainly localized to the cytosol. In addition localized to the nucleoplasm and mitotic spindle..
  4. Human Protein Atlas. ZNF263 antibody validation summary (2 antibodies).
  5. A zinc finger family protein, ZNF263, promotes hepatocellular carcinoma resistance to apoptosis via activation of ER stress-dependent autophagy. Translational oncology 2020 — PMC7486481.
  6. Zinc finger protein 263 promotes colorectal cancer cell progression by activating STAT3 and enhancing chemoradiotherapy resistance. Scientific reports 2024 — PMC11410824.
  7. The EGFR-ZNF263 signaling axis silences SIX3 in glioblastoma epigenetically. Oncogene 2020 — PMC7142014.
  8. mRNA and lncRNA Expression Profiling of Radiation-Induced Gastric Injury Reveals Potential Radiation-Responsive Transcription Factors. Dose-response : a publication of International Hormesis Society 2019 — PMC6851613.
  9. PubMed PMID:9256059 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:15616553 — UniProt-cited evidence.