This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic ZNF668 IHC in paraffin sections using the catalog antibody’s 1:100–1:300 dilution range (datasheet A13922-1). Assess nuclear staining against the reported all-tissue profile, whose reliability is uncertain (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclear tissue staining reported; reliability uncertain (HPA tissue IHC) | |
| Staining pattern | Nuclear staining across all tissues (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A13922-1) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific) | |
| Caveat | Staining awaits external verification (HPA tissue IHC) | |
| Regulation | No expression regulator annotated (UniProt) | |
| Isoform / epitope | 2 isoforms; epitope coverage unreported (UniProt) |
The catalog antibody’s IHC-P protocol (datasheet: A13922-1) is accompanied by a published ZNF668 protocol for a multi-tumor tissue microarray (PMC12732025).
| Sample | Paraffin-embedded human brain tumor tissue; fixative not specified (datasheet A13922-1) |
| Fixation | Image fixative and duration unreported (datasheet A13922-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Tris-EDTA pH 9.0 (datasheet A13922-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-ZNF668, 1:100-1:300 (datasheet A13922-1) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | ZNF668-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Nuclear expression in all tissues. No signal in the no-primary control. |
ZNF668 is a nuclear protein with no annotated transmembrane segment (UniProt Q96K58: subcellular location and topology). In paraffin-section IHC, expect nuclear staining across tissues, including glandular cells in colon and respiratory epithelial cells in bronchus (HPA: tissue IHC). Treat intensity as provisional: HPA rates the tissue profile Uncertain because antibody staining and RNA expression show medium consistency, pending external verification (HPA: tissue IHC reliability).
| Clear nuclear chromogen in colon glandular cells or bronchial respiratory epithelial cells. | This matches reported High staining in those cells (HPA: colon and bronchus tissue IHC) and the nuclear location (UniProt Q96K58). Record the cell type and nuclear fraction stained; HPA's tissue assessment remains Uncertain (HPA: reliability). |
| Strong cytoplasmic or membrane staining with little nuclear signal. | The compartment conflicts with the nuclear annotation and lack of a transmembrane segment (UniProt Q96K58). Treat it as a suspected artefact; assess background, detection controls and whether nuclear staining is present before interpreting it as ZNF668. |
| The strongest signal appears in a cell population reported as Low, while an expected High population is faint. | For example, prominent hepatocyte staining alongside faint colon glandular staining conflicts with HPA's relative levels (HPA: liver Low; colon High). Consider cross-reactivity or endogenous detection activity (standard IHC practice), while allowing for HPA's Uncertain reliability. |
| Chromogen spreads across nuclei, cytoplasm and spaces between cells. | A diffuse deposit cannot establish nuclear localisation (UniProt Q96K58: nucleus). Check blocking, wash and detection controls for nonspecific background (standard IHC practice); score discrete cellular signal only after the background is resolved. |
| No nuclear signal in a section containing colon glandular cells. | Colon glandular cells are reported High (HPA: colon tissue IHC), so an absent signal calls for a control and workflow check. It does not by itself prove ZNF668 is absent, especially given the Uncertain tissue assessment (HPA: reliability). |
| Tissue and cell selection | Colon glandular cells, bronchial respiratory epithelial cells and bone marrow hematopoietic cells are reported High; hepatocytes and adipocytes are Low (HPA: tissue IHC). Use these as relative comparisons, not as absolute positive or negative standards (HPA: reliability Uncertain). |
| Compartment resolution | Nuclear staining is the tissue-level expectation (HPA: nuclear expression in all tissues; UniProt Q96K58: nucleus). A chromogenic IHC section need not resolve the nucleolar detail reported by ICC-IF (HPA: subcellular ICC-IF); evaluate the nucleus first. |
| Antibody evidence | The listed antibody HPA043048 has Uncertain IHC status and Approved ICC status (HPA: antibody validation). The tissue profile also awaits external verification (HPA: reliability). Agreement with the expected pattern supports interpretation but does not independently establish specificity. |
| Isoforms and processing | UniProt lists two isoforms and annotates one chain spanning residues 1–619, with no signal peptide or propeptide (UniProt Q96K58). The payload gives no epitope position or isoform coverage, so staining cannot identify which isoform contributed. |
| IF/ICC Q&A: What subnuclear pattern is expected? | HPA reports mainly nucleoli and nucleoli rim, with additional nucleoplasm, in ICC-IF images from A-431, U-251MG and U2OS (HPA: subcellular ICC-IF). That approved ICC observation guides image interpretation; it does not prescribe an IHC protocol or guarantee visible nucleoli in chromogenic sections. |
| Situation | Likely cause | Next action |
|---|---|---|
| No staining in colon glandular cells. | A missed or weak detection step is possible (standard IHC practice); colon glandular cells are reported High (HPA: colon tissue IHC). | Check the catalog antibody's IHC-P conditions, detection reagents and a concurrently processed positive section (standard IHC practice). Interpret a persistent absence cautiously because tissue IHC reliability is Uncertain (HPA: reliability). |
| Only cytoplasmic signal is visible. | The location conflicts with ZNF668's nuclear annotation (UniProt Q96K58); nonspecific or endogenous detection signal is possible (standard IHC practice). | Compare a detection-only control and inspect nuclear counterstain alignment (standard IHC practice). Do not score cytoplasmic colour alone as a positive ZNF668 result. |
| Colour covers the whole section. | Diffuse background can obscure the expected nuclear pattern (UniProt Q96K58: nucleus; standard IHC practice). | Review blocking, washes and detection-only controls, then reassess whether discrete nuclei remain above background (standard IHC practice). Avoid assigning a cell type from a uniform deposit. |
| Hepatocytes stain more strongly than colon glandular cells. | This reverses the supplied relative profile (HPA: hepatocytes Low; colon glandular cells High), although HPA rates the tissue IHC profile Uncertain. | Review cell identification and section controls; investigate cross-reactivity or endogenous detection activity (standard IHC practice). Report the discrepancy rather than treating HPA levels as an absolute exclusion rule. |
| Nuclei stain, but nucleoli cannot be distinguished. | Nucleoli and nucleoli rim are ICC-IF findings (HPA: subcellular ICC-IF); chromogenic tissue IHC may not resolve that detail (standard IHC practice). | Judge the IHC result by nuclear localisation and the identified cell population (UniProt Q96K58: nucleus; HPA: tissue IHC). Use the separate IF/ICC guide for subnuclear imaging. |
| A section shows patchy or unexpectedly weak nuclear staining. | The supplied sources do not establish a ZNF668-specific fixation sensitivity; variable detection is a general IHC possibility (standard IHC practice). | Compare sections processed together and review the catalog antibody's IHC-P conditions (standard IHC practice). Document the variation without assigning it to ZNF668 epitope masking. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Cervix | Glandular cells | High | Protein (IHC) | HPA → |
| Colon | Glandular cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: ZNF668 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Troubleshoot ZNF668 staining by checking nuclear localization, documented retrieval conditions, and controls before interpreting chromogenic signal.
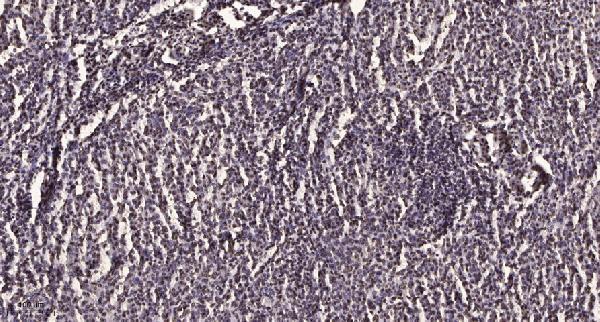
A13922-1 is listed for human and mouse IHC and IF (catalog: applications and reactivity); its supplied image documents IHC on paraffin-embedded human brain tumor (IHC image caption).
A13922-1 will render with its IHC figure from paraffin-embedded human brain tumor (IHC image caption). It is listed for human and mouse IHC and IF, but no IF image is supplied (catalog: applications, reactivity and image captions).
Which to pick: Choose A13922-1 for paraffin-section IHC: its own figure used a 1:200 primary dilution and Tris-EDTA retrieval at pH 9.0 (IHC image caption); the fixative is unreported (IHC image caption). For IF, A13922-1 is listed with a 1:200–1:1000 dilution range, while ICC validation and an IF image are unreported (catalog: applications, dilution and image captions). The same SKU is listed as mouse reactive, but its supplied IHC figure shows human tissue only (catalog: reactivity; IHC image caption).