ADO / 2-aminoethanethiol dioxygenase · IHC design guide

Design Immunohistochemistry for ADO

Plan chromogenic ADO IHC with the catalog antibody, using neuronal cells and lung macrophages as candidate positive controls (HPA tissue IHC). Assess cytoplasmic and extracellular staining with matched controls, and interpret intensity cautiously because staining and RNA expression have low agreement (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ADO (IHC for ADO): expected localisation Cytoplasmic and extracellular tissue staining (HPA tissue IHC), antibody PB10032, validated IHC image, and IHC protocol steps
Printable ADO IHC protocol sheet — expected localisation Cytoplasmic and extracellular tissue staining (HPA tissue IHC), antibody PB10032, controls and protocol steps. Open the full ADO IHC guide →

ADO Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and extracellular tissue staining (HPA tissue IHC)
Staining pattern Cytoplasmic/extracellular positivity across several tissues (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet PB10032)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Appendix+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep tissue fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Staining has low agreement with RNA expression (HPA tissue IHC)
Regulation Low tissue specificity at RNA level (HPA tissue RNA)
Isoform / epitope No annotated isoforms or cleavage; epitope location unknown (UniProt)
Section 1

Recommended ADO IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet: PB10032) with one published ADO tissue-microarray protocol (PMC11704412).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded rat brain tissue; fixative not specified (datasheet PB10032)
FixationImage fixative and duration unreported (datasheet PB10032); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet PB10032); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet PB10032)
Primary antibodyRabbit anti-ADO, 2-5μg/ml (datasheet PB10032)
Primary incubationOvernight at 4 °C (datasheet PB10032)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet PB10032)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultADO-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Extracellular positivity and cytoplasmic expression in several tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA, pH 8.0, for the catalog antibody (datasheet: PB10032); citrate, pH 6.0, is the published alternative (PMC11704412).
Section 2

What Is the Expected ADO Staining Pattern?

ADO staining is expected mainly in the cytoplasm of selected cells, with extracellular positivity also reported (HPA: tissue IHC profile). Medium staining is reported in lung macrophages, brain neurons, cardiomyocytes, and selected glandular and hematopoietic cells (HPA: tissue IHC). ADO has no annotated transmembrane segment (UniProt Q96SZ5). Treat this pattern as provisional: HPA rates the tissue staining Approved but reports low consistency with RNA expression and pending external verification (HPA: reliability).

What am I looking at on my slide?
Cytoplasmic staining in lung macrophages or cortical neurons, with some extracellular staining.This fits the reported compartment and cell patterns; both cell types have Medium staining (HPA: tissue IHC). Assess cellular staining separately from extracellular color so the latter does not inflate the count of positive cells (general IHC practice).
Strong nuclear-only or sharply membrane-dominant staining across many cells.This diverges from the reported cytoplasmic and extracellular profile (HPA: tissue IHC). ADO has no annotated transmembrane segment, but topology alone cannot prove such staining is an artefact (UniProt Q96SZ5 topology). Review controls and antibody specificity before assigning it to ADO (general IHC practice).
Prominent staining in colon glandular cells or bronchial basal cells.Both are reported as Not detected (HPA: tissue IHC). Consider cross-reactivity or endogenous chromogenic activity, especially if the negative reagent control also develops color (general IHC practice). An unexpected positive result needs confirmation because the HPA tissue profile has low RNA concordance (HPA: reliability).
Uniform pale color over cells, stroma, and slide background.A broad haze obscures the reported cell and compartment pattern (HPA: tissue IHC profile). Background may arise from nonspecific binding, incomplete blocking, or detection chemistry (general IHC practice); it cannot establish widespread ADO expression.
No staining in lung macrophages or heart cardiomyocytes.These are Medium-staining examples, so an absent signal merits a run-level check (HPA: tissue IHC). Examine the positive control, primary-antibody conditions, retrieval, and detection reagents (general IHC practice). A failed run cannot be interpreted as tissue-specific absence.
💡Expected ADO appearanceCall a result compatible when selected cells show discernible cytoplasmic color, potentially alongside extracellular positivity (HPA: tissue IHC profile); expect Medium staining in lung macrophages or cortical neurons (HPA: tissue IHC), while diffuse haze or nuclear-only color warrants control-based review (general IHC practice).
How each factor affects the staining
Tissue and cell selectionLung macrophages, cortical neurons, heart cardiomyocytes, and bone-marrow hematopoietic cells are Medium examples (HPA: tissue IHC). Colon glandular and bronchial basal cells are Not detected examples (HPA: tissue IHC). Compare the named cell population, not the whole section (general IHC practice).
Interpretive confidenceThe tissue profile is Approved but has low antibody-staining/RNA consistency and awaits external verification (HPA: reliability). Concordance with the reported pattern is useful, yet it is not independent proof of target specificity.
Antibody evidenceHPA039194 and HPA040437 each have Approved IHC status (HPA: antibodies). Neither is listed as ICC-IF validated in the supplied antibody record (HPA: antibodies). Their status does not establish that every positive structure is ADO.
Topology and processingADO has no annotated transmembrane segment, signal peptide, propeptide, or glycosylation site; its annotated chain spans residues 1–270 (UniProt Q96SZ5). These annotations give no basis for a membrane-only pattern or a processing-dependent staining prediction.
Fixation and retrievalTarget-specific fixation sensitivity and antigen-retrieval conditions are unreported in the supplied UniProt and HPA records. Use a controlled retrieval comparison if the stain is weak (general IHC practice); do not infer an ADO-specific fixation effect.
IF/ICC: what pattern should be expected?HPA provides no assigned ICC-IF location or cell-line images (HPA: subcellular record). Cytoplasmic IHC staining is a provisional comparison only (HPA: tissue IHC); it does not establish an IF/ICC localization or protocol.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Positive-control tissue is blank.The run may have inadequate primary-antibody binding, retrieval, or chromogenic detection (general IHC practice); Medium staining is reported in lung macrophages and heart cardiomyocytes (HPA: tissue IHC).Check section integrity and reagent controls, then compare retrieval and primary-antibody conditions one variable at a time (general IHC practice). Do not score other blank sections as ADO-negative until the control works.
A section shows mostly nuclear color.Nuclear-only staining conflicts with the reported cytoplasmic and extracellular profile (HPA: tissue IHC). Counterstain or nonspecific signal may complicate interpretation (general IHC practice).Inspect an unstained or negative reagent control, check counterstain intensity, and compare the expected positive cell population before scoring nuclear signal as ADO (general IHC practice).
Extracellular color overwhelms cell boundaries.Some extracellular positivity is reported (HPA: tissue IHC profile), but excessive chromogen development or background can obscure cytoplasmic staining (general IHC practice).Shorten chromogen development or adjust detection conditions with matched controls (general IHC practice). Record extracellular and cytoplasmic observations separately; do not count extracellular deposits as positive cells.
Colon glands or bronchial basal cells stain strongly.These cell populations are reported as Not detected (HPA: tissue IHC). Cross-reactivity or endogenous detection activity is possible (general IHC practice).Compare a negative reagent control and a reported Medium-staining population in the same run (HPA: tissue IHC; general IHC practice). Seek independent confirmation if the unexpected cell pattern persists, given HPA's low RNA concordance (HPA: reliability).
Color appears throughout the section, including acellular areas.This does not resolve the selected cellular pattern reported by HPA (HPA: tissue IHC). Nonspecific binding, incomplete blocking, or excessive detection may contribute (general IHC practice).Review blocking, washes, reagent controls, and chromogen time using the same slide set (general IHC practice). Reassess only distinct cellular staining after background is reduced.
An IF/ICC image disagrees with the IHC pattern.HPA supplies no ICC-IF images or assigned subcellular location (HPA: subcellular record); the tissue IHC pattern cannot validate an IF/ICC result.Assess IF/ICC with its own controls and guide (general IF practice). Keep the IHC call tied to the reported tissue and cell pattern (HPA: tissue IHC).

Sample controls for ADO IHC & IF

🧪Run cerebral cortex first and score its neuronal cells for ADO staining (HPA: cerebral cortex neuronal cells, Medium). Use appendix glandular cells as the negative tissue (HPA: appendix glandular cells, Not detected); on the cortex slide, use morphologically identifiable non-neuronal cells as internal background comparators, while confirming their staining status rather than assuming they lack ADO.
Positive control tissue: Adrenal gland (Glandular cells, HPA Medium)
Negative control tissue: Appendix (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for ADO; derive a cell-line control from the positive tissue's cell type (Glandular cells) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary (secondary-only) slide, a matched rabbit IgG isotype control, and ADO knockout tissue if available (caption: rabbit anti-ADO primary). For chromogenic detection, block endogenous peroxidase and check endogenous biotin background in brain tissue when using the biotin-based detection shown in the caption (caption: biotinylated secondary and SABC–DAB detection).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected PB10032 paraffin-section caption does not state the fixative (caption: fixative unreported). Heat retrieval in EDTA at pH 8.0 is a documented starting condition, but a retrieval dependency is unreported (caption: rat-brain paraffin section, heat retrieval in EDTA pH 8.0). The supplied evidence does not establish that frozen sections or IF are easier; brain lipofuscin autofluorescence may complicate IF interpretation (standard IF practice).

HPA tissue IHC evidence for ADO

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →
Caudate Neuronal cells Medium Protein (IHC) HPA →
Cerebral cortex Neuronal cells Medium Protein (IHC) HPA →
Gallbladder Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bronchus Basal cells Not detected Protein (IHC) HPA →
Cervix Glandular cells Not detected Protein (IHC) HPA →
Colon Glandular cells Not detected Protein (IHC) HPA →
Duodenum Glandular cells Not detected Protein (IHC) HPA →
Section 3

Advanced ADO IHC Tips

Troubleshoot ADO staining in paraffin sections using the catalog antibody’s tissue IHC conditions, then assess localisation and controls against the available tissue evidence.

What retrieval should I try when ADO staining is weak in paraffin sections?
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet PB10032). The catalog antibody stained a paraffin section of rat brain under that condition, followed by 2 µg/mL primary antibody overnight at 4°C (datasheet PB10032). If signal remains weak, compare a modest change in heating time on adjacent sections while keeping detection and exposure to DAB constant (standard IHC practice). Include a no-primary control and inspect tissue integrity, because damaged sections can make stronger retrieval look falsely beneficial (standard IHC practice). Record the retrieval conditions for every slide before comparing staining intensity (standard IHC practice).
Could fixation explain inconsistent ADO staining between specimens?
Target-specific sensitivity of ADO staining to fixation is unknown: the selected paraffin-section caption does not state a fixative (datasheet PB10032). Do not infer fixation tolerance from the reported tissue staining or the absence of a transmembrane segment and annotated glycosylation sites (HPA tissue IHC; UniProt Q96SZ5 topology and processing). For a controlled comparison, process matched specimens with documented fixation and section preparation, then apply the same EDTA pH 8.0 retrieval (standard IHC practice; datasheet PB10032). Keep primary incubation at 2 µg/mL overnight at 4°C while assessing that variable (datasheet PB10032). Score signal alongside morphology and background rather than intensity alone (standard IHC practice).
How should I assess extracellular or cytoplasmic ADO staining?
Assess cytoplasmic and extracellular staining separately, because both appear in the tissue profile (HPA tissue IHC). UniProt supplies no subcellular location for ADO and reports no transmembrane segment, signal peptide or propeptide (UniProt Q96SZ5 subcellular, topology and processing). That record does not establish an exclusively intracellular pattern or prove that extracellular chromogen represents ADO (UniProt Q96SZ5; standard IHC interpretation). Compare staining within intact cells against adjacent extracellular areas and a no-primary control on the same tissue (standard IHC practice). Document the compartment and cell type for each scored area instead of pooling all brown signal (standard IHC practice).
Can an unreported isoform or modified epitope explain discordant staining?
No ADO isoforms are annotated, and the record describes a single 1–270 chain without annotated glycosylation or modified residues (UniProt Q96SZ5 isoforms and processing). Those annotations do not identify the catalog antibody’s epitope or establish how fixation and retrieval affect its accessibility (UniProt Q96SZ5; datasheet PB10032). Check the antibody documentation for its immunogen before interpreting a missing signal as loss of a particular region (standard IHC practice). Compare adjacent sections using the documented EDTA pH 8.0 retrieval and identical primary conditions (datasheet PB10032). If staining differs from another antibody, evaluate each reagent’s validation and controls independently (standard IHC practice).
How can I assess ADO by IF alongside a cell-type marker?
For a separate IF experiment, pair ADO with a validated marker of the cell type under study; neuronal cells and lung macrophages show medium tissue staining (HPA tissue IHC). Choose spectrally separated fluorophores and check an unstained section in each channel before selecting the ADO channel, especially where tissue autofluorescence is strong (standard IF practice). The ADO epitope’s position is unspecified, although no transmembrane segment is annotated, so compare staining with and without gentle permeabilisation rather than assuming antibody access (UniProt Q96SZ5 topology; standard IF practice). Include single-label and no-primary controls to identify bleed-through and background (standard IF practice). Do not transfer the paraffin-section antibody conditions to IF without validation (datasheet PB10032; standard IF practice).
What should I check when brown staining obscures ADO-positive cells?
First compare a no-primary section with the test section to separate detection-system staining from primary-dependent signal (standard IHC practice). For chromogenic IHC, block endogenous peroxidase before DAB development and assess whether the block reduces diffuse brown staining (standard IHC practice). The catalog example used 10% goat serum, biotinylated secondary antibody, streptavidin-biotin detection and DAB (datasheet PB10032). Include an appropriate detection-only control if background persists with that system, and keep development time consistent across slides (standard IHC practice). Exclude folds, damaged edges and necrotic regions from scoring because they can accumulate misleading stain (standard IHC practice).
How should I compare ADO staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell type and anatomical region before scoring, then use percent positive cells and an H-score for cellular staining (standard IHC practice). An H-score combines intensity categories with their corresponding percentages; apply the same thresholds to every slide (standard IHC practice). For extracellular signal, measure positive area or optical density per mm² of evaluable tissue separately from cellular scores (standard IHC practice; HPA tissue IHC profile). Normalise cell counts to eligible cells and area measurements to intact tissue area, excluding folds and necrosis (standard IHC practice). Report compartment, controls and acquisition or scanning settings alongside each comparison (standard IHC practice).
How can I distinguish credible ADO staining from an artefact?
Look for reproducible staining in the same cell type and compartment across intact sections, with little signal in no-primary controls (standard IHC practice). Medium staining is reported in neuronal cells of the cerebral cortex and in lung macrophages, while colon glandular cells are reported as not detected (HPA tissue IHC). These examples guide comparison but do not establish that every brown deposit is ADO, particularly given low staining-to-RNA consistency (HPA tissue IHC reliability). Treat isolated edge, necrotic or unexpected nuclear staining cautiously, and check for endogenous peroxidase signal (standard IHC practice; UniProt Q96SZ5 subcellular location not annotated). Confirm disputed patterns with an independent antibody or orthogonal measurement (standard IHC practice).
Boster reagents

Best ADO / 2-aminoethanethiol dioxygenase IHC Antibodies

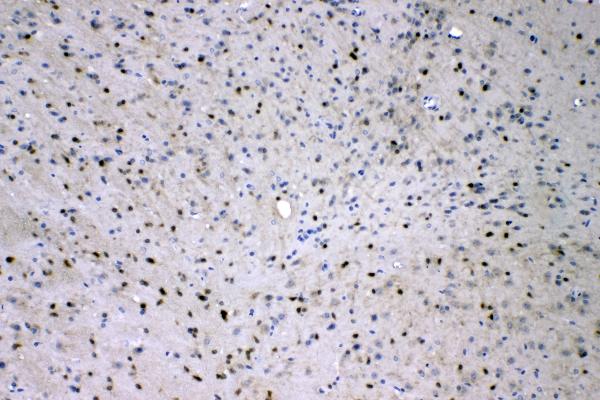
PB10032 has paraffin-section IHC images from rat and mouse brain and an IF/ICC image from A549 cells (catalog image captions).

Real IHC data IHC analysis of ADO using anti-ADO antibody (PB10032). ADO was detected in paraffin-embedded section of rat brain tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2μg/ml rabbit anti-ADO Antibody (PB10032) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-ADO Antibody ®
Cat # PB10032

PB10032 is the sole listed SKU; its IHC images show paraffin sections of rat and mouse brain (PB10032 IHC captions). Its IF/ICC image shows A549 cells (PB10032 IF caption).

Which to pick: Choose PB10032 for paraffin-section tissue IHC in rat or mouse brain, supported by its own images; the fixative is unreported (PB10032 IHC captions). Choose PB10032 for IF/ICC in A549 cells, supported by its cell image (PB10032 IF caption). For cross-species planning, PB10032 lists Human, Mouse and Rat reactivity, but the supplied IHC images cover only rat and mouse (catalog reactivity; PB10032 IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q96SZ5 (AEDO_HUMAN, 2-aminoethanethiol dioxygenase).
  2. Human Protein Atlas. ADO tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. ADO subcellular location (ICC-IF): Highest expression in PC-3: 73.8 nTPM.
  4. Human Protein Atlas. ADO antibody validation summary (2 antibodies).
  5. The impact of adenosine and an A2A adenosine receptor agonist on the ACh-induced increase in intracellular calcium of the glomus cells of the cat carotid body. Brain research 2009 — PMC2783842.
  6. Taurine Synthesis by 2-Aminoethanethiol Dioxygenase as a Vulnerable Metabolic Alteration in Pancreatic Cancer. Biomolecules & therapeutics 2025 — PMC11704412.
  7. Amplification of spatially isolated adenosine pathway by tumor-macrophage interaction induces anti-PD1 resistance in hepatocellular carcinoma. Journal of hematology & oncology 2021 — PMC8627086.
  8. Integrated multiomics revealed adenosine signaling predict immunotherapy response and regulate tumor ecosystem of melanoma. Human genomics 2024 — PMC11404024.
  9. PubMed PMID:15164054 — UniProt-cited evidence.
  10. PubMed PMID:15489334 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.