ARR3 / Arrestin-C · IHC design guide

Design Immunohistochemistry for ARR3

Plan ARR3 IHC-P around cytoplasmic staining in retinal cones (HPA tissue IHC). Start the catalog antibody A06100 at 2 μg/mL (datasheet) and include an HPA-negative tissue as a comparison (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ARR3 (IHC for ARR3): expected localisation Cone cytoplasm in retina (HPA tissue IHC), antibody A06100, validated IHC image, and IHC protocol steps
Printable ARR3 IHC protocol sheet — expected localisation Cone cytoplasm in retina (HPA tissue IHC), antibody A06100, controls and protocol steps. Open the full ARR3 IHC guide →

ARR3 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cone cytoplasm in retina (HPA tissue IHC)
Staining pattern Cytoplasmic staining in retinal cones; texture unreported (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Retina
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Cone-poor retinal fields may show little signal (HPA tissue IHC)
Regulation No expression regulator specified (UniProt)
Isoform / epitope 2 isoforms; epitope coverage unspecified (UniProt)
Section 1

Recommended ARR3 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is accompanied by published ARR3 staining protocols for mouse retinal sections (PMC13276656) and retinoblastoma samples (PMC8458383).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleTissue sections; selected-image fixative not specified (standard IHC workflow)
FixationImage fixative and duration unreported (datasheet A06100); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-ARR3, 2 μg/mL (datasheet A06100)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultARR3-positive staining in photoreceptor cells of retina (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in cones in retina. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 retrieval at 95–98 °C for 20 min (page antigen retrieval); the retinal study used 98 °C for 30 min (PMC13276656).
Section 2

What Is the Expected ARR3 Staining Pattern?

ARR3 should stain retinal cones, with cytoplasmic expression reported by HPA; UniProt also places it in photoreceptor inner and outer segments and retinal inner plexiform regions (HPA: Enhanced tissue IHC; UniProt P36575: tissue specificity and subcellular location). ARR3 has no transmembrane segment (UniProt P36575: topology). Interpret chromogenic staining against retinal cell identity and compartment, using the HPA pattern as the tissue IHC reference.

What am I looking at on my slide?
Cytoplasmic staining in retinal cones, with a medium signal in the photoreceptor layer.This fits the reported cone pattern and photoreceptor staining level (HPA: tissue IHC). Assess whether the signal follows recognizable cone cells and segments, rather than relying on color intensity alone.
Staining confined to nuclei, without a corresponding cytoplasmic cone pattern.A nuclear-only result does not match the reported retinal localization (HPA: cytoplasmic expression in cones; UniProt P36575: photoreceptor segments). Review morphology and controls before scoring it as ARR3 positive.
Strong staining in retinal cells that cannot be identified as cones.The cell identity conflicts with the HPA cone pattern (HPA: tissue IHC). Cross-reactivity or endogenous detection activity are possible IHC causes; neither can be assigned from appearance alone (standard IHC practice).
Color spread across retinal layers, extracellular spaces, or most cells without clear boundaries.Diffuse signal cannot establish cone-restricted expression (HPA: cytoplasmic expression in cones). Uneven reagent coverage, nonspecific binding, or excess chromogen development can produce background (standard IHC practice).
No discernible photoreceptor signal in a retinal section with preserved cone morphology.This conflicts with the HPA retinal positive reference, although its reported level is medium (HPA: tissue IHC). Check the positive control and detection workflow before interpreting the sample as ARR3 negative.
💡Expected ARR3 appearanceCall a section positive when retinal cones show discernible cytoplasmic staining at an approximately medium photoreceptor level; isolated nuclear or widespread non-cone color is suspect (HPA: tissue IHC).
How each factor affects the staining
Retinal tissue and cell identityHPA reports tissue-enriched retinal RNA, cytoplasmic cone expression, and medium staining in photoreceptor cells (HPA: tissue IHC). Match the stain to cone morphology; the RNA result supports tissue choice but does not identify a stained cell.
Negative tissue comparisonHPA reports no detection in adipocytes from adipose tissue and glandular cells from adrenal gland (HPA: tissue IHC). These are comparison patterns, not proof that every cell in either tissue must be unstained.
Compartment and topologyUniProt places ARR3 in photoreceptor inner and outer segments and the retinal inner plexiform regions, and lists no transmembrane segment (UniProt P36575). HPA describes retinal cone staining as cytoplasmic (HPA: tissue IHC).
Antibody validationHPA assigns Enhanced reliability to tissue IHC because antibody staining agrees strongly with RNA data; HPA063129 is listed as IHC Enhanced (HPA: tissue IHC and antibody record). This supports pattern interpretation, not a guarantee for every section.
Isoforms and processingUniProt lists two ARR3 isoforms, no signal peptide or propeptide, and a chain spanning residues 1–388 (UniProt P36575). The supplied sources do not identify the IHC antibody epitope or establish isoform-specific staining.
IF/ICC Q: Should Golgi staining define the retinal IHC result?No. HPA reports approved Golgi and additional vesicle localization in ICC-IF, while its retinal tissue IHC describes cytoplasmic cones (HPA: subcellular ICC-IF; HPA: tissue IHC). Assess each application against its own evidence.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Retinal positive control shows no cone signal.The HPA reference predicts retinal photoreceptor staining at a medium level (HPA: tissue IHC); the failed result alone does not identify which workflow step failed.Confirm cone morphology, antibody coverage, chromogen development, and that the detection system recognizes the primary antibody (standard IHC practice). Repeat with a working positive control before scoring samples.
Retinal section has nuclear-only staining.Nuclear-only color conflicts with cytoplasmic cone expression and photoreceptor segment localization (HPA: tissue IHC; UniProt P36575). Its cause is unresolved from the slide alone.Compare a no-primary control and the retinal positive reference; verify that the color lies within identified cones before calling ARR3 positive (standard IHC practice).
Non-cone cells stain as strongly as cones.The distribution departs from the reported cone pattern (HPA: tissue IHC). Cross-reactivity or endogenous detection activity may contribute (standard IHC practice).Check cell identity, a no-primary control, and the detection system's endogenous-activity controls; reassess primary antibody concentration if nonspecific staining persists (standard IHC practice).
Most of the section has diffuse brown color.Widespread color obscures the cone-restricted pattern (HPA: tissue IHC). Incomplete blocking, inadequate washes, or excess chromogen development are general IHC possibilities (standard IHC practice).Inspect the no-primary control; optimize blocking, washing, and development time one variable at a time, then recheck whether cone boundaries become distinguishable (standard IHC practice).
An HPA-negative comparison tissue shows staining.The result differs from the reported cell-level pattern, such as no detection in adipose-tissue adipocytes (HPA: tissue IHC). Other cells or background could account for the color.Identify the stained cell type and review control slides before treating the whole tissue as ARR3 positive; compare under the same detection conditions (standard IHC practice).
Golgi-like puncta appear in an ICC-IF image.HPA reports Golgi localization with additional vesicle staining in ICC-IF (HPA: subcellular ICC-IF). That observation does not establish the expected chromogenic retinal IHC pattern.Evaluate the ICC-IF image against its own controls and HPA subcellular reference; score retinal IHC against cytoplasmic cone staining (HPA: subcellular ICC-IF; HPA: tissue IHC).

Sample controls for ARR3 IHC & IF

🧪Run retina first: photoreceptor cells should stain at the reported medium level (HPA: retina, photoreceptor cells, Medium). Run adipose tissue as a negative comparator (HPA: adipocytes, Not detected); on the retina slide, assess non-photoreceptor cells as internal background, without assuming every such cell is ARR3-negative (HPA: photoreceptor cells, Medium).
Positive control tissue: Retina (Photoreceptor cells, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show ARR3 in HEK293, U2OS, hTERT-RPE1, hTERT-RPE1 (serum starved), Sperm, with annotated localisation: Golgi apparatus (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; a concentration-matched isotype control for a monoclonal antibody or host-matched normal IgG for a polyclonal antibody; and, if available, ARR3 knockout tissue or a validated peptide-block control (standard IHC practice). For chromogenic retina IHC, quench endogenous peroxidase and distinguish pigment from reaction product; for IF, check retinal autofluorescence with a no-primary control (standard IHC/IF practice).
⚠️Feasibility: No target-specific fixation window or retrieval dependence is reported in the supplied evidence; optimize paraffin-section retrieval empirically (supplied ARR3 evidence; standard IHC practice). The A06100 mouse-spleen IHC caption reports 2 µg/ml, but its fixative is unreported (selected tissue-IHC caption). The evidence does not establish that frozen sections or IF/ICC are easier than paraffin IHC; retinal pigment and autofluorescence require careful background assessment (standard IHC/IF practice).

HPA tissue IHC evidence for ARR3

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Retina Photoreceptor cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced ARR3 IHC Tips

Troubleshoot ARR3 staining in paraffin sections by checking retrieval, retinal cell identity, subcellular pattern and controls before scoring chromogenic signal.

How should I retrieve ARR3 in paraffin sections when staining is weak?
Start with citrate buffer at pH 6.0, heated to 95–98 °C for 20 min (page antigen-retrieval rule). Let sections cool in the buffer before washing, then compare the same antibody concentration across retrieval conditions so changes in signal have a clear cause (standard IHC practice). Examine retinal photoreceptor cells as the tissue reference, because ARR3 shows cytoplasmic cone staining there (HPA: retina tissue IHC profile). If signal remains weak, check section integrity and the detection controls before extending heating; excessive retrieval can damage morphology and make compartment-level interpretation unreliable (standard IHC practice).
Could fixation explain weak or patchy ARR3 staining?
ARR3-specific sensitivity to fixation is unknown from the supplied evidence, and the catalog image does not state its fixative (A06100 tissue-IHC caption). Record fixative, fixation duration and section thickness for each sample, then compare matched sections processed with the same citrate pH 6.0, 95–98 °C, 20 min retrieval (page antigen-retrieval rule; standard IHC practice). Use retinal photoreceptor staining as a positive tissue reference rather than treating a weak unknown tissue as proof of fixation damage (HPA: retina tissue IHC profile). If morphology is lost or staining varies between section edges and centers, troubleshoot processing and retrieval alongside fixation before drawing a target-specific conclusion (standard IHC practice).
Which ARR3 staining pattern should I accept as plausible in retina?
Look for cytoplasmic signal in retinal cones when assessing paraffin-section staining (HPA: retina tissue IHC profile). ARR3 is also described in photoreceptor inner segments, outer segments and inner plexiform regions, with outer-segment ciliary localisation noted separately (UniProt P36575: tissue specificity and subcellular location). Compare the chromogenic signal with a counterstain and preserved retinal architecture at matched magnification, scoring the photoreceptor compartment rather than every dark pixel (standard IHC practice). A strongly nuclear-only pattern or diffuse staining across unrelated cells needs control-based review before attribution to ARR3; the supplied retinal IHC profile supports cone cytoplasmic staining (HPA: retina tissue IHC profile; standard IHC practice).
Can this antibody distinguish ARR3 isoforms or reveal an inaccessible epitope?
Do not assign staining to one splice form without an antibody epitope mapped to an isoform-specific sequence; ARR3 has 2 listed isoforms (UniProt P36575: alternative splicing). Its annotated chain spans residues 1–388, with no signal peptide, propeptide or transmembrane segment, but those annotations do not identify this antibody’s binding site (UniProt P36575: processing and topology). Compare the manufacturer’s epitope information, if available, with both isoform sequences before making an isoform claim (standard IHC practice). For weak paraffin-section staining, first verify the page’s citrate pH 6.0 retrieval and a retinal positive reference; neither can establish isoform selectivity (page antigen-retrieval rule; HPA: retina tissue IHC profile).
How should I check ARR3 by IF alongside this chromogenic IHC assay?
Treat IF as a separate assay and multiplex ARR3 with a validated cone marker to check whether signal falls in the expected retinal cells (HPA: retina tissue IHC profile; standard IF practice). Choose a fluorophore channel after measuring unstained-section autofluorescence, and include single-label controls to assess spectral bleed-through (standard IF practice). Because ARR3 has no annotated transmembrane segment and retinal IHC shows cytoplasmic staining, optimise gentle permeabilisation for access to intracellular epitopes while preserving photoreceptor morphology (UniProt P36575: topology; HPA: retina tissue IHC profile; standard IF practice). Do not infer an IF fixation condition or performance from the mouse-spleen chromogenic caption, which gives neither IF data nor a fixative (A06100 tissue-IHC caption).
How can I separate ARR3 signal from chromogenic background?
Run a no-primary control through the same secondary reagent and chromogen steps, and compare it with a retinal positive section (standard IHC practice; HPA: retina tissue IHC profile). Apply a peroxidase block before horseradish-peroxidase detection and inspect tissue without primary antibody for endogenous enzyme activity; these are general chromogenic workflow checks (standard IHC practice). If staining is widespread, review blocking, antibody concentration, wash stringency and DAB development time one variable at a time, keeping the counterstain consistent (standard IHC practice). The A06100 image reports mouse spleen staining at 2 µg/ml, but its caption does not establish retinal specificity or the fixative used (A06100 tissue-IHC caption).
What should I quantify when ARR3 staining varies across sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the retinal region and photoreceptor-cell denominator before scoring, because the supported tissue-IHC pattern is cytoplasmic staining in cones (HPA: retina tissue IHC profile). Report the percentage of positive cells and an intensity-weighted H-score on its 0–300 scale, with thresholds fixed before comparing groups (standard IHC scoring practice). Normalise counts to the number of evaluable photoreceptor cells, or report positive-cell density per mm² of a consistently defined retinal region when cell counting is impractical (standard IHC practice). Exclude folds, torn areas and poorly preserved tissue by the same prespecified rules for every section, and retain representative images alongside the scores (standard IHC practice).
When is an apparent ARR3-positive result likely to be artefactual?
Give most weight to cytoplasmic staining in retinal cones with preserved photoreceptor architecture (HPA: retina tissue IHC profile). Check unexpected nuclear-only or broadly distributed staining against the expected photoreceptor inner and outer segment distribution, while recognising that these references describe different localisation observations (UniProt P36575: tissue specificity; HPA: retina tissue IHC profile). Edge-restricted signal, staining over necrotic areas or colour in a no-primary control warrants review of section quality, detection chemistry and endogenous enzyme activity (standard IHC practice). The mouse-spleen image documents staining with A06100 at 2 µg/ml; by itself, that caption does not validate the identity of every stained cell (A06100 tissue-IHC caption).
Boster reagents

Best ARR3 / Arrestin-C IHC Antibodies

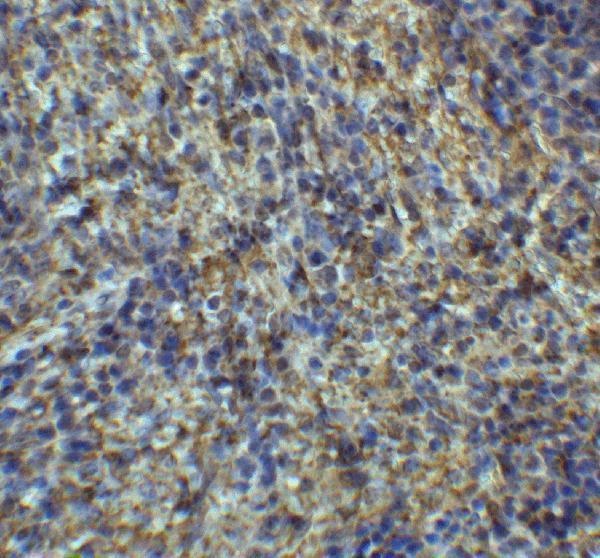
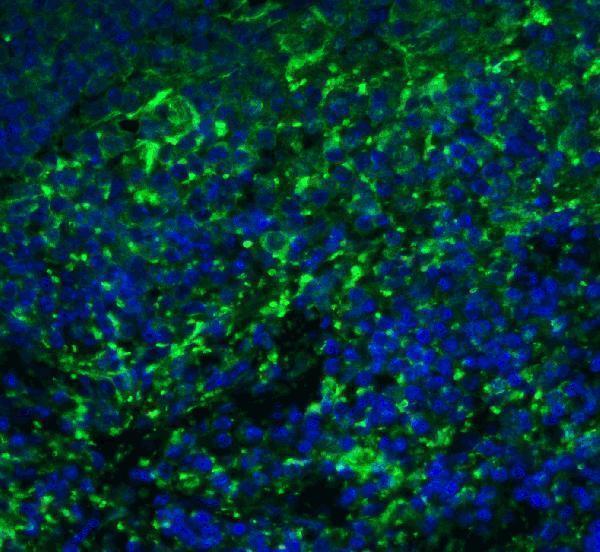
A06100 is an anti-ARR3 antibody listed for IHC-P and IF, with human, mouse and rat reactivity (catalog: applications and reactivity). Its IHC and IF images show mouse spleen tissue (catalog: image captions).

Real IHC data Immunohistochemistry of ARR3 in mouse spleen tissue with ARR3 antibody at 2 μg/ml.
Anti-Arrestin-C ARR3 Antibody
Cat # A06100

A06100 is listed for IHC-P and IF in human, mouse and rat samples (catalog: applications and reactivity). Its IHC and IF captions show mouse spleen tissue at 2 μg/mL and 20 μg/mL, respectively (catalog: IHC and IF image captions).

Which to pick: For tissue IHC, choose A06100 for paraffin sections: IHC-P is listed and the IHC caption shows mouse spleen tissue at 2 μg/mL; the fixative is unreported (catalog: applications and IHC image caption). For IF, A06100 has a mouse spleen image at 20 μg/mL; ICC is not listed (catalog: IF image caption and applications). For human or rat tissue, A06100 lists reactivity, although its supplied images show mouse spleen only; it is a rabbit antibody with no clone specified (catalog: reactivity, image captions, host and clone).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P36575 (ARRC_HUMAN, Arrestin-C).
  2. Human Protein Atlas. ARR3 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. ARR3 subcellular location (ICC-IF): Mainly localized to the Golgi apparatus. In addition localized to vesicles..
  4. Human Protein Atlas. ARR3 antibody validation summary (1 antibodies).
  5. High temporal frequency light response in mouse retina requires FAT3 signaling in bipolar cells. bioRxiv : the preprint server for biology 2024 — PMC10635074.
  6. ERG responses to high-frequency flickers require FAT3 signaling in mouse retinal bipolar cells. The Journal of general physiology 2025 — PMC11793021.
  7. ARR3 variant-induced cone mosaicism alters cone subtype composition and disrupts phototransduction. Zoological research 2026 — PMC13276656.
  8. A high-risk retinoblastoma subtype with stemness features, dedifferentiated cone states and neuronal/ganglion cell gene expression. Nature communications 2021 — PMC8458383.
  9. PubMed PMID:8224247 — UniProt-cited evidence.
  10. PubMed PMID:8308033 — UniProt-cited evidence.
  11. PubMed PMID:8612728 — UniProt-cited evidence.