GRK6 / G protein-coupled receptor kinase 6 · IHC design guide

Design Immunohistochemistry for GRK6

Plan chromogenic GRK6 IHC in paraffin sections using the IHC-validated antibody at a starting concentration of 5 μg/mL (datasheet). Compare cytoplasmic staining across cell populations, with immune-cell subsets expected to stain most strongly (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for GRK6 (IHC for GRK6): expected localisation Cytoplasmic staining in tissue (HPA tissue IHC), antibody A03623-1, validated IHC image, and IHC protocol steps
Printable GRK6 IHC protocol sheet — expected localisation Cytoplasmic staining in tissue (HPA tissue IHC), antibody A03623-1, controls and protocol steps. Open the full GRK6 IHC guide →

GRK6 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in tissue (HPA tissue IHC)
Staining pattern Broad cytoplasmic staining; strongest in immune-cell subsets (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Liver+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections (standard IHC practice; not target-specific)
Caveat Staining has low concordance with RNA expression (HPA tissue IHC)
Regulation RNA is enhanced in bone marrow (HPA tissue RNA)
Isoform / epitope 3 isoforms; no transmembrane segment; map the epitope (UniProt)
Section 1

Recommended GRK6 IHC & IF Protocols

The catalog antibody protocol is paired with one published GRK6 IHC protocol using rat striatal paraffin sections (PMC3864941).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleTissue sections; selected-image fixative not specified (standard IHC workflow)
FixationImage fixative and duration unreported (datasheet A03623-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-GRK6, 5 μg/mL (datasheet A03623-1)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultGRK6-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression, most abundant in subsets of immune cells. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 retrieval at 95–98 °C for 20 min (page antigen retrieval); the published protocol does not report retrieval (PMC3864941).
Section 2

What Is the Expected GRK6 Staining Pattern?

In paraffin-section IHC, expect predominantly cytoplasmic GRK6 staining, often strongest in subsets of immune cells (HPA: tissue IHC profile). GRK6 is also associated with membranes but has no transmembrane segment (UniProt P43250: subcellular location and topology). HPA rates its tissue IHC data Approved while reporting low consistency between antibody staining and RNA expression; interpret individual tissue patterns with that limitation (HPA: tissue IHC reliability).

What am I looking at on my slide?
Cytoplasmic stain is strong in kidney tubule cells or colon glandular cells.Both cell populations are listed as High in HPA tissue IHC (HPA: kidney and colon). Score the named cells against neighboring tissue and the section's negative control; a strong signal alone does not resolve the reported staining–RNA inconsistency (HPA: reliability description).
Stain is predominantly nuclear, with little cytoplasmic signal.That distribution departs from HPA's ubiquitous cytoplasmic IHC profile (HPA: tissue IHC). Review morphology and counterstain, then repeat with appropriate controls before assigning GRK6 to nuclei. Membrane association without a transmembrane segment does not predict a nuclear IHC pattern (UniProt P43250: location and topology).
Strong stain appears in liver cholangiocytes or oral squamous epithelium.HPA lists these cells as Not detected (HPA: liver and oral mucosa). Check whether the stained cells were identified correctly; persistent signal may reflect cross-reactivity or endogenous detection activity (general IHC practice). A negative HPA entry is a comparison point, not proof that every specimen must be blank.
Brown signal spreads across tissue, including spaces or cells lacking clear morphology.Treat diffuse, poorly localized color as background until controls support a cellular pattern (general IHC practice). Compare a no-primary control, inspect washing and blocking, and avoid calling weak widespread color positive solely because GRK6 is widely expressed (UniProt P43250: tissue specificity).
Kidney tubules and lymph-node non-germinal-center cells show no signal.Both are listed as High in HPA tissue IHC (HPA: kidney and lymph node). First verify that the expected cell populations are present. If they are, check the staining run and antibody conditions; absence in one section cannot establish absent GRK6 expression.
💡Expected GRK6 appearanceCall a section positive when identifiable cells show clear cytoplasmic staining, potentially strong in kidney tubules or colon glands (HPA: tissue IHC); nuclear-only color or uniform diffuse deposits warrant investigation (general IHC practice).
How each factor affects the staining
Tissue and cell selectionGRK6 is widely expressed (UniProt P43250: tissue specificity), yet HPA reports different cell-level IHC results: kidney tubules High, salivary glandular cells Low, and liver cholangiocytes Not detected (HPA: tissue IHC). Choose comparison cells by cell type, not by organ name alone.
Subcellular evidence across applicationsHPA describes cytoplasmic tissue IHC but approved mitochondrial localization in ICC-IF (HPA: tissue IHC and subcellular ICC-IF). UniProt lists GRK6 as membrane-associated without a transmembrane segment (UniProt P43250: location and topology). These observations should be recorded by assay rather than forced into one identical visual pattern.
Antibody validationHPA lists two antibodies with Approved IHC status, HPA015327 and HPA018903 (HPA: antibodies). The tissue IHC profile also carries a low-consistency warning against RNA expression (HPA: reliability description). Use controls and cell-level comparisons when interpreting an unexpected stain.
Isoforms and epitope coverageUniProt lists three isoforms, GRK6A, GRK6B and GRK6C (UniProt P43250: isoforms). The supplied record does not map either antibody's epitope to those isoforms, so an isoform-specific IHC interpretation is unsupported without further antibody information.
Processing and modified residuesUniProt lists no signal peptide or propeptide and identifies several phosphorylated residues (UniProt P43250: processing and modified residues). The payload provides no evidence that these features change paraffin-section staining, retrieval needs or tissue positivity; do not use them to explain a failed stain.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected positive cells are blank.An absent signal in HPA-High kidney tubules or colon glands may indicate a staining-run problem, though specimen-level variation remains possible (HPA: tissue IHC; general IHC practice).Confirm the expected cells are present; inspect a positive control, antibody dilution, retrieval record and detection reagents (general IHC practice). No GRK6-specific retrieval condition or dilution is supplied.
The whole section has a diffuse brown haze.Background can arise from incomplete blocking, washing or detection controls (general IHC practice). The haze does not match HPA's described cellular cytoplasmic pattern (HPA: tissue IHC).Compare the no-primary control; review blocking, washes and chromogen development, then score only stain tied to identifiable cells (general IHC practice).
Signal is strong in an HPA Not detected cell population.Misidentified cells, cross-reactivity or endogenous detection activity are possibilities (HPA: liver cholangiocytes, oral and vaginal squamous epithelium; general IHC practice).Recheck morphology and an appropriate negative control. If signal persists, describe the observation and the HPA discrepancy instead of treating either as definitive.
Staining appears predominantly nuclear.This conflicts with the HPA cytoplasmic tissue IHC profile; a nuclear pattern is not established by UniProt's membrane annotation (HPA: tissue IHC; UniProt P43250: location).Check counterstain, cellular boundaries and controls. Repeat the IHC stain if needed before reporting nuclear GRK6 (general IHC practice).
A weak signal is difficult to score in salivary glandular cells.HPA lists these cells as Low, whereas kidney tubule cells are High (HPA: tissue IHC). A faint result can therefore be harder to distinguish from background.Compare identifiable glandular cells with a no-primary control and a suitable HPA-High tissue on the same run; report uncertain signal as equivocal (general IHC practice).
IF/ICC shows mitochondria while tissue IHC looks cytoplasmic. Is that inconsistent?HPA reports approved mitochondrial localization for ICC-IF and a cytoplasmic profile for tissue IHC (HPA: subcellular ICC-IF and tissue IHC). The assays describe localization at different visual resolutions.Record each assay's observed compartment and controls separately. Do not require a mitochondrial pattern to score paraffin-section chromogenic IHC (HPA: tissue IHC and subcellular ICC-IF).

Sample controls for GRK6 IHC & IF

🧪Run duodenum first; its glandular cells should stain for GRK6 (HPA: High in duodenal glandular cells). Use oral mucosa squamous epithelial cells as the negative tissue (HPA: Not detected); cells without glandular staining on the duodenal slide should show background chromogen only, although HPA identifies no validated internal-negative duodenal cell type (HPA: duodenum row).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Liver (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show GRK6 in A-431, U-251MG, U2OS, with annotated localisation: Mitochondria (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; an isotype control matched to the primary antibody’s host species, subclass and concentration; and a GRK6 knockout specimen or validated peptide-block control (standard IHC practice). For chromogenic detection, quench endogenous peroxidase and check the duodenal section for residual background before scoring glandular cells (standard IHC practice; HPA: High in duodenal glandular cells).
⚠️Feasibility: A target-specific fixation window and fixation effect are unreported in the supplied evidence; the selected A03623-1 small-intestine IHC caption also does not state a fixative (selected-SKU caption). Antigen-retrieval dependence is unreported, so optimize retrieval empirically for paraffin sections; the supplied evidence does not establish whether frozen sections or IF would be easier (selected-SKU caption; HPA: tissue and subcellular entries). Check intestinal glandular staining against the same section’s background and the no-primary control before scoring (HPA: High in duodenal glandular cells; standard IHC practice).

HPA tissue IHC evidence for GRK6

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Caudate Neuronal cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Oral mucosa Squamous epithelial cells Not detected Protein (IHC) HPA →
Vagina Squamous epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced GRK6 IHC Tips

Troubleshoot GRK6 chromogenic IHC in paraffin sections by checking retrieval, compartment, cell type and controls before comparing staining intensity.

How should I retrieve GRK6 in paraffin sections when staining is weak?
Start with citrate buffer at pH 6.0 for heat induced epitope retrieval at 95–98 °C for 20 minutes (page retrieval setting). Let sections cool in buffer, then keep cooling, washing and detection conditions identical across the comparison set (standard IHC practice). If staining remains weak, check a known positive control and titrate the primary antibody before changing retrieval conditions; the selected tissue caption reports 5 µg/mL, but gives no retrieval method (selected A03623-1 tissue-IHC caption). If exploring another buffer or heating duration, compare it directly with the page setting while watching for tissue damage and increased background (standard IHC practice).
Could fixation explain variable GRK6 staining between my paraffin samples?
GRK6 specific sensitivity to fixation is unknown from the supplied evidence, and the selected tissue-IHC caption does not state a fixative (selected A03623-1 tissue-IHC caption). Record fixative, fixation duration, tissue thickness and processing history for each specimen so differences can be traced (standard IHC practice). Compare sections processed together under the same citrate pH 6.0, 95–98 °C, 20 minute retrieval setting, using a reference section in each run (page retrieval setting; standard IHC practice). If results differ, test matched material with controlled processing before assigning a GRK6 specific fixation effect; the available tissue staining patterns do not establish one (standard IHC practice).
Should GRK6 appear on membranes or throughout the cytoplasm?
Assess both cytoplasmic and membrane associated staining: GRK6 is annotated as membrane associated without a transmembrane segment, while tissue IHC is described as broadly cytoplasmic (UniProt P43250 subcellular location and topology; HPA tissue IHC profile). The separate ICC/IF record reports mitochondrial localisation, so a punctate pattern may warrant follow up rather than automatic rejection (HPA subcellular: mitochondria approved). For chromogenic sections, record compartment and cell type separately, since the selected small intestine image establishes tissue staining but does not specify a subcellular pattern (selected A03623-1 tissue-IHC caption). Compare patterns at matched magnification with no primary controls and a cell type expected to stain, while checking section edges and damaged areas (standard IHC practice; HPA tissue IHC profile).
Can my IHC distinguish GRK6 isoforms or phosphorylation states?
Do not assign a staining pattern to one isoform without an antibody epitope map or isoform specific validation: GRK6 has three listed isoforms, GRK6A, GRK6B and GRK6C (UniProt P43250 isoforms). The supplied product caption identifies GRK6 staining at 5 µg/mL but gives no epitope or isoform recognition data (selected A03623-1 tissue-IHC caption). GRK6 also has reported phosphosites at residues 484, 485, 566 and 568; ordinary GRK6 staining cannot establish phosphorylation at those sites (UniProt P43250 modified residues; standard IHC interpretation). To make either claim, obtain epitope information and test the relevant isoforms or phosphosite controls alongside the chromogenic assay (standard antibody validation practice).
How can IF clarify ambiguous GRK6 IHC localisation?
Use IF as a follow up to chromogenic IHC by multiplexing GRK6 with a marker for the cell population being assessed; subsets of immune cells show abundant tissue IHC staining (HPA tissue IHC profile; standard IF practice). Choose a red or far red fluorophore after measuring autofluorescence in unstained sections, and keep single stain controls for channel bleed through (standard IF practice). GRK6 has no transmembrane segment, so determine whether the antibody epitope is intracellularly accessible before choosing permeabilisation; the supplied caption does not map that epitope (UniProt P43250 topology; selected A03623-1 tissue-IHC caption). Compare any mitochondrial overlap with the separate approved ICC/IF localisation record, while treating the resulting IF pattern as supporting evidence for the IHC interpretation (HPA subcellular: mitochondria approved; standard IF interpretation).
How do I separate weak GRK6 signal from chromogenic background?
Run a no primary control and a known positive section through the same retrieval, blocking and detection steps to locate nonspecific signal (standard IHC practice). For a peroxidase and DAB workflow, include a peroxide block, for example 3% hydrogen peroxide for 10 minutes, then inspect the no primary control for residual endogenous enzyme activity (standard chromogenic IHC practice). Titrate the IHC validated antibody around the caption's 5 µg/mL reference concentration while holding development time constant; that caption alone does not validate every paraffin workflow (selected A03623-1 tissue-IHC caption; standard IHC practice). Judge faint cytoplasmic staining against the tissue pattern and controls, since reported staining and RNA expression have low consistency (HPA tissue IHC reliability).
What should I score when comparing GRK6 across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because GRK6 tissue IHC is described as cytoplasmic and most abundant in subsets of immune cells (HPA tissue IHC profile). For a defined cell population, report percent positive cells and an H-score from 0–300 using intensity grades 0–3; for dispersed positive cells, report counts per mm² of viable tissue (standard IHC scoring practice). Normalise counts to viable area or to the number of eligible cells, and compare only sections stained and imaged under matched conditions (standard IHC scoring practice). Keep epithelial and immune cell scores separate where both are present, and state the positivity threshold before analysing samples (HPA tissue IHC profile; standard IHC scoring practice).
Which GRK6 staining patterns are convincing, and which suggest artefact?
A convincing pattern should recur in the expected cell population and compartment across intact sections and disappear from no primary controls (standard IHC interpretation). HPA reports high GRK6 staining in duodenal glandular cells and lymph node non germinal center cells, but no detected staining in liver cholangiocytes, providing cell level comparisons rather than universal positive or negative tissues (HPA tissue IHC). Investigate staining restricted to cut edges, necrotic regions or the no primary control, particularly when endogenous peroxidase could generate DAB signal (standard chromogenic IHC interpretation). Treat striking nuclear only staining or mitochondrial claims from DAB alone cautiously: GRK6 is membrane associated in UniProt, tissue IHC is described as cytoplasmic, and approved mitochondrial localisation comes from ICC/IF (UniProt P43250; HPA tissue IHC profile; HPA subcellular).
Boster reagents

Best GRK6 / G protein-coupled receptor kinase 6 IHC Antibodies

A03623-1 has IHC and IF images from human small intestine (catalog image captions). Its listed reactivity covers human, mouse and rat (catalog reactivity).

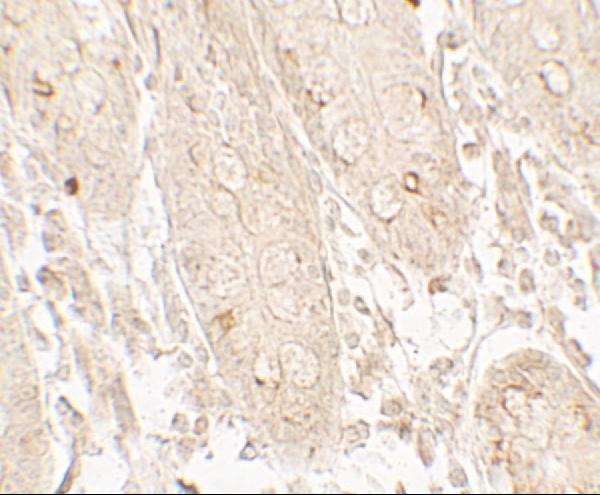
Real IHC data Immunohistochemistry of GRK6 in human small intestine tissue with GRK6 antibody at 5 μg/mL.
Anti-GRK6 Antibody
Cat # A03623-1

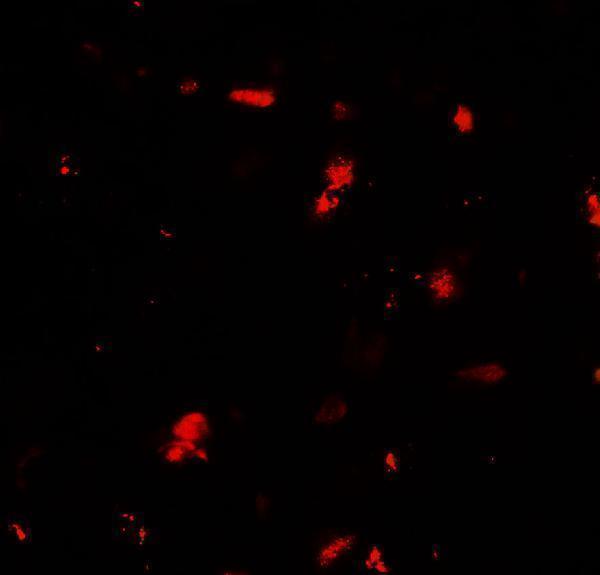
A03623-1 will render with its human small intestine IHC image at 5 μg/mL (A03623-1 IHC image caption). The catalog also lists IF and shows human small intestine IF at 20 μg/mL (catalog applications; A03623-1 IF image caption).

Which to pick: For tissue IHC, choose A03623-1: IHC-P is listed and its own IHC image shows human small intestine at 5 μg/mL; the fixative is unreported (catalog applications; A03623-1 IHC image caption). For IF, choose the same SKU based on its human small intestine IF image at 20 μg/mL; ICC validation is unreported (A03623-1 IF image caption; catalog applications). For mouse or rat samples, A03623-1 is the listed cross-species option, though the supplied IHC and IF images are human only (catalog reactivity; catalog image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P43250 (GRK6_HUMAN, G protein-coupled receptor kinase 6).
  2. Human Protein Atlas. GRK6 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. GRK6 subcellular location (ICC-IF): Localized to the mitochondria..
  4. Human Protein Atlas. GRK6 antibody validation summary (2 antibodies).
  5. Effect of Tianqi antitremor granules on behavioral manifestations and expression of G protein-coupled receptor kinase 6 and β-arrestin1 in levodopa-induced dyskinesia in a rat model of Parkinson's disease. Drug design, development and therapy 2013 — PMC3864941.
  6. GRK6 deficiency in mice causes autoimmune disease due to impaired apoptotic cell clearance. Nature communications 2013 — PMC3586722.
  7. G protein-coupled receptor kinase 6 deficiency promotes angiogenesis, tumor progression, and metastasis. Journal of immunology (Baltimore, Md. : 1950) 2013 — PMC3646980.
  8. G protein-coupled receptor kinase 6 is overexpressed in glioma and promotes glioma cell proliferation. Oncotarget 2017 — PMC5589575.
  9. PubMed PMID:8366096 — UniProt-cited evidence.
  10. PubMed PMID:10506199 — UniProt-cited evidence.
  11. PubMed PMID:15372022 — UniProt-cited evidence.