LEF1 / Lymphoid enhancer-binding factor 1 · IHC design guide

Design Immunohistochemistry for LEF1

Plan paraffin-section LEF1 IHC around nuclear staining in lymphoid tissue (HPA tissue IHC). Use lymph node non-germinal center cells as a positive reference and exclude cytoplasmic staining from scoring (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
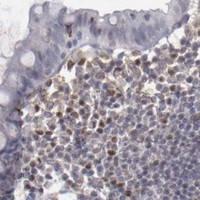
Immunohistochemistry protocol sheet for LEF1 (IHC for LEF1): expected localisation Nuclear staining in lymphoid tissue (HPA tissue IHC), antibody M00605-3, validated IHC image, and IHC protocol steps
Printable LEF1 IHC protocol sheet — expected localisation Nuclear staining in lymphoid tissue (HPA tissue IHC), antibody M00605-3, controls and protocol steps. Open the full LEF1 IHC guide →

LEF1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining in lymphoid tissue (HPA tissue IHC)
Staining pattern Nuclear staining in lymphoid tissue cells (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen)
Positive control ⓘ Lymph node+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Cytoplasmic staining was disregarded (HPA tissue IHC)
Regulation Higher in colon cancer than normal colon (UniProt)
Isoform / epitope 7 isoforms; epitope coverage is unspecified (UniProt; catalog data)
Section 1

Recommended LEF1 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol with three published LEF1 IHC protocols for paraffin sections (PMC12772540; PMC11479531; PMC13294606).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleTissue sections; selected-image fixative not specified (standard IHC workflow)
FixationImage fixative and duration unreported (datasheet M00605-3); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-LEF1, 1:1000-1:4000 (datasheet M00605-3)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
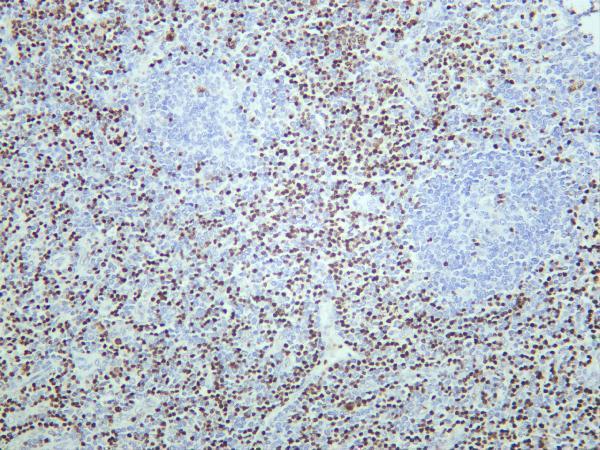
Expected resultLEF1-positive staining in non-germinal center cells of lymph node (HPA tissue IHC: High). HPA tissue profile: Nuclear expression in lymphoid tissue. No signal in the no-primary control.
💡Decision noteStart with Tris-EDTA pH 9.0 retrieval at 95–98 °C for 20 min for nuclear LEF1 (page retrieval rule); a published protocol uses citrate retrieval (PMC11479531).
Section 2

What Is the Expected LEF1 Staining Pattern?

LEF1 is a nuclear transcription factor with no transmembrane segment (UniProt Q9UJU2). In paraffin-section IHC, expect nuclear staining chiefly in lymphoid tissue, especially non-germinal center cells of lymph node and tonsil (HPA: high; tissue IHC reliability Enhanced). HPA reports medium consistency between staining and RNA data and disregards observed cytoplasmic staining (HPA: tissue IHC reliability description).

What am I looking at on my slide?
Distinct nuclear staining in non-germinal center cells of lymph node or tonsil.This matches the strongest supplied tissue examples (HPA: high in both cell populations) and the expected nuclear compartment (UniProt Q9UJU2; HPA: nuclear expression in lymphoid tissue). Evaluate the named cells rather than treating every cell in the section as an expected positive.
Predominantly cytoplasmic staining, with little nuclear signal.Do not score this as convincing LEF1 positivity: HPA observed and disregarded cytoplasmic staining (HPA: tissue IHC reliability description), while UniProt places LEF1 in the nucleus (UniProt Q9UJU2). Recheck compartment assignment against the counterstain.
Strong staining in cells expected to be negative, such as adipocytes.Adipocytes in adipose tissue are listed as not detected (HPA: adipose tissue IHC). Suspect nonspecific binding or endogenous detection activity before calling this biological expression (general IHC interpretation). Check whether the color is nuclear and whether omission controls retain it.
Haze or precipitate across nuclei and surrounding tissue.A diffuse deposit cannot establish the cell-restricted nuclear pattern reported for LEF1 (HPA: nuclear expression in lymphoid tissue). Uneven blocking, excess detection reagent, or chromogen deposit can obscure interpretation (general IHC practice); compare with a reagent-omission control.
No nuclear signal in non-germinal center cells of a lymph node positive control.The assay has failed to reproduce an HPA high-staining example (HPA: lymph node IHC). Review control integrity and the IHC-validated antibody’s documented paraffin-section conditions before interpreting an experimental sample as LEF1 negative (general IHC practice).
💡Expected LEF1 appearanceCall a section positive when staining is clearly nuclear and strong in lymph-node or tonsil non-germinal center cells (HPA: high in both); isolated cytoplasmic color is a false-positive pattern for scoring (HPA: cytoplasmic staining disregarded).
How each factor affects the staining
Tissue and cell selectionLymph node and tonsil non-germinal center cells provide high-staining references (HPA: tissue IHC). Appendix lymphoid tissue and bone-marrow hematopoietic cells are medium, so expect a less prominent reference pattern there (HPA: tissue IHC).
Negative-cell comparisonAdipose-tissue adipocytes and bronchial respiratory epithelial cells are listed as not detected (HPA: tissue IHC). Compare named cell populations; the HPA entries do not establish that every cell in either tissue is negative.
Antibody evidenceHPA002087 has Enhanced IHC validation; CAB019405 has Approved IHC validation (HPA: antibody entries). The tissue-level Enhanced label also carries a medium staining–RNA consistency description (HPA: tissue IHC); these labels do not prove specificity in every specimen.
Isoforms and processingUniProt lists 7 LEF1 isoforms and one annotated chain spanning residues 1–399, with no signal peptide or propeptide (UniProt Q9UJU2). This record supplies no antibody epitope, so it cannot predict which isoforms an IHC antibody detects.
IF/ICC Q: Where should signal appear?A: Mainly in the nucleoplasm (HPA: ICC-IF, approved); UniProt also notes nuclear bodies upon PIASG binding (UniProt Q9UJU2). This localisation answer does not define an IF/ICC protocol.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Lymph-node control lacks nuclear color.The assay or control may not have produced an interpretable positive result (HPA: high in non-germinal center cells; general IHC practice).Confirm the named cell population is present; check the IHC-validated antibody’s documented paraffin-section protocol, detection reagents, and a concurrently run positive control (general IHC practice).
Color is mainly cytoplasmic.HPA explicitly disregards cytoplasmic LEF1 staining (HPA: tissue IHC reliability description).Score nuclei against the counterstain and review reagent-omission controls for background (general IHC practice); do not count cytoplasmic color as the expected nuclear result (UniProt Q9UJU2).
Adipocytes show prominent color.This conflicts with the listed not-detected adipocyte pattern (HPA: adipose tissue IHC); nonspecific staining or endogenous activity is possible (general IHC practice).Check the cellular compartment and compare primary-antibody-omission and detection controls before assigning positivity (general IHC practice).
Diffuse color makes individual nuclei hard to score.Background or chromogen deposit may mask cell boundaries (general IHC practice), preventing comparison with HPA’s nuclear lymphoid pattern (HPA: tissue IHC).Inspect a control without primary antibody, then review blocking, washing, reagent amount, and chromogen development under the detection system’s instructions (general IHC practice).
Only a few cells stain in a lymphoid section.Cell composition and the field sampled may differ; HPA specifies non-germinal center cells for its high lymph-node and tonsil results (HPA: tissue IHC).Identify the relevant compartment on the counterstained section and compare like cell populations across control and test sections (general IHC practice).
A negative experimental section conflicts with a working positive control.Expression can differ by tissue and cell type: HPA reports high, medium, low, and not-detected examples (HPA: tissue IHC). The negative result alone does not identify its cause.Record the scored cell population and nuclear result, then compare it with the appropriate HPA tissue entry; keep the positive control in the same run (general IHC practice).

Sample controls for LEF1 IHC & IF

🧪Run tonsil first: non-germinal center cells should show nuclear LEF1 staining (HPA: High in tonsil non-germinal center cells; UniProt Q9UJU2: nucleus). Use adrenal gland as the negative tissue because its glandular cells are reported as not detected (HPA: Not detected in adrenal gland glandular cells); on the tonsil slide, cells without nuclear staining can serve as internal negative comparators, but the supplied HPA row does not identify a specific negative cell type.
Positive control tissue: Lymph node (Non-germinal center cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show LEF1 in REH, U-251MG, U2OS, with annotated localisation: Nucleoplasm (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; an isotype control matched to the primary antibody’s host species and clonality; and LEF1 knockout material, if available, as a biological negative (standard IHC practice). Check for endogenous peroxidase activity and nonspecific chromogen deposition in the tonsil section (standard chromogenic IHC practice).
⚠️Feasibility: A target-specific fixation window and fixation effect are unreported in the supplied evidence; the selected M00605-3 tonsil caption also leaves the fixative unreported (selected tissue-IHC caption). Antigen retrieval dependency is unreported, so optimize retrieval for the paraffin-section assay rather than infer it from HPA staining (standard IHC practice). The supplied evidence does not establish whether frozen sections or IF would be easier; in tonsil, assess background against the expected nuclear signal (UniProt Q9UJU2: nucleus).

HPA tissue IHC evidence for LEF1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Cytoplasmic staining observed and disregarded.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Lymph node Non-germinal center cells High Protein (IHC) HPA →
Tonsil Non-germinal center cells High Protein (IHC) HPA →
Appendix Lymphoid tissue Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →
Oral mucosa Squamous epithelial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Section 3

Advanced LEF1 IHC Tips

Troubleshoot LEF1 chromogenic IHC by assessing nuclear staining, tissue controls and section quality; the IF entry addresses the separate fluorescence workflow.

How should I retrieve LEF1 in paraffin sections with weak nuclear staining?
Use Tris-EDTA pH 9.0 heat-induced epitope retrieval at 95–98 °C for 20 min before chromogenic IHC (page retrieval rule: nuclear antigen). Process a tonsil control alongside study sections, using the same heating and cooling schedule for each (HPA: high in tonsil non-germinal center cells; standard IHC practice). If nuclei remain faint, check bath temperature, buffer pH, dewaxing and section adherence before extending retrieval in a small trial (standard IHC practice). Excess heating can damage morphology, so assess signal alongside preserved tissue architecture (standard IHC practice). Score crisp nuclear staining; HPA disregarded cytoplasmic staining (HPA tissue IHC: cytoplasmic staining disregarded).
Could fixation explain loss of LEF1 staining in my paraffin sections?
LEF1-specific sensitivity to fixation is unknown from the supplied evidence; the selected tonsil caption does not state a fixative (catalog antibody M00605-3 tissue-IHC caption). Record the fixative, fixation duration, specimen thickness and processing history for each case before attributing a negative result to LEF1 biology (standard IHC practice). Compare suspect sections with a tonsil control processed under the same conditions and stained in the same run (HPA: high in tonsil non-germinal center cells; standard IHC practice). If the control also loses nuclear signal, check section handling, retrieval and detection before interpreting the study section (standard IHC practice). Avoid inferring fixation tolerance from LEF1 phosphorylation or nuclear localisation (UniProt Q9UJU2; standard IHC practice).
What should I make of cytoplasmic staining when scoring LEF1 IHC?
Prioritise well-defined nuclear staining because LEF1 is nuclear and HPA reports nuclear expression in lymphoid tissue (UniProt Q9UJU2: nucleus; HPA tissue IHC: nuclear expression in lymphoid tissue). HPA specifically disregarded cytoplasmic staining when assessing this target (HPA tissue IHC: cytoplasmic staining disregarded). Examine the chromogenic deposit against the counterstained nuclear boundary at high magnification, especially in crowded lymphoid regions (standard IHC practice). LEF1 can occur in nuclear bodies upon PIASG binding, so a punctate nuclear pattern warrants assessment within intact nuclei (UniProt Q9UJU2: nuclear bodies upon PIASG binding; standard IHC practice). If staining is predominantly cytoplasmic, review antibody concentration, detection background and control sections before assigning positivity (standard IHC practice).
Can LEF1 isoforms or modifications alter the apparent IHC pattern?
LEF1 has 7 annotated isoforms, but the supplied evidence does not map the catalog antibody's epitope across them (UniProt Q9UJU2: isoforms 1–7; supplied catalog evidence). An absent nuclear signal therefore cannot identify which isoform is missing without independent epitope and isoform evidence (UniProt Q9UJU2: isoforms 1–7; standard IHC interpretation). Annotated modifications include phosphoserine at residue 132 and NLK-associated phosphorylation at residues 155 and 166 (UniProt Q9UJU2: modified residues). Their effect on this antibody's tissue staining is unreported, so avoid assigning a weak stain to phosphorylation alone (supplied catalog evidence). Compare staining with a consistently processed positive control and document the antibody's epitope if that information becomes available (standard IHC practice).
How can I assess LEF1 by multiplex IF alongside chromogenic IHC?
Treat IF as a separate assay and verify nuclear LEF1 signal with an independently validated antibody before comparing it with chromogenic IHC (UniProt Q9UJU2: nucleus; standard IF practice). Multiplex LEF1 with a marker that identifies the expected lymphoid cell population, and assess the stains in separate channels as well as together (HPA tissue IHC: nuclear expression in lymphoid tissue; standard IF practice). Choose fluorophores after checking tissue autofluorescence and spectral overlap, then include single-stain controls (standard IF practice). LEF1 has no transmembrane segment and is nuclear, so use permeabilisation sufficient for antibody access to the nuclear epitope (UniProt Q9UJU2: topology and localisation; standard IF practice). Optimise IF fixation and permeabilisation directly; no IF-specific fixation condition is supplied (supplied evidence; standard IF practice).
How do I distinguish LEF1 signal from diffuse chromogenic background?
Look for discrete nuclear staining in intact cells against a low-background section, using tonsil as a positive tissue control (HPA: high in tonsil non-germinal center cells; standard IHC practice). Diffuse cytoplasmic color should not be counted as LEF1 positivity because HPA disregarded cytoplasmic staining (HPA tissue IHC: cytoplasmic staining disregarded). Check whether background persists in a no-primary control, then review blocking, antibody concentration, wash steps and detection reagent exposure (standard IHC practice). For peroxidase-based detection, include a peroxidase block and inspect controls for endogenous enzyme activity (standard IHC practice). Titrate the primary antibody and DAB development together with the positive control, preserving interpretable nuclear morphology (standard IHC practice).
How should I quantify LEF1 in mixed lymphoid tissue? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and scoring region before examining treatment groups, then score nuclear LEF1 only (HPA tissue IHC: nuclear expression in lymphoid tissue; standard IHC practice). Report the percentage of positive nuclei and, when intensity is reproducible, an H-score based on nuclear intensity categories (standard IHC practice). For spatial comparisons, report positive-cell density per mm² of viable tissue or a defined compartment (standard IHC practice). Normalise each measure to the eligible cells or viable area actually assessed, rather than to the whole section when tissue composition varies (standard IHC practice). Keep retrieval, chromogen development, imaging and positivity thresholds consistent across cases, with a shared control in each run (standard IHC practice).
When is an unexpected LEF1-positive region biologically credible?
A credible result shows staining within intact nuclei and a plausible cell population, with a working positive control (UniProt Q9UJU2: nucleus; HPA tissue IHC: lymphoid nuclear expression; standard IHC practice). Non-germinal center cells in tonsil and lymph node are useful reference populations because HPA reports high staining there (HPA: high in tonsil and lymph node non-germinal center cells). LEF1 expression can also vary by tissue and disease context, including higher expression reported in colon cancer than normal colon (UniProt Q9UJU2: tissue specificity). Recheck isolated edge staining, necrotic regions, cytoplasmic color and deposits associated with endogenous peroxidase before calling a case positive (HPA tissue IHC: cytoplasmic staining disregarded; standard IHC practice). Confirm an unexpected pattern with independent evidence when its interpretation matters (standard IHC practice).
Boster reagents

Best LEF1 / Lymphoid enhancer-binding factor 1 IHC Antibodies

Anti-LEF1 antibodies have IHC images from human, mouse and rat tissues and an IF image from Caco-2 cells (catalog image captions).

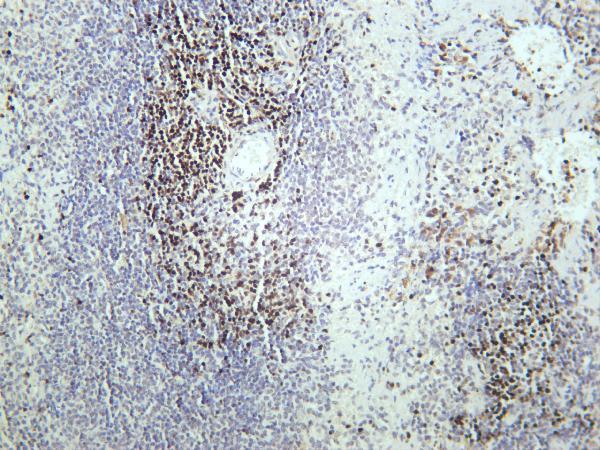
Real IHC data Human tonsil was stained with anti-LEF1 rabbit antibody
Anti-LEF1 Rabbit Monoclonal Antibody
Cat # M00605-3
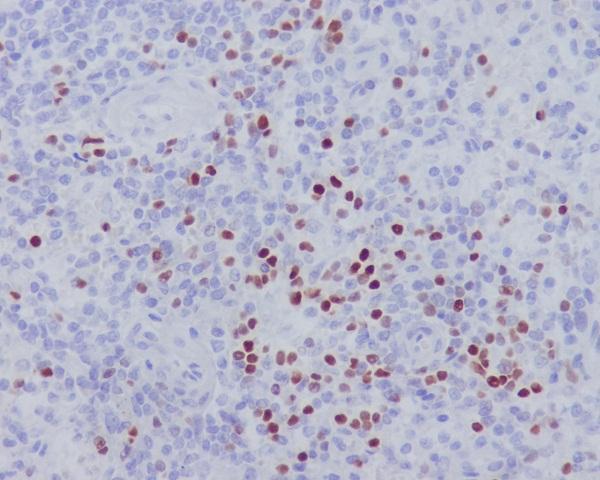
Real IHC data Immunohistochemical analysis of paraffin-embedded human spleen, using LEF1 Antibody.
Anti-LEF1 Rabbit Monoclonal Antibody
Cat # M00605
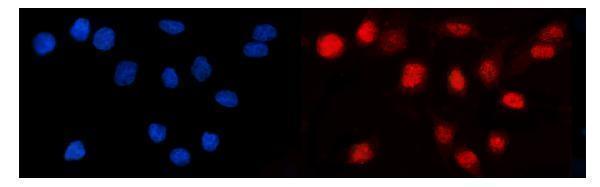
Real IF data IF analysis of LEF1 using anti-LEF1 antibody (A00605-2). LEF1 was detected in an immunocytochemical section of Caco-2 cells. Enzyme antigen retrieval was performed using IHC enzyme antigen retrieval reagent (AR0022) for 15 mins. The cells were blocked with 10% goat serum. And then incubated with 5 μg/mL rabbit anti-LEF1 Antibody (A00605-2) overnight at 4°C. DyLight®594 Conjugated Goat Anti-Rabbit IgG (BA1142) was used as secondary antibody at 1:100 dilution and incubated for 30 minutes at 37°C. The section was counterstained with DAPI. Visualize using a fluorescence microscope and filter sets appropriate for the label used.
Anti-LEF1 Antibody ®
Cat # A00605-2

M00605-3 has IHC images of human tonsil and human, mouse and rat spleen; M00605 has an IHC image of paraffin-embedded human spleen (catalog image captions). A00605-2 has an IF/ICC image of Caco-2 cells (catalog image caption).

Which to pick: For tissue IHC across species, choose M00605-3: it is monoclonal, lists human, mouse and rat reactivity, and has IHC images from all three species (catalog applications, reactivity and image captions). For paraffin sections, M00605 has a paraffin-embedded human spleen IHC image; the caption does not report the fixative (catalog image caption). For IF/ICC, choose A00605-2, whose Caco-2 IF/ICC image documents staining at 5 μg/mL (catalog image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9UJU2 (LEF1_HUMAN, Lymphoid enhancer-binding factor 1).
  2. Human Protein Atlas. LEF1 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. LEF1 subcellular location (ICC-IF): Mainly localized to the nucleoplasm..
  4. Human Protein Atlas. LEF1 antibody validation summary (2 antibodies).
  5. Lymphoid enhancer-binding factor 1 (LEF1) immunostaining as a surrogate for β-catenin (CTNNB1) mutations. Journal of clinical pathology 2025 — PMC12772540.
  6. Clinicopathological features of primary cold agglutinin disease in the Japanese population: Heterogeneous characteristics and diagnostic challenges. Journal of clinical and experimental hematopathology : JCEH 2026 — PMC13160648.
  7. LEF1 is associated with immunosuppressive microenvironment of patients with lung adenocarcinoma. Medicine 2024 — PMC11479531.
  8. Autoimmune Hemolytic Anemia Occurring One Year Before Acute Leukemic Manifestation of Lymphoma with a Chronic Lymphocytic Leukemia Immunophenotype. Internal medicine (Tokyo, Japan) 2026 — PMC13294606.
  9. PubMed PMID:2010090 — UniProt-cited evidence.
  10. PubMed PMID:10756202 — UniProt-cited evidence.
  11. PubMed PMID:19653274 — UniProt-cited evidence.