This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic MAPK6 IHC in paraffin sections using high-staining glandular cells or kidney tubules as positive controls (HPA tissue IHC). The catalog antibody PB9666 has an IHC dilution of 0.5–1 µg/mL; assess cytoplasmic staining against a negative control (datasheet PB9666; HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic tissue staining; nuclear location also annotated (HPA tissue IHC; UniProt) | |
| Staining pattern | General cytoplasmic staining; high in glandular cells (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet PB9666) | |
| Positive control | Breast+4 more · see all | |
| Negative control | Oral mucosa |
| Fixation | Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image PB9666) | |
| Caveat | Staining varies by cell type; oral squamous cells were undetected (HPA tissue IHC) | |
| Regulation | Expression regulation unreported (UniProt) | |
| Isoform / epitope | No reported isoforms or cleavage; no extracellular domain (UniProt) |
The catalog antibody protocol uses EDTA pH 8.0 retrieval (datasheet PB9666). The published MAPK6 IHC protocol uses heated citrate pH 6.0 (PMC8589317).
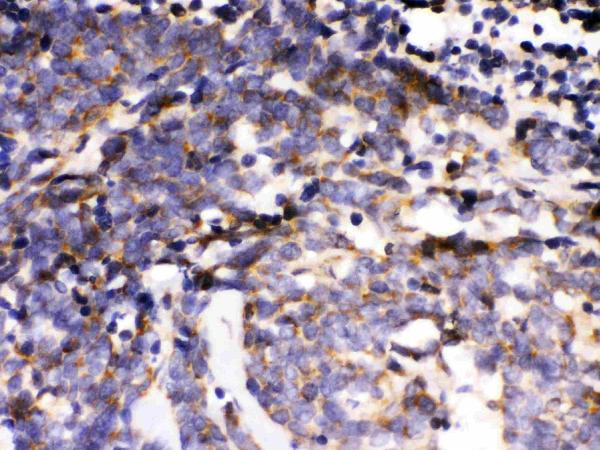
| Sample | Paraffin-embedded human lung cancer tissue; fixative not specified (datasheet PB9666) |
| Fixation | Image fixative and duration unreported (datasheet PB9666); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet PB9666); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet PB9666) |
| Primary antibody | Rabbit anti-MAPK6, 0.5-1μg/ml (datasheet PB9666) |
| Primary incubation | Overnight at 4 °C (datasheet PB9666) |
| Detection | Streptavidin-biotin complex (SABC), DAB chromogen (datasheet PB9666) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | MAPK6-positive staining in glandular cells of breast (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control. |
Expect mainly cytoplasmic MAPK6 staining in paraffin sections, including breast and duodenal glandular cells, kidney tubule cells, and pancreatic exocrine cells (HPA: general cytoplasmic expression; High in those cells). Nuclear MAPK6 is also possible, and the protein has no transmembrane segment (UniProt Q16659: subcellular location and topology). Treat the tissue pattern as a guide: HPA rates its IHC reliability Approved, with medium staining–RNA consistency and external verification pending (HPA: tissue IHC).
| Clear cytoplasmic chromogen in glandular or tubule cells, with visible cell boundaries and little staining outside cells. | This fits the reported general cytoplasmic pattern and High staining in breast, duodenum, endometrium, prostate, pancreas, and kidney cell populations (HPA: tissue IHC). Compare the exact cell population on the section; a positive tissue does not imply that every cell in it should stain (HPA: cell-specific tissue IHC). |
| Signal appears mainly in lumens or extracellular material, without convincing intracellular staining. | Check for a staining artefact: MAPK6 is reported in cytoplasm and nucleus and has no transmembrane segment (UniProt Q16659: location and topology). Do not reject every membrane-adjacent signal automatically; Purkinje cells are described as cytoplasm/membrane High in cerebellum (HPA: tissue IHC). |
| Strong staining appears in oral mucosa squamous cells while the expected positive cell populations are weak. | Investigate antibody cross-reactivity or endogenous chromogen-generating activity with appropriate controls (general IHC practice). HPA reports MAPK6 as Not detected in oral mucosa squamous cells, but its Approved IHC profile has medium consistency with RNA and awaits external verification (HPA: tissue IHC). |
| A diffuse brown haze covers several cell types, including spaces where cellular MAPK6 cannot be assessed. | This obscures the expected cytoplasmic distribution (HPA: general cytoplasmic expression). Assess a no-primary control for endogenous detection activity and review blocking, washing, and antibody concentration as general chromogenic IHC checks (general IHC practice); the haze alone cannot establish MAPK6 localisation. |
| No interpretable signal appears in kidney tubules or pancreatic exocrine cells on a test section. | HPA reports High staining in those populations, so a blank result warrants a technical check (HPA: tissue IHC). Verify section integrity, retrieval, antibody application, and detection with suitable controls (general IHC practice). A single negative section cannot establish absence of MAPK6, especially given the stated HPA verification limit (HPA: reliability description). |
| Choice of positive and lower-signal tissue | Breast glandular cells, kidney tubule cells, and pancreatic exocrine cells offer reported High IHC patterns; oral mucosa squamous cells are reported Not detected, while smooth muscle cells and adipocytes are Low (HPA: tissue IHC). Use those observations as comparison patterns, allowing for the stated medium staining–RNA consistency (HPA: reliability description). |
| Compartment and topology | A predominantly cytoplasmic result matches the HPA tissue profile; UniProt also lists the nucleus and reports cytoplasmic translocation following interaction with MAPKAPK5 (HPA: tissue IHC; UniProt Q16659: subcellular location). With no transmembrane segment, isolated extracellular staining needs scrutiny (UniProt Q16659: topology; general IHC practice). |
| Antibody validation limits | The three listed antibodies each have Approved IHC status, while the tissue profile has medium staining–RNA consistency and awaits external verification (HPA: antibody validation and tissue reliability). Approved status supports using the reported pattern for comparison; resolve an unexpected result with controls rather than treating that status as proof of specificity in every section (general IHC practice). |
| IF/ICC localisation cross-check: what should fluorescence show? | Mainly cytosolic signal, with additional microtubule and primary-cilium localisation, is the HPA ICC-IF pattern (HPA: subcellular localisation). That observation can help interpret compartment differences, but it comes from ICC-IF and does not establish how frequently these structures will be visible in chromogenic paraffin sections (HPA: ICC-IF; general IHC practice). |
| Target-specific processing and fixation evidence | UniProt lists a single MAPK6 chain spanning residues 1–721, with no signal peptide or propeptide and zero glycosylation sites (UniProt Q16659: processing and glycosylation). The supplied UniProt and HPA records give no target-specific fixation-sensitivity result; do not infer a MAPK6 fixation effect from these features. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected positive cells are blank. | Retrieval, antibody application, or detection may have failed (general IHC practice); kidney tubule and pancreatic exocrine cells are reported High (HPA: tissue IHC). | Run a suitable positive control and check the recorded retrieval and detection steps, then reassess staining specifically in the expected cells (general IHC practice; HPA: tissue IHC). |
| Brown stain persists without primary antibody. | Endogenous detection activity can produce chromogen independently of primary-antibody binding (general chromogenic IHC practice). | Review the no-primary control, endogenous-activity blocking, and detection chemistry before assigning the signal to MAPK6 (general IHC practice). |
| Most structures show a uniform brown haze. | Excess nonspecific reagent binding or incomplete washing can obscure the reported cytoplasmic pattern (general IHC practice; HPA: tissue IHC). | Inspect blocking and wash steps, and reassess antibody concentration against positive and no-primary controls (general IHC practice). |
| Staining is dominated by extracellular or luminal deposits. | The distribution conflicts with reported intracellular localisation and no transmembrane segment (UniProt Q16659: location and topology). | Inspect the section and controls for precipitate or nonspecific deposition; score cellular staining separately (general IHC practice). |
| Nuclear staining accompanies cytoplasmic staining. | UniProt lists both nucleus and cytoplasm and notes cytoplasmic translocation after MAPKAPK5 interaction (UniProt Q16659: subcellular location). | Record nuclear and cytoplasmic staining separately and compare them with morphology and controls; do not classify nuclear signal as artefact solely by compartment (UniProt Q16659: subcellular location; general IHC practice). |
| Unexpected cells stain strongly while reference cells do not. | Cross-reactivity or background is possible (general IHC practice); HPA's Approved profile has medium staining–RNA consistency (HPA: tissue reliability). | Check cell identity and controls, then compare the result with HPA's named High and Not detected populations before interpreting the unexpected staining (HPA: tissue IHC; general IHC practice). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Breast | Glandular cells | High | Protein (IHC) | HPA → |
| Cerebellum | Purkinje cells - cytoplasm/membrane | High | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | High | Protein (IHC) | HPA → |
| Endometrium | Glandular cells | High | Protein (IHC) | HPA → |
| Kidney | Cells in tubules | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Oral mucosa | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot MAPK6 staining in paraffin sections by checking retrieval, controls, cellular location, and scoring before interpreting chromogenic signal.
PB9666 has a real IHC image from a human paraffin section (PB9666 image caption). A03011S189-1 lists IHC and IF applications, with human, mouse and rat reactivity; no IF image is supplied (catalog applications; catalog reactivity; catalog image alts).
PB9666 has IHC data from a paraffin-embedded human lung cancer section and lists human, mouse and rat reactivity (PB9666 image caption; catalog reactivity). A03011S189-1 lists IHC and IF applications and human, mouse and rat reactivity, but supplies no IHC or IF image (catalog applications; catalog reactivity; catalog image alts).
Which to pick: Choose PB9666 for paraffin-section IHC because its own image documents chromogenic staining at 1 μg/ml; the fixative is unreported (PB9666 image caption). For IF, consider the polyclonal phospho-S189 antibody A03011S189-1 at its listed 1:50 dilution; ICC validation is unreported (A03011S189-1 dilution_raw; catalog applications). Both list human, mouse and rat reactivity for cross-species planning, while the supplied tissue image documents human staining only (catalog reactivity; PB9666 image caption).