This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan NIPBL IHC in paraffin sections around the nuclear staining seen in most tissues (HPA tissue IHC). This guide covers fixation, retrieval, controls and chromogenic scoring, with three isoforms to consider when assessing antibody specificity (UniProt).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Predominantly nuclear in tissue IHC (HPA tissue IHC) | |
| Staining pattern | Nuclear staining in glandular and trophoblastic cells (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A01939) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation conditions consistent across sections (standard IHC practice; not target-specific) | |
| Caveat | Antibody staining and RNA show medium consistency (HPA tissue IHC) | |
| Regulation | Expression regulation is unreported (UniProt) | |
| Isoform / epitope | Three isoforms; epitope coverage is unspecified (UniProt) |
The catalog antibody protocol uses heat-mediated Tris-EDTA pH 9.0 retrieval (datasheet: A01939). Published IHC protocols cover lung adenocarcinoma (PMC4438579) and testes (PMC3765518).
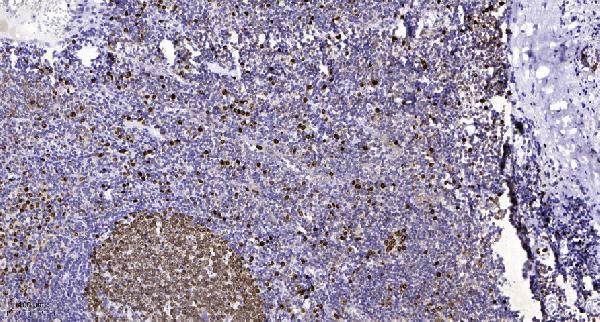
| Sample | Paraffin-embedded human tonsil tissue; fixative not specified (datasheet A01939) |
| Fixation | Image fixative and duration unreported (datasheet A01939); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Tris-EDTA pH 9.0 (datasheet A01939); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-NIPBL, 1:50 recommended; image 1:200 (datasheet A01939) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | NIPBL-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Nuclear expression in a majority of the tissues. No signal in the no-primary control. |
NIPBL should appear predominantly in nuclei across many tissues, consistent with its nuclear and chromosome localization and lack of a transmembrane segment (UniProt Q6KC79 topology; HPA: nuclear expression in a majority of tissues). Strong examples include adrenal and thyroid glandular cells, placental trophoblasts, and testicular pachytene spermatocytes (HPA tissue IHC: High). HPA rates the tissue profile Approved, with medium consistency between staining and RNA expression (HPA tissue IHC).
| Distinct nuclear staining in the expected cells, with little signal outside nuclei. | This matches the reported pattern (HPA tissue IHC: nuclear expression in a majority of tissues; UniProt Q6KC79: nucleus and chromosome). Compare intensity within the relevant cell population: HPA reports High staining in placental trophoblasts and Medium staining in skin fibroblasts (HPA tissue IHC). |
| Predominantly cytoplasmic or membrane-like staining in a paraffin section. | Treat this as a localization mismatch requiring validation, since the expected tissue pattern is nuclear (HPA tissue IHC). HPA reports uncertain cytosol and vesicle localization in ICC-IF; that observation alone does not establish a cytoplasmic IHC pattern (HPA subcellular ICC-IF). |
| Strong staining in a cell population reported as not detected. | Check identity and controls before interpreting it as NIPBL: HPA reports no detection in adipocytes, liver cholangiocytes, and splenic red-pulp cells (HPA tissue IHC). Cross-reactivity or endogenous detection activity can produce apparent signal (general IHC practice); an individual HPA observation is not an absolute exclusion rule. |
| Diffuse color across nuclei, cytoplasm, and tissue background. | The distribution does not resolve the predominantly nuclear pattern (HPA tissue IHC). Assess background with a negative detection control, then review blocking, wash stringency, and detection conditions (general chromogenic IHC practice). |
| No nuclear staining in a known-positive comparison section. | A failed positive comparison limits interpretation of the test section. Adrenal glandular cells or placental trophoblasts are High in the HPA tissue profile (HPA tissue IHC). Check section quality, retrieval, antibody conditions, and detection controls as general IHC workflow steps; no NIPBL-specific fixation effect is established here. |
| Cell-level reference | Use the named cell population, not the whole organ, for comparison (HPA tissue IHC). UniProt describes high liver expression, while HPA reports cholangiocytes as Not detected; those statements refer to different levels of observation (UniProt Q6KC79; HPA tissue IHC). |
| Subcellular location | A nuclear readout is supported by both sources (UniProt Q6KC79; HPA tissue IHC). NIPBL has no annotated transmembrane segment, so membrane staining has no support from its reported topology (UniProt Q6KC79 topology). |
| Antibody evidence | HPA040834 is Approved for IHC and Supported for ICC; HPA058239 has Supported ICC status with no IHC status supplied (HPA antibodies). Interpret IHC images using the IHC evidence for the chosen antibody, alongside HPA's medium consistency rating for the tissue profile (HPA tissue IHC). |
| Isoforms and processing | UniProt lists 3 isoforms and one annotated protein chain spanning residues 1–2804, without a signal peptide or propeptide (UniProt Q6KC79). The payload gives no antibody epitope, so isoform coverage cannot be inferred. |
| Retrieval and fixation | Target-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation. |
| Can IF/ICC clarify a compartment? | HPA supports nucleoplasm as the main ICC-IF location; vesicle and cytosol locations are uncertain (HPA subcellular ICC-IF). Use this as a localization comparison, without treating the uncertain locations as expected chromogenic IHC staining. |
| Situation | Likely cause | Next action |
|---|---|---|
| The positive comparison has no nuclear signal. | The staining run may have failed, or the comparison section may be unsuitable; HPA reports High staining in adrenal glandular cells and placental trophoblasts (HPA tissue IHC). | Check the positive section, retrieval conditions, antibody application, and detection reagents with run controls (general paraffin-IHC practice). Avoid calling the test section negative until the comparison works. |
| Color is mainly cytoplasmic or outlines membranes. | This conflicts with the reported nuclear tissue pattern (HPA tissue IHC; UniProt Q6KC79: nucleus and chromosome). HPA's uncertain cytosol and vesicle ICC-IF observations do not validate that IHC appearance (HPA subcellular ICC-IF). | Confirm compartment boundaries with the counterstain and review the negative detection control; reassess antibody specificity if the mismatch persists (general IHC practice). |
| The entire section has diffuse color. | Diffuse deposition can obscure the expected nuclear pattern (HPA tissue IHC); background from blocking, washes, or detection is a general chromogenic IHC possibility. | Compare a negative detection control and review blocking, wash stringency, and detection time (general IHC practice). Score nuclear staining only where cell boundaries and counterstained nuclei remain interpretable. |
| A reported not-detected cell type stains strongly. | Cross-reactivity or endogenous detection activity is possible (general IHC practice). HPA lists adipocytes and liver cholangiocytes as Not detected, but its tissue profile has medium consistency with RNA data (HPA tissue IHC). | Verify the cell type and compare negative detection and known-positive controls. Treat persistent staining as unresolved until specificity is supported; do not turn an HPA reference level into an absolute biological rule. |
| A section gives mixed signals across cell types. | Cell-specific levels can differ within and between tissues: HPA reports High placental trophoblasts, Medium skin fibroblasts, and Low skeletal myocytes (HPA tissue IHC). | Score the named cells and nuclear compartment separately, using the same staining run for comparisons (general IHC practice). Avoid assigning one expected intensity to every cell in a tissue. |
| An IF/ICC image shows extra cytosolic or vesicular signal. | HPA labels those additional locations uncertain, while nucleoplasm is supported (HPA subcellular ICC-IF). | Use the supported nucleoplasmic signal as the localization reference (HPA subcellular ICC-IF). Assess extra signal with appropriate imaging controls as general IF practice; do not use it to redefine the expected IHC pattern. |
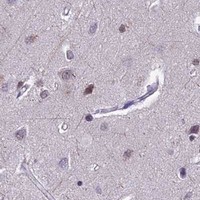


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Placenta | Trophoblastic cells | High | Protein (IHC) | HPA → |
| Skin | Fibroblasts | Medium | Protein (IHC) | HPA → |
| Stomach | Glandular cells | High | Protein (IHC) | HPA → |
| Testis | Pachytene spermatocytes | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Liver | Cholangiocytes | Not detected | Protein (IHC) | HPA → |
| Lymph node | Germinal center cells | Not detected | Protein (IHC) | HPA → |
| Parathyroid gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Prostate | Glandular cells | Not detected | Protein (IHC) | HPA → |
Use the IHC-validated antibody as a starting point for paraffin-section staining, then assess signal by cell type and nuclear localisation (datasheet A01939; HPA tissue IHC).
A01939 is listed for human and mouse IHC and IF (catalog: applications and reactivity); its supplied image shows IHC on a paraffin-embedded human tonsil section (A01939 IHC caption).
A01939 will render with an IHC image of a paraffin-embedded human tonsil section (A01939 IHC caption). IF is listed as an application, and human and mouse are listed as reactive species; no IF image is supplied (catalog: A01939 applications, reactivity and image captions).
Which to pick: Choose A01939 for paraffin-section tissue IHC because its own image documents that preparation in human tonsil (A01939 IHC caption); the fixative is unreported (A01939 IHC caption). For IF/ICC, A01939 is the only candidate, but IF is listed without a supplied IF image and ICC is not listed (catalog: A01939 applications and image captions). For mouse samples, A01939 lists mouse reactivity, although its supplied IHC image shows human tissue (catalog: A01939 reactivity; A01939 IHC caption).