This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan PACS1 chromogenic IHC on paraffin sections using the catalog antibody at a starting concentration of 2 μg/mL (datasheet). Compare cytoplasmic staining with the tissue profile (HPA tissue IHC); perinuclear trans-Golgi localisation is a molecular expectation (UniProt).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic tissue staining (HPA tissue IHC) | |
| Staining pattern | General cytoplasmic staining, abundant in lymphoid tissue (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Breast+4 more · see all | |
| Negative control | Liver |
| Fixation | Keep formalin fixation consistent across sections (standard IHC practice; not target-specific) | |
| Caveat | Antibody staining and RNA show medium consistency (HPA tissue IHC) | |
| Regulation | No specific expression regulator annotated (UniProt) | |
| Isoform / epitope | 2 isoforms; epitope coverage needs checking (UniProt) |
Compare the catalog antibody’s IHC-P protocol with the published PACS1 staining method for gastric tissue microarrays (PMC5906598).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A06811-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-PACS1, 2 μg/mL (datasheet A06811-1) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | PACS1-positive staining in glandular cells of breast (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression, highly abundant in lymphoid tissues. No signal in the no-primary control. |
PACS1 is associated with the trans-Golgi network and perinuclear region, with no transmembrane segment (UniProt Q6VY07). In paraffin-section IHC, expect cytoplasmic staining in several cell types, including breast glandular and neuronal cells; lymphoid tissues are described as highly abundant (HPA tissue IHC). The tissue staining profile is Approved, with medium consistency between staining and RNA data (HPA tissue IHC).
| Cytoplasmic staining in breast glandular cells or cerebral cortex neurons, possibly enriched near the nucleus. | These cells are reported High by tissue IHC (HPA tissue IHC). Perinuclear enrichment is compatible with the trans-Golgi network location, but is not required to call every positive cell (UniProt Q6VY07). |
| Strong nuclear-only staining, with little cytoplasmic staining, dominates a paraffin section. | This differs from the general cytoplasmic tissue IHC profile (HPA tissue IHC). Treat it as a possible artefact and check controls before scoring it as PACS1; HPA calls nucleoplasmic ICC-IF localization uncertain (HPA subcellular). |
| Liver cholangiocytes stain as strongly as the expected positive cells. | Cholangiocytes are listed as Not detected (HPA tissue IHC). Investigate antibody cross-reactivity or endogenous detection activity before accepting this signal; the tissue profile alone cannot identify which caused it. |
| Colour covers tissue structures indiscriminately, obscuring cell boundaries and cytoplasmic detail. | This cannot be scored against the reported cell-specific staining levels (HPA tissue IHC). Background or detection artefact is possible (general IHC practice); assess a primary-antibody omission control and tissue morphology. |
| No staining appears in an adequately preserved breast glandular-cell region. | Breast glandular cells are reported High (HPA tissue IHC), so a blank result warrants an assay check. One negative section cannot establish absent PACS1: the tissue profile has only medium staining–RNA consistency (HPA tissue IHC). |
| Tissue and cell choice | Use the named cell population when judging a section: breast glandular cells are High, whereas liver cholangiocytes are Not detected (HPA tissue IHC). A whole-tissue impression can hide that distinction. |
| IHC antibody evidence | HPA038914 is a rabbit polyclonal antibody with Approved IHC status (HPA antibodies). The supplied record does not label its IHC result Enhanced (HPA antibodies); interpret unusual staining with controls and morphology. |
| Protein form and location | UniProt lists two isoforms, no transmembrane segment, no signal peptide and no annotated glycosylation sites (UniProt Q6VY07). These annotations do not establish which isoform an antibody detects or predict a section's staining intensity. |
| Fixation and retrieval | Target-specific fixation sensitivity and retrieval response are unreported in the supplied UniProt and HPA records. Follow the validated IHC procedure and compare control sections (general IHC practice); do not infer a PACS1-specific fixation effect. |
| IF/ICC Q: Should its location match IHC? | A: HPA's ICC-IF main location is plasma membrane, with approved vesicular and uncertain nucleoplasmic localization (HPA subcellular). Tissue IHC is described as generally cytoplasmic (HPA tissue IHC); assess IF/ICC on its own guide page. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected positive cells remain blank. | An assay or detection failure is possible; breast glandular cells are reported High (HPA tissue IHC). A blank result does not by itself identify the failed step. | Check tissue preservation, the IHC antibody procedure, reagent activity and a known-positive control in the same run (general IHC practice). Do not assign a PACS1-specific fixation cause. |
| Signal is faint or varies across expected positive cells. | The tissue profile has medium staining–RNA consistency (HPA tissue IHC); variation alone does not establish antibody failure or a biological difference. | Compare the same named cell type across sections and runs, then score intensity only where morphology and control staining are interpretable (general IHC practice). |
| Nuclear-only staining dominates the slide. | The pattern differs from general cytoplasmic tissue staining (HPA tissue IHC). HPA marks nucleoplasmic ICC-IF localization uncertain (HPA subcellular). | Compare cytoplasmic signal in expected positive cells and examine a primary-antibody omission control before assigning PACS1 positivity (general IHC practice). |
| Cholangiocytes appear positive. | They are reported Not detected (HPA tissue IHC). Cross-reactivity or endogenous chromogenic detection activity could account for unexpected colour (general IHC practice). | Check a primary-antibody omission control and the detection system's endogenous-activity controls, then compare with an expected positive cell population (general IHC practice). |
| Diffuse colour obscures cell-specific staining. | Background from antibody concentration, incomplete washing or detection chemistry is possible (general IHC practice); the image cannot support reliable cell-level scoring. | Review omission controls, washing and antibody concentration within the validated IHC procedure; score only sections where cellular detail remains visible (general IHC practice). |
| Membrane-heavy staining raises doubt about the IHC result. | HPA reports approved plasma-membrane localization by ICC-IF, while describing tissue IHC as generally cytoplasmic (HPA subcellular; HPA tissue IHC). Assay context matters. | Compare membrane and cytoplasmic staining in the named positive cell type and inspect omission controls. Record the observed pattern without treating the ICC-IF image as a paraffin-IHC reference (general IHC practice; HPA tissue IHC). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Breast | Glandular cells | High | Protein (IHC) | HPA → |
| Caudate | Neuronal cells | High | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | High | Protein (IHC) | HPA → |
| Cerebral cortex | Neuronal cells | High | Protein (IHC) | HPA → |
| Endometrium | Glandular cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Liver | Cholangiocytes | Not detected | Protein (IHC) | HPA → |
Troubleshooting PACS1 staining in paraffin sections requires attention to retrieval, compartment pattern, tissue controls and consistent scoring.
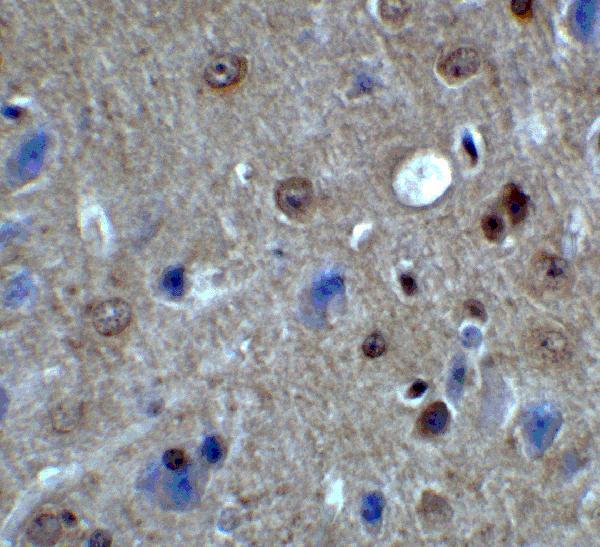
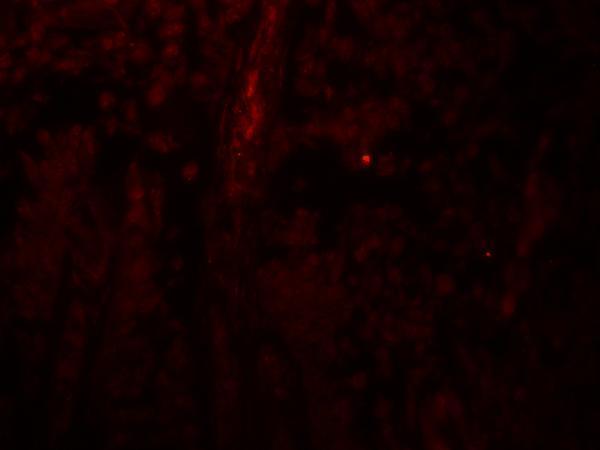
A06811-1 has IHC-P and IF applications (catalog: applications), with mouse brain IHC and mouse brain and human bladder IF images (catalog: image captions). Human, mouse and rat are listed as reactive (catalog: reactivity).
A06811-1 will render with an IHC image of mouse brain tissue stained at 2 μg/mL (catalog: IHC image caption). Its IF images show human bladder tissue and mouse brain tissue at 20 μg/mL (catalog: IF image captions).
Which to pick: Choose A06811-1 for tissue IHC-P: its application list includes IHC-P, and its own IHC caption shows mouse brain tissue at 2 μg/mL; the fixative is unreported (catalog: applications; IHC image caption). For IF, A06811-1 has human bladder and mouse brain tissue images; ICC is not listed as a tested application (catalog: IF image captions; applications). For work across species, A06811-1 lists human, mouse and rat reactivity, while its supplied IHC image documents mouse tissue only (catalog: reactivity; IHC image caption).