PLIN3 / Perilipin-3 · IHC design guide

Design Immunohistochemistry for PLIN3

Plan chromogenic IHC on paraffin sections using the IHC-validated antibody PB10013 (datasheet PB10013). Use cytoplasmic tissue staining as the reference pattern, while accounting for uncertain antibody–RNA agreement (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for PLIN3 (IHC for PLIN3): expected localisation Cytoplasmic staining in several tissues (HPA tissue IHC), antibody PB10013, validated IHC image, and IHC protocol steps
Printable PLIN3 IHC protocol sheet — expected localisation Cytoplasmic staining in several tissues (HPA tissue IHC), antibody PB10013, controls and protocol steps. Open the full PLIN3 IHC guide →

PLIN3 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in several tissues (HPA tissue IHC)
Staining pattern High cytoplasmic staining in adrenal glandular and skin Langerhans cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet PB10013)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Caudate+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific). Selected-image fixative and duration unreported (datasheet PB10013); verify before use.
Caveat Medium antibody–RNA consistency limits tissue predictions (HPA tissue IHC)
Regulation Expression regulation is not established (UniProt)
Isoform / epitope 4 isoforms; antibody epitope coverage is unspecified (UniProt; datasheet PB10013)
Section 1

Recommended PLIN3 IHC & IF Protocols

The catalog antibody has an IHC-P protocol (datasheet PB10013). The published PLIN3 IHC protocols below cover prostate cancer and lung adenocarcinoma tissue (PMC13464395; PMC8374126; PMC13188825).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colon cancer tissue; fixative not specified (datasheet PB10013)
FixationImage fixative and duration unreported (datasheet PB10013); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet PB10013); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet PB10013)
Primary antibodyRabbit anti-PLIN3, 2-5μg/ml (datasheet PB10013)
Primary incubationOvernight at 4 °C (datasheet PB10013)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet PB10013)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultPLIN3-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in several different tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA, pH 8.0, for the catalog antibody (datasheet PB10013). The published protocols used citrate, pH 6.0, or retrieval solution, pH 9.0 (PMC13464395; PMC8374126).
Section 2

What Is the Expected PLIN3 Staining Pattern?

Expect PLIN3 in the cytoplasm of several tissues, with lipid droplet association and possible endosome-associated signal (HPA: tissue profile; UniProt O60664: subcellular location). Adrenal glandular cells and skin Langerhans cells showed high staining; several other cell types showed medium staining (HPA: tissue IHC). PLIN3 has no transmembrane segment (UniProt O60664: topology). Tissue IHC reliability is uncertain because antibody staining and RNA expression have medium consistency (HPA: reliability).

What am I looking at on my slide?
Cell-confined cytoplasmic staining, sometimes appearing punctate or droplet-associated, in adrenal glandular cells or skin Langerhans cells.This fits the reported high-staining cells and PLIN3's lipid droplet location (HPA: tissue IHC; HPA: supported ICC-IF location). Chromogenic sections may not resolve individual droplets; assess compartment and cell identity together (general IHC practice).
Predominantly nuclear staining with little cytoplasmic signal in the expected positive cells.Treat this as a suspect compartment pattern: the supplied locations are cytoplasm, lipid droplets and endosome membrane (UniProt O60664: subcellular location; HPA: tissue profile). Check the counterstain and detection controls before interpreting it as PLIN3.
Strong signal mainly in a cell population reported as not detected, such as liver cholangiocytes.Consider cross-reactivity or endogenous detection activity, then compare with a known-positive tissue (HPA: cholangiocytes not detected; general IHC practice). An HPA negative is a comparison point, not proof that every specimen must be negative (HPA: IHC reliability uncertain).
Diffuse deposit over tissue and background areas, without clear cell boundaries.This is less persuasive than cell-confined cytoplasmic staining (HPA: tissue profile). Review reagent and no-primary controls for background or endogenous detection activity (general IHC practice); do not confuse broad tissue expression with uniform slide-wide deposit.
No signal in adrenal glandular cells or skin Langerhans cells.Investigate the staining run before calling the specimen negative: both populations showed high staining in HPA tissue IHC (HPA: adrenal glandular cells high; skin Langerhans cells high). HPA rates tissue IHC reliability uncertain, so verify with controls and replicate material (HPA: reliability).
💡Expected PLIN3 appearanceA convincing IHC positive is cell-confined cytoplasmic staining, potentially droplet-associated, strongest in HPA's high-staining adrenal glandular cells or skin Langerhans cells; predominant nuclear or slide-wide deposit is suspect (HPA: tissue IHC and supported ICC-IF location; UniProt O60664: subcellular location).
How each factor affects the staining
Cell and tissue choiceAdrenal glandular cells and skin Langerhans cells are high-staining examples; adipocytes and several glandular or epithelial populations are medium (HPA: tissue IHC). Compare like cell types when judging intensity rather than treating an entire section as uniformly positive.
Tissue IHC confidenceHPA calls tissue IHC uncertain because antibody staining and RNA expression show medium consistency; both listed antibodies have uncertain IHC status (HPA: reliability; HPA: HPA006427 and HPA066538). A single unexpected result needs control-based follow-up.
Compartment and topologyPLIN3 is reported at lipid droplets, in cytoplasm and associated with endosome membrane, with no transmembrane segment (UniProt O60664: subcellular location and topology). Judge cell-confined cytoplasmic staining against those locations; topology alone does not identify the antibody epitope.
Isoforms and processingFour isoforms are listed, and the annotated chain is residues 2–434 (UniProt O60664: isoforms and processing). The payload does not map antibody epitopes to isoforms, so these annotations cannot predict which isoform an IHC signal detects.
IF/ICC: where should signal appear?Mainly at lipid droplets: HPA marks that ICC-IF location supported and lists images from A-431, U-251MG, U2OS and PC-3 (HPA: subcellular). This localization evidence helps interpret compartment, but does not provide an IHC-P staining protocol.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in a high-staining reference cell population.The staining run or detection may have failed; an HPA reference is also uncertain for tissue IHC (HPA: adrenal glandular cells and Langerhans cells high; HPA: reliability).Confirm that the positive control and detection reagents worked, then review the antibody dilution and retrieval conditions in the validated IHC-P instructions (general IHC practice).
Predominantly nuclear signal.The compartment conflicts with the reported cytoplasmic and lipid droplet locations (HPA: tissue profile and supported ICC-IF location; UniProt O60664: subcellular location).Check counterstain overlap and no-primary controls; repeat with a validated staining run before assigning nuclear PLIN3 (general IHC practice).
Signal appears in an HPA not-detected cell type.Cross-reactivity or endogenous detection activity is possible; HPA reports no detection in liver cholangiocytes, for example (HPA: tissue IHC).Compare a high-staining reference cell type and inspect no-primary and detection controls; interpret disagreement cautiously because HPA tissue IHC reliability is uncertain (HPA: reliability; general IHC practice).
Heavy deposit obscures cell boundaries.Excess background or endogenous detection activity can prevent compartment assessment (general IHC practice).Check no-primary controls, blocking and detection development; optimize the validated antibody dilution if needed (general IHC practice). Reassess whether staining is cell-confined and cytoplasmic (HPA: tissue profile).
Only weak, widespread cytoplasmic staining is visible.PLIN3 has a broad cytoplasmic tissue profile, so weak cell-confined signal alone may be hard to distinguish from background (HPA: tissue profile).Compare the same run's high-staining reference cells with low or not-detected reference cells and controls; avoid a positive call based on intensity alone (HPA: tissue IHC; general IHC practice).
A cell type reported as not detected stains differently across specimens.The HPA result describes observed reference staining, and its tissue IHC reliability is uncertain (HPA: tissue IHC and reliability).Review cell identification, matched controls and repeat sections before treating the discrepancy as a biological difference or assay failure (general IHC practice).

Sample controls for PLIN3 IHC & IF

🧪Run adrenal gland first and require staining in its glandular cells (HPA: High in adrenal glandular cells). Use parathyroid glandular cells as the negative tissue (HPA: Not detected); on the adrenal slide, compare staining with morphologically distinct non-glandular cells, whose PLIN3 status is not established by the supplied HPA row.
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Caudate (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show PLIN3 in A-431, U-251MG, U2OS, PC-3, with annotated localisation: Lipid droplets (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, a matched rabbit immunoglobulin isotype control (PB10013 caption: rabbit primary antibody), and an identically processed PLIN3-knockout sample as a biological negative. For adrenal IHC, quench endogenous peroxidase and check tissue pigment before interpreting brown DAB signal (PB10013 caption: HRP/DAB; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected PB10013 paraffin-section caption does not state a fixative (PB10013 tissue-IHC caption). Heat-mediated EDTA retrieval at pH 8.0 was used, but retrieval dependency has not been established (PB10013 tissue-IHC caption). IF/ICC images support lipid-droplet localization, but the supplied evidence does not show that IF or frozen sections are easier than paraffin IHC; adrenal pigment may complicate DAB interpretation (HPA subcellular: lipid droplets; standard IHC practice).

HPA tissue IHC evidence for PLIN3

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Skin Langerhans High Protein (IHC) HPA →
Adipose tissue Adipocytes Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Caudate Glial cells Not detected Protein (IHC) HPA →
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Parathyroid gland Glandular cells Not detected Protein (IHC) HPA →
Seminal vesicle Glandular cells Not detected Protein (IHC) HPA →
Smooth muscle Smooth muscle cells Not detected Protein (IHC) HPA →
Section 3

Advanced PLIN3 IHC Tips

Troubleshoot PLIN3 staining in paraffin sections by checking retrieval, cellular localisation, controls and scoring before interpreting chromogenic signal.

What should I change if PLIN3 staining is weak after antigen retrieval?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 for paraffin sections stained with PB10013 (datasheet PB10013). The selected tissue image used this retrieval before incubation with 2 μg/ml primary antibody overnight at 4°C (caption PB10013). If staining remains weak, compare retrieval duration on adjacent sections while keeping antibody concentration, detection and development consistent (standard IHC practice). Include a section from the same block in each run so changes in staining can be assigned to retrieval rather than processing variation (standard IHC practice). Inspect tissue preservation and background alongside signal, because excessive heating can damage morphology and complicate interpretation (standard IHC practice).
Could fixation explain variable PLIN3 staining between paraffin blocks?
The PB10013 tissue caption identifies a paraffin section but does not state its fixative, so PLIN3 sensitivity to any particular fixation condition is unknown (caption PB10013). Record each block’s fixative, fixation duration and processing history before comparing its staining with another block (standard IHC practice). Run sections from the blocks together using EDTA at pH 8.0, the same 2 μg/ml primary concentration and matched detection conditions (datasheet PB10013; caption PB10013). Evaluate morphology and a control section alongside PLIN3, because tissue damage or inconsistent processing can confound staining comparisons (standard IHC practice). Treat any apparent fixation effect as a result to verify with matched material, rather than a known PLIN3-specific property.
Where should convincing PLIN3 signal appear in a paraffin section?
Assess PLIN3 primarily as cytoplasmic staining, with a punctate or droplet-associated pattern where morphology permits (HPA tissue IHC: cytoplasmic expression; HPA subcellular: lipid droplets supported). PLIN3 is associated with lipid droplets and endosome membranes and has no annotated transmembrane segment (UniProt O60664 localisation and topology). In paraffin sections, a diffuse cytoplasmic DAB signal may be easier to recognise than individual small droplets, so compare patterns across intact cells and matched controls (standard IHC practice). Do not score isolated nuclear staining as expected PLIN3 localisation without independent validation (UniProt O60664 localisation). Keep the cell type visible when assessing signal; HPA reports high staining in adrenal glandular cells and skin Langerhans cells (HPA tissue IHC).
Can PLIN3 isoforms or modifications alter what this antibody detects?
PLIN3 has 4 annotated isoforms, but the supplied PB10013 caption does not map its epitope or establish isoform coverage (UniProt O60664 isoforms; caption PB10013). The record also lists modified residues, including phosphoserines at positions 31, 91 and 130; their effect on this antibody’s staining is unreported (UniProt O60664 modified residues). Request an epitope map or validate staining with a second antibody directed to a distinct region before assigning an isoform-specific interpretation (standard IHC practice). Compare staining in matched sections processed with the same EDTA pH 8.0 retrieval and detection conditions (datasheet PB10013; standard IHC practice). A change in DAB intensity alone cannot establish which isoform or modification is present.
How should I investigate PLIN3 localisation by multiplex immunofluorescence?
Use the separate IF/ICC workflow to examine PLIN3 alongside a validated marker for the cell type under study; HPA reports high tissue staining in skin Langerhans cells and adrenal glandular cells (HPA tissue IHC). Choose fluorophores after checking tissue autofluorescence in an unstained section, and place the weaker channel away from the strongest autofluorescence (standard IF practice). Optimise gentle permeabilisation for access to cytoplasmic and droplet-associated PLIN3, which has no annotated transmembrane segment (UniProt O60664 localisation and topology; standard IF practice). Include single-label and no-primary controls to assess bleed-through and background (standard IF practice). HPA supports lipid-droplet localisation in its subcellular images; assess colocalisation at the level your imaging resolution permits (HPA subcellular).
How can I distinguish PLIN3 staining from chromogenic background?
Check a no-primary section and block endogenous peroxidase before HRP detection, particularly when DAB deposits appear in unexpected cells or tissue spaces (standard IHC practice). The selected PB10013 example used 10% goat serum blocking, a peroxidase-conjugated secondary and DAB development (caption PB10013). If diffuse staining persists, compare shorter DAB development and a primary-antibody titration against the documented 2 μg/ml condition on adjacent sections (caption PB10013; standard IHC practice). Examine section edges, folds and damaged areas separately, since uneven reagent exposure can create misleading deposits (standard IHC practice). Retain only signal that follows intact cellular morphology and exceeds the matched no-primary control (standard IHC practice).
What is a defensible way to quantify PLIN3 IHC staining? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and tissue compartment before scoring, then record both the percentage of positive cells and cytoplasmic staining intensity (standard IHC practice; HPA tissue IHC: cytoplasmic expression). An H-score can combine percentages at intensity grades 0–3 into a 0–300 scale, provided thresholds and image settings stay fixed (standard IHC practice). For spatial comparisons, report positive-cell density per mm² of viable tissue and normalise to the relevant cell population or viable area (standard IHC practice). Exclude folds, necrosis and edges using the same rules across sections (standard IHC practice). Report tissue and cell type because HPA staining varies by compartment, and its tissue-IHC reliability is uncertain (HPA tissue IHC).
When is PLIN3-positive DAB staining credible rather than artefactual?
Give greatest weight to reproducible cytoplasmic staining in intact cells, with droplet-associated detail where it is resolvable (HPA tissue IHC: cytoplasmic expression; HPA subcellular: lipid droplets supported). Check whether the stained cell population is plausible: HPA reports high signal in skin Langerhans cells and adrenal glandular cells, but no detected signal in liver cholangiocytes (HPA tissue IHC). Distrust signal confined to nuclei, cut edges or necrotic regions, and compare it with a no-primary control for endogenous enzyme or nonspecific DAB deposition (UniProt O60664 localisation; standard IHC practice). PLIN3 also associates with endosome membranes, so cytoplasmic patterns need not form perfect droplet rings (UniProt O60664 localisation). Interpret weak differences cautiously because HPA rates its tissue staining reliability as uncertain (HPA tissue IHC).
Boster reagents

Best PLIN3 / Perilipin-3 IHC Antibodies

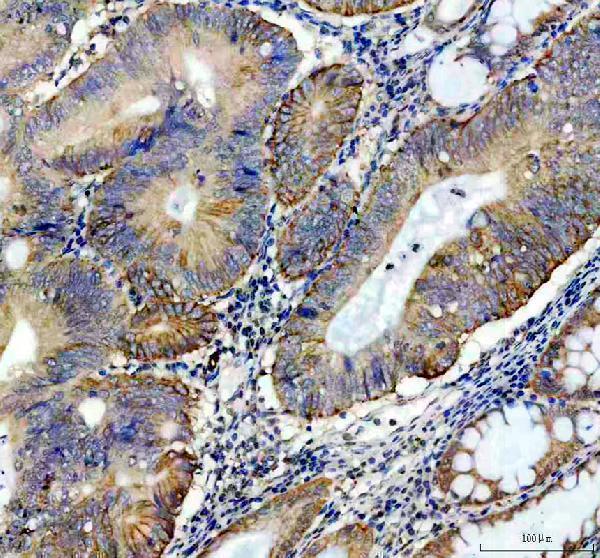
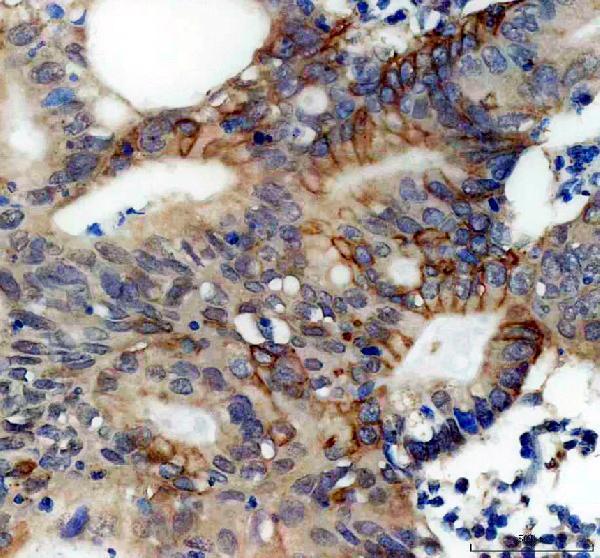
PB10013 has an IHC image from a human colon cancer paraffin section (PB10013 image caption); A02977-1 lists human IF/ICC applications without a supplied IF image (A02977-1 catalog payload).

Real IHC data IHC analysis of Perilipin 3/PLIN3 using anti-Perilipin 3/PLIN3 antibody (PB10013). Perilipin 3/PLIN3 was detected in a paraffin-embedded section of human colon cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-Perilipin 3/PLIN3 Antibody (PB10013) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-Perilipin 3/PLIN3 Antibody ®
Cat # PB10013

PB10013 will render with its human colon cancer paraffin-section IHC image; its listed reactivity is human, mouse and rat (PB10013 image caption; catalog applications and reactivity). A02977-1 lists human IF/ICC applications but has no supplied IF image and is not among the cards set to render (A02977-1 catalog payload; cards payload).

Which to pick: Choose PB10013 for paraffin-section tissue IHC: its own image shows staining of human colon cancer tissue after EDTA retrieval, and the fixative is unreported (PB10013 image caption). For IF/ICC, A02977-1 is the human-reactive, polyclonal option with those applications listed, though no IF image is supplied (A02977-1 catalog payload). PB10013 lists human, mouse and rat reactivity, but its supplied IHC image and IHC dilution cover human tissue only; validate mouse or rat IHC separately (PB10013 catalog reactivity and IHC dilution; PB10013 image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O60664 (PLIN3_HUMAN, Perilipin-3).
  2. Human Protein Atlas. PLIN3 tissue IHC expression (reliability: Uncertain).
  3. Human Protein Atlas. PLIN3 subcellular location (ICC-IF): Mainly localized to the lipid droplets..
  4. Human Protein Atlas. PLIN3 antibody validation summary (2 antibodies).
  5. Lipid Metabolic Rewiring During Continuous Prostate Cancer Progression Defines a Biologically Relevant Four-Gene Prognostic Signature. Biological procedures online 2026 — PMC13464395.
  6. Lipid droplet dynamics in healthy and pyometra-affected canine endometrium. BMC veterinary research 2022 — PMC9188128.
  7. Suppressed PLIN3 frequently occurs in prostate cancer, promoting docetaxel resistance via intensified autophagy, an event reversed by chloroquine. Medical oncology (Northwood, London, England) 2021 — PMC8374126.
  8. PLIN3 overexpression in lung adenocarcinoma promotes M2 macrophage-myofibroblast transition in the tumor microenvironment. Biology direct 2026 — PMC13188825.
  9. PubMed PMID:9590177 — UniProt-cited evidence.
  10. PubMed PMID:9874244 — UniProt-cited evidence.
  11. PubMed PMID:10393528 — UniProt-cited evidence.