This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan paraffin-section PPP1R3A IHC with heart or skeletal muscle as positive controls and cytoplasmic myocyte staining as the expected pattern (HPA tissue IHC). Start with the catalog antibody's 1:50 IHC dilution (datasheet A07755), and assess unexpected staining in light of presumed off-target binding (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining (HPA tissue IHC); membrane association (UniProt) | |
| Staining pattern | Cardiomyocyte and skeletal myocyte cytoplasm (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A07755) | |
| Positive control | Heart muscle+2 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific) | |
| Caveat | Presumed off-target staining was disregarded (HPA tissue IHC) | |
| Regulation | Muscle-enriched expression (UniProt) | |
| Isoform / epitope | 2 isoforms; TM at 1078–1098; epitope side unknown (UniProt) |
Compare the catalog antibody’s IHC-P protocol (datasheet A07755) with the published rat tendon IHC protocol (PMC10590817).
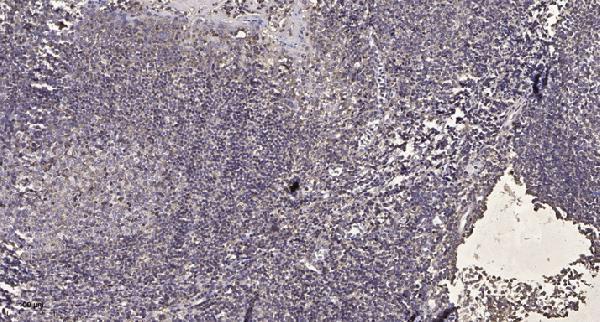
| Sample | Paraffin-embedded human tonsil tissue; fixative not specified (datasheet A07755) |
| Fixation | Image fixative and duration unreported (datasheet A07755); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Tris-EDTA pH 9.0 (datasheet A07755); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-PPP1R3A, 1:50 recommended; image 1:200 (datasheet A07755) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | PPP1R3A-positive staining in cardiomyocytes of heart muscle (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in skeletal and heart muscle. No signal in the no-primary control. |
PPP1R3A should show cytoplasmic staining in skeletal myocytes and cardiomyocytes, with membrane association consistent with its single transmembrane segment at residues 1078–1098 (HPA: tissue IHC profile; UniProt Q16821: topology). HPA rates both cell types High and the tissue IHC evidence Enhanced, while noting presumed off-target binding that was disregarded in its assessment (HPA: tissue IHC; HPA: reliability description).
| Strong cytoplasmic signal in skeletal myocytes or cardiomyocytes, with cellular outlines remaining interpretable. | This matches the principal observed pattern: both cell types are rated High, and the tissue profile describes cytoplasmic expression in skeletal and heart muscle (HPA: tissue IHC). Record the stained cell type and compartment when scoring; intensity alone cannot establish specificity, particularly because HPA notes presumed off-target binding (HPA: reliability description). |
| Predominantly nuclear staining in myocytes, with little cytoplasmic signal. | A nuclear-dominant pattern conflicts with the reported cytoplasmic muscle staining and membrane annotation (HPA: tissue IHC; UniProt Q16821: subcellular location). Treat it as suspect. Check whether the signal follows nuclei across the section, then review the negative control and repeat with the IHC-validated antibody if the pattern persists (general IHC practice). |
| Prominent staining in cells outside the expected muscle populations, especially cells in a negative-reference tissue. | Consider nonspecific antibody binding or endogenous chromogenic activity before assigning the signal to PPP1R3A (general IHC practice). HPA reports adipocytes in adipose tissue as Not detected, but also reports High staining in testicular spermatogonia; location outside muscle alone is therefore insufficient to declare every signal false (HPA: tissue IHC). |
| Broad, low-contrast color across many cell types or the section background. | A field-wide haze does not reproduce HPA’s cell-resolved cytoplasmic muscle pattern (HPA: tissue IHC). Common IHC causes include excess antibody or detection reagent, incomplete blocking, or inadequate washing (general IHC practice). Compare with the negative control before changing conditions, because a weak true signal can be obscured by background (general IHC practice). |
| No convincing signal in skeletal muscle or heart muscle. | A blank known-positive section is inconclusive: HPA rates skeletal myocytes and cardiomyocytes High, but its tissue observations do not guarantee performance under every staining condition (HPA: tissue IHC). Confirm tissue preservation and the detection controls, then review retrieval and antibody conditions using the catalog antibody’s IHC-P protocol (general IHC practice). |
| Tissue and cell selection | Skeletal myocytes and cardiomyocytes provide High-staining reference populations; adipocytes in adipose tissue provide a Not detected comparison (HPA: tissue IHC). HPA also lists spermatogonia as High, so interpret testis by cell type rather than assuming an entire nonmuscle tissue is negative (HPA: tissue IHC). |
| Compartment interpretation | HPA describes cytoplasmic staining in muscle, whereas UniProt annotates PPP1R3A as membrane-associated with one transmembrane segment at residues 1078–1098 (HPA: tissue IHC; UniProt Q16821: location and topology). These descriptions can coexist in light microscopy; the supplied sources do not define an organelle-level IHC pattern or prove that every visible edge signal is specific. |
| Antibody evidence | The tissue IHC assessment is Enhanced, and HPA lists HPA070440 and HPA073138 as IHC Enhanced (HPA: reliability; HPA: antibodies). HPA nevertheless notes presumed off-target binding that was disregarded, so compare cell type, compartment, and controls when judging a new section (HPA: reliability description; general IHC practice). |
| Isoforms and epitope scope | UniProt lists two isoforms and a single protein chain spanning residues 1–1122 (UniProt Q16821: isoforms and processing). The payload supplies no antibody epitope or isoform-specific staining data; do not attribute a changed IHC pattern to a particular isoform or processing event on this evidence alone. |
| Situation | Likely cause | Next action |
|---|---|---|
| The positive-reference muscle section is blank. | A failed stain or detection run may conceal an expected High signal in skeletal myocytes or cardiomyocytes (HPA: tissue IHC; general IHC practice). | Verify tissue and reagent controls, then check the catalog antibody’s IHC-P conditions, including its specified retrieval and dilution if available (general IHC practice). The supplied evidence gives no PPP1R3A-specific fixation sensitivity, so do not diagnose fixation as the cause from a blank section alone. |
| Myocyte nuclei are dark while cytoplasm is faint. | This distribution conflicts with the reported cytoplasmic muscle pattern (HPA: tissue IHC). Counterstain or nonspecific detection may complicate visual interpretation (general IHC practice). | Inspect a negative control and distinguish chromogen from counterstain, then reassess compartment calls at the cellular level (general IHC practice). If nuclear signal remains, record the result as discordant with HPA rather than scoring it as confirmed PPP1R3A. |
| Adipocytes stain as strongly as the muscle reference. | Adipocytes in adipose tissue are reported Not detected; comparable staining raises concern for nonspecific antibody binding or endogenous chromogenic activity (HPA: tissue IHC; general IHC practice). | Compare matched negative and detection controls, review blocking and washing, and require the expected myocyte cytoplasmic pattern before accepting the run (general IHC practice; HPA: tissue IHC). |
| The slide has diffuse color and poor cell boundaries. | Excess detection signal or insufficient blocking or washing can obscure cell-specific staining (general IHC practice). HPA’s reported muscle pattern is cytoplasmic and cell-associated (HPA: tissue IHC). | Check the negative control, then adjust staining conditions in a controlled rerun and judge whether myocyte cytoplasm separates clearly from background (general IHC practice; HPA: tissue IHC). |
| A testis section shows stained spermatogonia. | HPA reports spermatogonia as High, even though its summary emphasizes skeletal and heart muscle (HPA: tissue IHC). The observation is therefore not automatically an off-target result. | Identify the stained cell population before scoring and compare its pattern with appropriate controls (general IHC practice). Keep HPA’s off-target caveat in view; the reported High level alone does not validate a new antibody result (HPA: reliability description; HPA: tissue IHC). |
| Can this IHC pattern be used as an IF/ICC protocol or a precise IF localization call? | HPA’s subcellular summary says Membrane but provides no main location or cell-line ICC-IF images; its listed antibodies have no ICC status in the payload (HPA: subcellular; HPA: antibodies). | Use the muscle IHC observations as context only (HPA: tissue IHC). Follow the separate IF/ICC guide for method design and controls; do not infer an IF dilution, permeabilisation setting, or organelle-level pattern from this IHC record. |
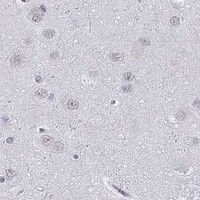
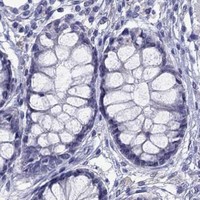
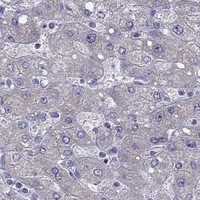
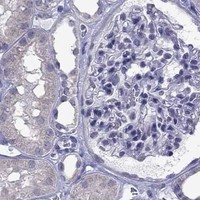
Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Presumed off target binding observed and disregarded.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Heart muscle | Cardiomyocytes | High | Protein (IHC) | HPA → |
| Skeletal muscle | Myocytes | High | Protein (IHC) | HPA → |
| Testis | Spermatogonia cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
Troubleshoot PPP1R3A staining in paraffin sections by checking retrieval, cell identity, subcellular pattern and controls before comparing signal intensity.
One IHC-validated anti-PPP1R3A antibody has a figure from paraffin-embedded human tonsil (A07755 image caption); its listed reactivity covers human, mouse, and rat (A07755 catalog). No IF data are supplied (catalog).
A07755 is the only card; it is listed for IHC and WB with human, mouse, and rat reactivity (A07755 catalog). Its IHC figure shows paraffin-embedded human tonsil, Tris-EDTA retrieval at pH 9.0, and a 1:200 primary dilution (A07755 image caption).
Which to pick: Choose A07755 for paraffin-section IHC based on its human tonsil figure; the caption does not report the fixative (A07755 image caption). No listed SKU supports an IF/ICC choice because A07755 has no IF application or figure (A07755 catalog). For mouse or rat tissue, A07755 is the listed cross-species candidate based on its polyclonal format and reactivity listing; its supplied IHC figure is human only (A07755 catalog; A07755 image caption).