SP2 / Transcription factor Sp2 · IHC design guide

Design Immunohistochemistry for SP2

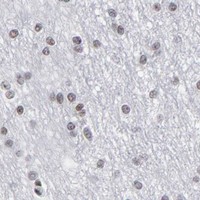
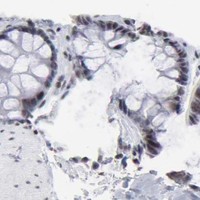
Plan SP2 chromogenic IHC around its general nuclear staining and high signal in testis preleptotene spermatocytes (HPA tissue IHC). Keep fixation consistent, include a negative control, and score nuclear signal while accounting for the medium consistency between antibody staining and RNA expression (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for SP2 (IHC for SP2): expected localisation General nuclear staining (HPA tissue IHC), antibody A02284, validated IHC image, and IHC protocol steps
Printable SP2 IHC protocol sheet — expected localisation General nuclear staining (HPA tissue IHC), antibody A02284, controls and protocol steps. Open the full SP2 IHC guide →

SP2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation General nuclear staining (HPA tissue IHC)
Staining pattern Nuclear signal across tissue cell types (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A02284)
Positive control ⓘ Testis+4 more · see all
Negative control ⓘ Adipose tissue
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Breast adipocytes stain; adipose adipocytes do not (HPA tissue IHC)
Regulation No expression regulator annotated (UniProt)
Isoform / epitope 2 isoforms; epitope coverage is unknown (UniProt)
Section 1

Recommended SP2 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet A02284) and a published hepatocellular tissue microarray protocol (PMC7221442: IHC methods) provide starting points for SP2 staining.

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human spleen tissue; fixative not specified (datasheet A02284)
FixationImage fixative and duration unreported (datasheet A02284); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Tris-EDTA pH 9.0 (datasheet A02284); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-SP2, 1:100 - 1:300 (datasheet A02284)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultSP2-positive staining in preleptotene spermatocytes of testis (HPA tissue IHC: High). HPA tissue profile: General nuclear expression. No signal in the no-primary control.
💡Decision noteTry heat-mediated Tris-EDTA retrieval at pH 9.0 first with the catalog antibody (datasheet A02284); the published protocol does not specify retrieval (PMC7221442: IHC methods).
Section 2

What Is the Expected SP2 Staining Pattern?

SP2 is a nuclear transcription factor with no transmembrane segment (UniProt Q02086: nucleus and topology). In paraffin sections, expect a general nuclear pattern, with the strongest reported staining in testis preleptotene spermatocytes and medium staining in several other listed cell populations (HPA: tissue IHC). HPA rates the tissue pattern Supported, with medium consistency against RNA data and external verification pending (HPA: reliability).

What am I looking at on my slide?
Distinct nuclear chromogen in testis preleptotene spermatocytes, stronger than nearby tissue (HPA: High in these cells).This matches the clearest reported positive population and SP2's nuclear location (HPA: tissue IHC; UniProt Q02086: nucleus). Compare nuclei within the same section, while allowing for the broader nuclear expression reported by HPA (HPA: general nuclear expression).
Predominantly cytoplasmic or membranous staining, with little nuclear signal (UniProt Q02086: nucleus and topology).That pattern conflicts with the expected nuclear IHC result (HPA: general nuclear expression). Check a no-primary control and the staining run before interpreting it as SP2; localization alone cannot identify the cause (general IHC practice).
Strong staining in a cell population reported only as Low, such as oral mucosa squamous epithelium (HPA: Low).Treat the intensity mismatch as a specificity question, especially if staining lies outside nuclei (HPA: tissue IHC; UniProt Q02086: nucleus). Cross-reactivity or endogenous detection activity is possible; matched controls can help distinguish them (general IHC practice).
Hazy chromogen across nuclei, cytoplasm and extracellular areas, with weak boundaries (general IHC practice).Diffuse deposition makes nuclear scoring unreliable (general IHC practice). Compare no-primary and known-positive sections, then review blocking, antibody concentration, washing and chromogen development before assigning cell-specific SP2 staining (general IHC practice).
No nuclear signal in testis preleptotene spermatocytes (HPA: High in these cells).A negative result in this reported positive population makes the run or antibody performance suspect (HPA: tissue IHC; general IHC practice). First check control performance and detection, then optimize retrieval or antibody dilution as general IHC variables; SP2-specific retrieval needs are unreported.
💡Expected SP2 appearanceCall an IHC section positive when clearly bounded nuclear staining appears in the relevant cells, especially the High testis preleptotene spermatocytes (UniProt Q02086: nucleus; HPA: tissue IHC); diffuse nonnuclear chromogen or staining persisting without primary antibody suggests an artefact (general IHC practice).
How each factor affects the staining
Expected compartment (UniProt Q02086: nucleus; HPA: general nuclear expression)Score nuclear staining as the principal IHC result (UniProt Q02086: nucleus; HPA: tissue IHC). SP2 has no annotated transmembrane segment, so a membrane-dominant pattern needs independent scrutiny (UniProt Q02086: topology; general IHC practice).
Tissue and cell context (HPA: tissue IHC)Testis preleptotene spermatocytes are High; listed adrenal glandular and bone-marrow hematopoietic cells are Medium (HPA: tissue IHC). Adipocytes are Medium in breast but Not detected in adipose tissue, so interpret them by tissue context (HPA: tissue IHC).
Strength of reference evidence (HPA: reliability and antibody validation)The tissue pattern is Supported, with medium RNA concordance and external verification pending (HPA: reliability). Both listed antibodies, HPA003357 and CAB010245, are IHC Supported; this does not make every observed stain definitive (HPA: antibody validation).
Detection chemistry and controls (general IHC practice)Endogenous detection activity or nonspecific chromogen deposition can mimic staining (general IHC practice). A no-primary control, appropriate blocking and a known-positive section help assess the run; none establishes SP2 identity alone (general IHC practice).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The reported positive testis population is blank (HPA: High in preleptotene spermatocytes).Possible weak assay sensitivity or failed detection (general IHC practice); SP2-specific retrieval sensitivity is unreported.Check the detection control and section identity, then optimize retrieval and primary dilution systematically (general IHC practice). Record changes alongside the positive control.
The whole section is brown, including spaces outside cells (general IHC practice).Background from detection chemistry, excess antibody or prolonged chromogen development is possible (general IHC practice).Inspect the no-primary control; review blocking, washing, antibody concentration and development time (general IHC practice). Score nuclei only after boundaries become clear.
Staining is mainly cytoplasmic or membranous (UniProt Q02086: nucleus and topology).The pattern conflicts with general nuclear expression (HPA: tissue IHC); off-target binding or detection background is possible (general IHC practice).Compare a known-positive section and no-primary control, then reassess specificity and subcellular scoring (general IHC practice).
Unexpected cell types stain strongly while the reported positive population is weak (HPA: tissue IHC).Cross-reactivity, endogenous activity or a poorly performing run may explain the reversal (general IHC practice).Compare the same cell types with HPA's tissue-specific levels, check no-primary staining, and repeat with an independently validated antibody if available (HPA: tissue IHC; general IHC practice).
A suspected negative section shows nuclear staining (HPA: general nuclear expression).SP2 has low RNA tissue specificity, and the reported negative is specifically adipocytes in adipose tissue (HPA: tissue IHC).Verify the tissue and cell identity before calling the result false; compare the relevant HPA cell-level entry and controls (HPA: tissue IHC; general IHC practice).
Does an IF/ICC vesicular signal validate vesicular IHC staining (HPA: subcellular ICC-IF)?HPA supports nucleoplasmic localization but marks additional vesicles uncertain in ICC-IF (HPA: subcellular ICC-IF).Use nuclear staining as the primary IHC interpretation (HPA: tissue IHC; UniProt Q02086: nucleus). Treat vesicular IF/ICC staining as uncertain and assess it with assay controls (HPA: subcellular ICC-IF; general IF practice).

Sample controls for SP2 IHC & IF

🧪Run testis first and score nuclear staining in preleptotene spermatocytes (HPA: High in preleptotene spermatocytes; UniProt Q02086: nucleus). Run adipose tissue as the negative tissue and score its adipocytes (HPA: Not detected in adipose tissue adipocytes); on the testis slide, neighboring cells without nuclear signal should remain at background, but they are not established biological negatives by these data.
Positive control tissue: Testis (Preleptotene spermatocytes, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show SP2 in A-431, U-251MG, U2OS, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; an isotype control matched to the primary antibody’s host species, isotype, and clonality; and a knockout specimen or validated peptide-block control (standard IHC practice). For chromogenic staining of testis, quench endogenous peroxidase and check background before scoring nuclei (standard IHC practice; HPA: High in testis preleptotene spermatocytes).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A02284 paraffin-section caption does not state the fixative (selected A02284 tissue-IHC caption). The caption uses Tris-EDTA pH 9.0 retrieval and a 1:200 primary antibody dilution, so retrieval is documented for that example; the supplied evidence does not establish whether frozen sections or IF/ICC are easier (selected A02284 tissue-IHC caption; HPA: ICC-IF images in A-431, U-251MG and U2OS). In densely populated testis, identify preleptotene spermatocytes before scoring nuclear signal to avoid assigning staining to another cell population (HPA: High in preleptotene spermatocytes; UniProt Q02086: nucleus).

HPA tissue IHC evidence for SP2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Testis Preleptotene spermatocytes High Protein (IHC) HPA →
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →
Breast Adipocytes Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced SP2 IHC Tips

Troubleshoot SP2 staining in paraffin-section chromogenic IHC, with one entry on IF validation.

Which retrieval conditions should I start with for SP2 in paraffin sections?
Start with heat-mediated retrieval in Tris-EDTA at pH 9.0 for paraffin sections (datasheet A02284). The selected spleen caption reports SP2 staining after that retrieval and an antibody dilution of 1:200, but does not state the fixative or heating duration (datasheet A02284). Keep heating and cooling conditions consistent between sections, and include a known staining control when comparing runs (standard IHC practice). If nuclear staining is weak, first check section processing and detection controls; then compare a shorter or longer retrieval within a controlled experiment (standard IHC practice). Score improvement by nuclear signal and preserved morphology, because SP2 is nuclear (UniProt Q02086).
How should I assess whether fixation is masking SP2 staining?
Target-specific SP2 sensitivity to fixation is unknown from the supplied evidence; the selected paraffin-section caption does not identify its fixative (datasheet A02284). Record the fixative and fixation interval for each specimen, and compare sections processed under matched conditions when investigating weak staining (standard IHC practice). Apply the documented Tris-EDTA pH 9.0 retrieval consistently before changing fixation-related variables (datasheet A02284). If a processing comparison is possible, assess nuclear signal alongside morphology and background rather than interpreting intensity alone (standard IHC practice; UniProt Q02086: nucleus). Do not infer fixation tolerance from tissue staining patterns, topology, or the annotated phosphoserine at residue 78 (HPA: tissue IHC; UniProt Q02086).
Where should convincing SP2 staining appear within positive cells?
Prioritise staining within nuclei: SP2 is annotated as nuclear, and the tissue IHC profile describes general nuclear expression (UniProt Q02086; HPA: tissue IHC). HPA subcellular imaging places SP2 mainly in the nucleoplasm, while its additional vesicle assignment is uncertain (HPA: subcellular). Use a nuclear counterstain to judge whether chromogen aligns with intact nuclei, particularly in crowded areas (standard IHC practice). A strong cytoplasmic-only pattern warrants review of background and antibody controls before being called SP2-positive (UniProt Q02086: nucleus; standard IHC practice). For a tissue comparison, HPA reports high staining in testis preleptotene spermatocytes, but its tissue IHC reliability is only Supported and awaits external verification (HPA: tissue IHC).
Could isoforms or epitope accessibility explain discrepant nuclear staining?
SP2 has 2 annotated isoforms, while the supplied product caption does not identify the antibody epitope or establish isoform coverage (UniProt Q02086; datasheet A02284). Check the antibody's documented immunogen or epitope before attributing different staining patterns to either isoform (standard IHC practice). UniProt annotates a phosphoserine at residue 78, but the payload does not show that this modification changes antibody binding (UniProt Q02086). Compare retrieval and staining on matched sections, retaining the documented Tris-EDTA pH 9.0 condition as the starting point (datasheet A02284; standard IHC practice). Report isoform-specific or modification-dependent staining only after testing an appropriate independent control, because nuclear appearance alone cannot distinguish those possibilities (standard IHC practice).
How can IF help check the cellular source of SP2 staining?
Use IF as a separate validation experiment and look for SP2 signal within nuclei, consistent with its nuclear annotation and supported nucleoplasmic localisation (UniProt Q02086; HPA: subcellular). For multiplexing in testis, pair SP2 with a validated marker of preleptotene spermatocytes, the cell population reported as high by tissue IHC (HPA: tissue IHC). Choose spectrally separated fluorophores and inspect unstained tissue for autofluorescence before assigning faint signal to SP2 (standard IF practice). Because SP2 has no annotated transmembrane segment and the expected signal is nuclear, optimise permeabilisation for access to an intracellular nuclear epitope (UniProt Q02086; standard IF practice). Validate the antibody and fixation conditions for IF independently; the A02284 paraffin-section caption supplies neither an IF protocol nor IF fixation evidence (datasheet A02284).
What should I check when SP2 chromogen appears diffuse or widespread?
First separate nuclear staining from diffuse chromogen, since SP2 is nuclear and HPA describes a general nuclear tissue profile (UniProt Q02086; HPA: tissue IHC). Review a section processed without primary antibody, the peroxidase block, wash steps, and chromogen development to identify detection-related background (standard chromogenic IHC practice). Use the caption's 1:200 primary dilution as a documented reference, then compare controlled staining conditions if excess signal persists (datasheet A02284; standard IHC practice). Examine tissue edges and damaged areas separately, where processing artefacts can exaggerate staining (standard IHC practice). Judge any adjustment by whether intact nuclei become easier to distinguish without losing the expected nuclear pattern (UniProt Q02086; standard IHC practice).
How should I quantify SP2 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Score SP2 in intact nuclei, using a prespecified percentage of positive cells or a nuclear H-score that combines the positive fraction with intensity (UniProt Q02086: nucleus; standard IHC practice). Define the cell population and intensity thresholds before reviewing experimental groups, and apply identical thresholds to all sections (standard IHC practice). Normalise positive nuclei to the total evaluable nuclei of that same cell population; if reporting positive-cell density per mm², divide by the measured viable tissue area (standard IHC practice). Exclude folds, necrosis, and section edges using the same criteria throughout (standard IHC practice). Report nuclear results separately from diffuse nonnuclear signal, which does not match the supported nucleoplasmic localisation (HPA: subcellular).
How do I distinguish true SP2 positivity from staining artefacts?
A credible positive has chromogen associated with intact nuclei, matching SP2's nuclear annotation and HPA's general nuclear tissue pattern (UniProt Q02086; HPA: tissue IHC). Check cell identity before comparing tissues: HPA reports high staining in testis preleptotene spermatocytes, but its tissue IHC assessment is Supported with external verification pending (HPA: tissue IHC). Treat isolated staining at section edges, in necrotic regions, or outside nuclei as suspect until controls and morphology support it (standard IHC practice; UniProt Q02086). A primary-omission control helps reveal endogenous enzyme activity or detection background in a chromogenic workflow (standard IHC practice). Interpret negative cells cautiously because HPA reports low tissue specificity at the RNA level (HPA: tissue IHC).
Boster reagents

Best SP2 / Transcription factor Sp2 IHC Antibodies

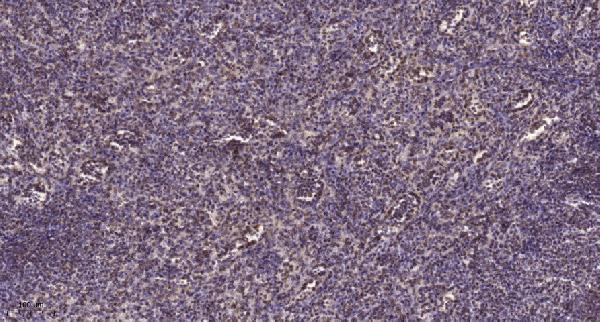
A02284 has an IHC image from paraffin-embedded human spleen (catalog IHC caption). IF/ICC and human/mouse reactivity are listed, but no IF image caption is supplied (catalog applications/reactivity/IF image alts).

Real IHC data Immunohistochemical analysis of paraffin-embedded human spleen. 1, Tris-EDTA,pH9.0 was used for antigen retrieval. 2 Antibody was diluted at 1:200(4° overnight.3,Secondary antibody was diluted at 1:200(room temperature, 45min).
Anti-Transcription factor Sp2 SP2 Antibody
Cat # A02284

A02284 will render with an IHC figure from paraffin-embedded human spleen (catalog IHC caption). It lists IHC, IF and ICC applications and human/mouse reactivity; the supplied figure documents human tissue IHC only (catalog applications/reactivity/IHC caption).

Which to pick: For tissue IHC, choose A02284 for paraffin-embedded human spleen: its figure caption reports Tris-EDTA pH 9 retrieval and a 1:200 primary dilution overnight at 4°C; the fixative is unreported (catalog IHC caption). For IF/ICC, A02284 lists both applications and an IF dilution of 1:50, but has no supplied IF image caption (catalog applications/IF dilution/IF image alts). For cross-species work, A02284 lists human and mouse reactivity and is rabbit polyclonal; its shown IHC result is from human spleen (catalog reactivity/host/dilution raw/IHC caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q02086 (SP2_HUMAN, Transcription factor Sp2).
  2. Human Protein Atlas. SP2 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. SP2 subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to vesicles..
  4. Human Protein Atlas. SP2 antibody validation summary (2 antibodies).
  5. ERGIC3, which is regulated by miR-203a, is a potential biomarker for non-small cell lung cancer. Cancer science 2015 — PMC4638005.
  6. Predictors of Recurrent Ductal Carcinoma In Situ after Breast-Conserving Surgery. Journal of breast cancer 2016 — PMC4929260.
  7. Prognostic Significance of a Micropapillary Pattern in Pure Mucinous Carcinoma of the Breast: Comparative Analysis with Micropapillary Carcinoma. Journal of pathology and translational medicine 2017 — PMC5525037.
  8. Sp2 promotes invasion and metastasis of hepatocellular carcinoma by targeting TRIB3 protein. Cancer medicine 2020 — PMC7221442.
  9. PubMed PMID:7584044 — UniProt-cited evidence.
  10. PubMed PMID:16625196 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.