This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan SUZ12 IHC-P around its nuclear, chromatin-associated location (UniProt) and the low nuclear staining reported in several tissues (HPA tissue IHC). Use tissue controls and interpret staining intensity cautiously because antibody staining and RNA expression show low consistency (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclear staining in several tissues (HPA tissue IHC) | |
| Staining pattern | Low nuclear staining in several tissues (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen) | |
| Positive control | Fallopian tube+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image M00583-3) | |
| Caveat | Tissue staining has low consistency with RNA levels (HPA tissue IHC) | |
| Regulation | Overexpressed in breast and colon cancer (UniProt) | |
| Isoform / epitope | No isoforms annotated; one 1–739 chain (UniProt) |
The catalog antibody’s IHC-P protocol is accompanied by three published SUZ12 IHC protocols (PMC5307854; PMC6010759; PMC4383254).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet M00583-3); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-SUZ12, 1:200-1:1000 (datasheet M00583-3) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | SUZ12-positive staining in ciliated cells (tip of cilia) of fallopian tube (HPA tissue IHC: High). HPA tissue profile: Low nuclear expression in several tissues. No signal in the no-primary control. |
SUZ12 is a nuclear, chromatin-associated PRC2 protein with no transmembrane segment (UniProt Q15022). In paraffin-section IHC, expect mainly nuclear staining in selected cells, including tonsil germinal center cells, bone marrow hematopoietic cells, and kidney tubular cells (HPA tissue IHC: Medium). HPA describes low nuclear expression across several tissues, but rates its IHC evidence Approved with low consistency between staining and RNA expression (HPA tissue IHC).
| Nuclear staining appears in tonsil germinal center cells, bone marrow hematopoietic cells, or kidney tubular cells (HPA tissue IHC: Medium). | This fits the expected compartment and reported cell distribution (UniProt Q15022; HPA tissue IHC). Compare staining with nearby morphology and the chosen control section; HPA's Approved rating carries a low staining–RNA consistency caveat (HPA tissue IHC). |
| Signal is predominantly cytoplasmic, membranous, or extracellular, with little nuclear staining. | That distribution conflicts with chromatin-associated nuclear SUZ12 (UniProt Q15022). Treat it as suspect and review morphology, background, and antibody-specific controls before scoring it as target signal (general IHC practice). |
| Strong staining appears in adipocytes or other cells listed as not detected by HPA. | HPA reports adipocytes as not detected in adipose tissue and breast (HPA tissue IHC). Unexpected staining can reflect cross-reactivity or endogenous detection activity; check a no-primary control and do not treat one discordant field as proof of expression (general IHC practice). |
| Color spreads uniformly across nuclei, cytoplasm, and empty spaces. | A diffuse deposit lacks the expected nuclear restriction (UniProt Q15022). Consider nonspecific background or detection-system activity; inspect a no-primary control, reagent blanks, and tissue edges before interpreting weak nuclear color (general IHC practice). |
| No convincing nuclear signal appears in a section selected from an HPA Medium-staining cell population. | A negative result there warrants checking control performance, tissue preservation, and the detection workflow (general IHC practice). HPA reports Medium staining, not guaranteed positivity in every specimen, and notes low staining–RNA consistency (HPA tissue IHC). |
| Nuclear location and chromatin association (UniProt Q15022) | Evaluate stain within morphologically identifiable nuclei. SUZ12 is a PRC2 component localized to chromatin, so a cytoplasmic or surface-dominant pattern does not match its annotated location (UniProt Q15022). |
| Cell distribution and evidence strength (HPA tissue IHC) | HPA reports Medium staining in several cell populations, low nuclear expression across several tissues, and low staining–RNA consistency despite an Approved IHC rating. Use those observations as comparison points, not absolute specimen-level pass criteria (HPA tissue IHC). |
| Fallopian-tube ciliary-tip report (HPA tissue IHC) | HPA lists High staining at ciliated-cell ciliary tips, a site that conflicts with UniProt's nuclear chromatin localization (HPA tissue IHC; UniProt Q15022). Record that observation separately; it does not establish ciliary SUZ12 or replace nuclear staining as the expected pattern. |
| IF/ICC: where should SUZ12 appear? (HPA subcellular ICC-IF) | HPA supports nucleoplasm, nucleoli, and nuclear bodies, with additional nucleolar-rim localization (HPA subcellular ICC-IF). This answers the IF/ICC localization question; the IF/ICC workflow belongs in its own guide (HPA subcellular ICC-IF). |
| Situation | Likely cause | Next action |
|---|---|---|
| The intended positive section is blank. | The assay may have failed, or the sampled cells may differ from HPA's reported Medium-staining populations (HPA tissue IHC; general IHC practice). | Confirm the relevant cells are present, inspect counterstain and detection controls, then review the antibody datasheet's IHC-P conditions and the run record (general IHC practice). Do not infer a SUZ12-specific fixation effect from these data. |
| Nuclei are faint but the whole section is pale. | Weak overall detection can obscure HPA's low nuclear expression pattern (HPA tissue IHC; general IHC practice). | Compare a known reactive section processed in the same run; check reagent performance and antibody dilution against its documented IHC-P instructions (general IHC practice). No target-specific dilution is supplied here. |
| Cytoplasm or membranes stain more strongly than nuclei. | The dominant compartment disagrees with nuclear, chromatin-associated SUZ12 (UniProt Q15022). Nonspecific binding or detection background is possible (general IHC practice). | Review a no-primary control and tissue morphology, then optimize blocking or detection conditions as needed (general IHC practice). Score nuclear signal separately from the discordant deposit. |
| Adipocytes or another HPA not-detected population stain strongly. | This conflicts with the cited HPA cell-level observation; cross-reactivity or endogenous detection activity may contribute (HPA tissue IHC; general IHC practice). | Verify cell identity, check a no-primary control, and assess endogenous activity appropriate to the chromogenic detection system (general IHC practice). Report the discrepancy rather than reclassifying that cell type as an established positive. |
| Background is diffuse or collects at section edges. | A broad deposit is difficult to reconcile with nuclear SUZ12 and may arise from nonspecific staining or uneven reagent coverage (UniProt Q15022; general IHC practice). | Inspect the no-primary control; review washing, blocking, reagent coverage, and detection development for the affected run (general IHC practice). Interpret nuclei only where tissue detail remains clear. |
| Prominent ciliary-tip staining appears in fallopian tube. | HPA reports High ciliary-tip staining, while UniProt places SUZ12 in the nucleus on chromatin; HPA also reports low staining–RNA consistency (HPA tissue IHC; UniProt Q15022). | Document ciliary and nuclear staining separately, inspect controls, and avoid calling ciliary signal confirmed SUZ12 localization on this evidence alone (HPA tissue IHC; UniProt Q15022; general IHC practice). |
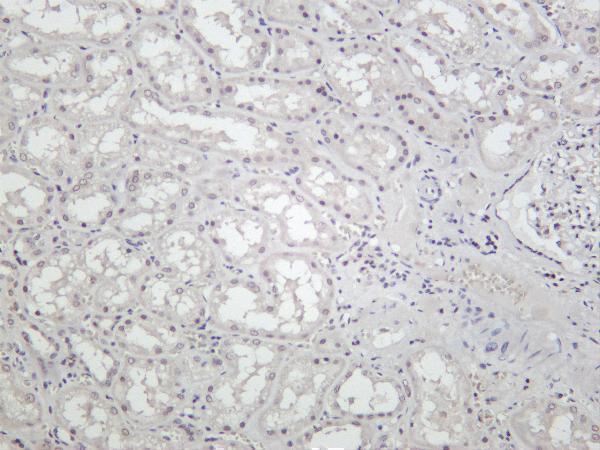
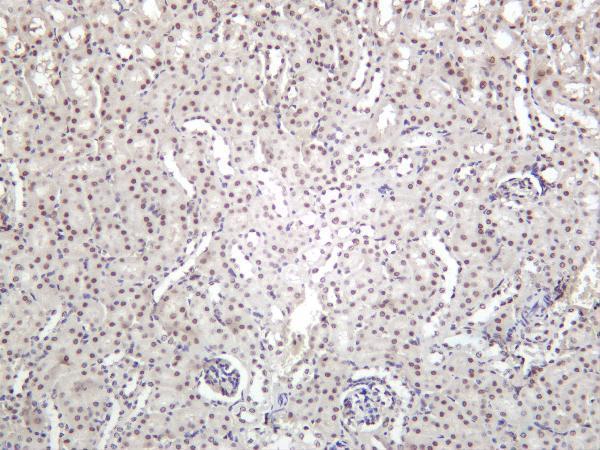
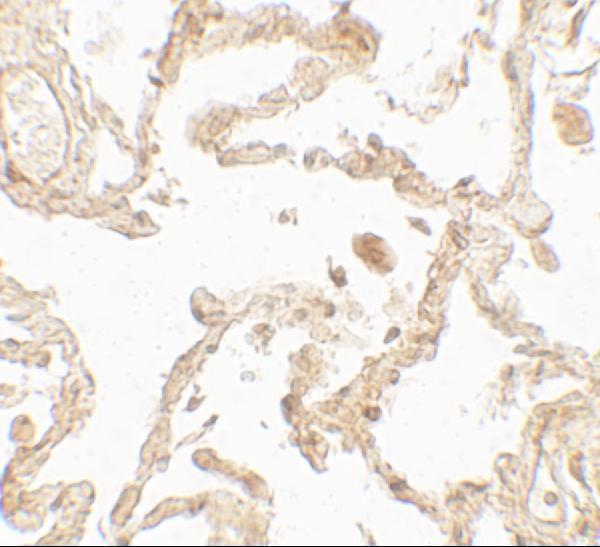
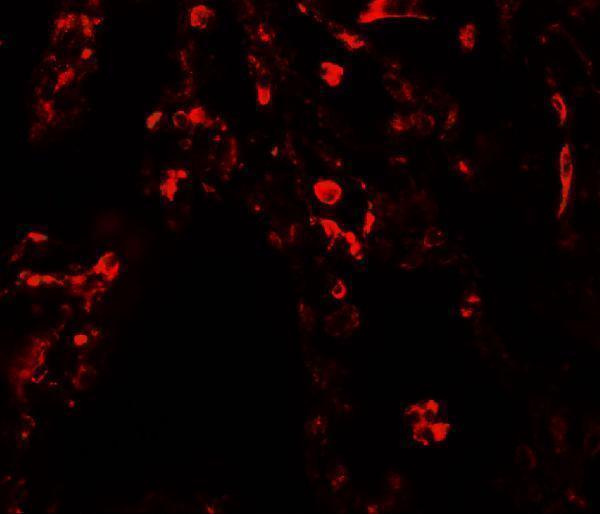


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Fallopian tube | Ciliated cells (tip of cilia) | High | Protein (IHC) | HPA → |
| Appendix | Lymphoid tissue | Medium | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Medium | Protein (IHC) | HPA → |
| Gallbladder | Glandular cells | Medium | Protein (IHC) | HPA → |
| Kidney | Cells in tubules | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Caudate | Glial cells | Not detected | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | Not detected | Protein (IHC) | HPA → |
SUZ12 is a chromatin-associated nuclear PRC2 component (UniProt Q15022). Use compartment-aware controls when troubleshooting chromogenic staining in paraffin sections.
Anti-SUZ12 antibodies have IHC images from human lung and human, mouse, and rat kidney, plus IF images from human lung and U2OS cells (catalog image captions).
M00583-3 lists IHC and IF applications and has IHC images from human, mouse, and rat kidney (catalog applications and IHC image captions). A00583 lists IHC-P and IF applications, with images from human lung at 5 μg/mL for IHC and 20 μg/mL for IF (catalog applications and image captions).
Which to pick: For paraffin-section tissue IHC, choose A00583: it lists IHC-P and shows staining in human lung at 5 μg/mL; the image caption does not report a fixative (catalog applications and IHC image caption). For human-cell IF/ICC, consider A00583-1, which lists IF and ICC and has an IF image from U2OS cells (catalog applications and IF image caption). For IHC across human, mouse, and rat samples, choose rabbit monoclonal M00583-3, which lists all three species and has a kidney IHC image for each (catalog description, reactivity, and IHC image captions).