This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
WSB1 shows cytoplasmic tissue staining, including at luminal membranes (HPA tissue IHC). This guide uses colon glandular cells and kidney tubules as positive controls (HPA tissue IHC) and 5 μg/mL catalog antibody as a starting concentration (datasheet).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic, including luminal membrane (HPA tissue IHC) | |
| Staining pattern | Glandular and tubular cells: cytoplasmic, luminal staining (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Appendix+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep paraffin-section fixation consistent (standard IHC practice; not target-specific) | |
| Caveat | Antibody staining has low concordance with RNA expression (HPA tissue IHC) | |
| Regulation | Expression regulation not annotated (UniProt) | |
| Isoform / epitope | 4 isoforms; epitope coverage is unknown (UniProt; datasheet) |
Compare the catalog antibody’s IHC-P protocol with published WSB1 IHC methods for human cancer tissue arrays (PMC4647558) and myocardial paraffin sections (PMC10893653).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A07445); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-WSB1, 5 μg/mL (datasheet A07445) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | WSB1-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in several tissues, including luminal membrane. No signal in the no-primary control. |
In paraffin-section IHC, expect mainly cytoplasmic WSB1 staining, sometimes along the luminal membrane, especially in appendix, colon, gallbladder and prostate glandular cells and kidney tubule cells (HPA: tissue IHC). WSB1 has no transmembrane segment (UniProt Q9Y6I7 topology). The HPA IHC antibody is Approved, but staining has low consistency with RNA expression; treat the pattern as a guide to interpretation, not proof of specificity (HPA: reliability).
| Distinct cytoplasmic staining in glandular cells or kidney tubules, with possible luminal-edge staining. | This matches the reported IHC distribution. Appendix, colon, gallbladder and prostate glandular cells and kidney tubule cells are listed as High; assess the relevant cells rather than assigning one score to the whole section (HPA: tissue IHC). Because HPA reports low consistency between staining and RNA expression, a matching image alone does not establish antibody specificity (HPA: reliability). |
| A predominantly nuclear or other compartment-restricted IHC pattern replaces the expected cytoplasmic pattern. | Flag the result for review: HPA describes tissue IHC as cytoplasmic, including luminal membrane staining (HPA: tissue IHC). Check morphology, counterstain and detection controls before calling it WSB1. HPA separately reports mitochondrial localisation by ICC-IF, so assess IF images against that application-specific observation (HPA: subcellular ICC-IF). |
| Strong staining appears mainly in cells listed as undetected, while the expected cells remain faint. | For example, adipocytes in adipose tissue and alveolar cells in lung are listed as Not detected (HPA: tissue IHC). This mismatch raises possible cross-reactivity or endogenous detection activity; compare a known-positive section and a no-primary control before interpreting the unexpected signal (general IHC practice). |
| Weak colour spreads across many cell types and tissue spaces without a clear cellular boundary. | A broad haze cannot be scored as the HPA cytoplasmic pattern (HPA: tissue IHC). In chromogenic IHC, background may arise from nonspecific antibody binding or endogenous detection activity (general IHC practice). Compare tissue morphology and a no-primary control, then score only discernible cellular staining (general IHC practice). |
| No cellular signal is visible in a section selected for reported high WSB1 staining. | If the relevant glandular or tubule cells are present, this conflicts with the HPA High observations for appendix, colon, gallbladder, kidney and prostate (HPA: tissue IHC). Check that the staining run and positive control worked before reporting absence; HPA's Approved rating and low RNA consistency limit the certainty of any single section (HPA: reliability). |
| IHC evidence and scoring | The single listed antibody, HPA003293, is IHC Approved; the tissue profile reports low consistency between antibody staining and RNA expression (HPA: antibody validation; HPA: reliability). Use the HPA pattern as a comparison, and interpret intensity in the named cell population (HPA: tissue IHC). |
| Topology and processing | UniProt lists no transmembrane segment, signal peptide, propeptide or glycosylation sites for WSB1 (UniProt Q9Y6I7 topology and processing). The HPA luminal-membrane IHC observation is a staining pattern; it does not establish a membrane-spanning or shed form (HPA: tissue IHC; UniProt Q9Y6I7 topology). |
| Isoforms | UniProt lists 4 isoforms (UniProt Q9Y6I7 isoforms). The supplied evidence does not identify the antibody epitope or establish isoform-specific IHC staining; avoid assigning an IHC pattern to an individual isoform. |
| IF/ICC Q: What location should an IF image be checked against? | A: HPA reports approved mitochondrial localisation in ICC-IF, with images from A-431 and U2OS (HPA: subcellular ICC-IF). This is application-specific evidence; compare the IF image with that localisation while keeping the cytoplasmic tissue-IHC profile as the IHC reference (HPA: tissue IHC). |
| Situation | Likely cause | Next action |
|---|---|---|
| A high-staining reference section shows no signal. | The run may have failed, or the relevant cells may be absent from the examined field (general IHC practice). HPA reports High staining in specified glandular cells and kidney tubules, not every cell in those organs (HPA: tissue IHC). | Confirm the listed cell population on the counterstained section. Review the run control, antibody dilution, antigen-retrieval conditions and chromogen development using the validated IHC procedure (general IHC practice); do not infer WSB1 absence from a failed run. |
| A strong nuclear-only pattern appears. | Its dominant compartment disagrees with the cytoplasmic tissue-IHC profile (HPA: tissue IHC); the supplied evidence does not identify a target-specific cause. | Check tissue morphology and counterstain, compare a reported-positive cell population, and examine a no-primary control for detection signal (general IHC practice). Report the discrepancy if it persists. |
| Listed undetected cell types stain strongly. | Cross-reactivity or endogenous detection activity is possible (general IHC practice). HPA lists adipocytes in adipose tissue and lung alveolar cells as Not detected (HPA: tissue IHC). | Compare a no-primary control and a reported-positive section in the same run (general IHC practice). Interpret the named cell types separately and avoid calling unexpected staining specific on morphology alone. |
| Diffuse chromogenic background obscures cell boundaries. | Nonspecific binding or endogenous detection activity can obscure cellular staining (general IHC practice); this appearance does not resolve the HPA cytoplasmic pattern (HPA: tissue IHC). | Review blocking, washing, antibody dilution and detection controls using standard IHC practice. Score only signal that remains clearly assigned to intact cells (general IHC practice). |
| Luminal-edge staining is mistaken for proof of a membrane-spanning protein. | HPA includes luminal-membrane staining in its IHC profile, while UniProt lists no transmembrane segment (HPA: tissue IHC; UniProt Q9Y6I7 topology). | Describe the visible edge and cytoplasmic distribution without assigning membrane topology. Compare adjacent cells and the reported glandular pattern before scoring (HPA: tissue IHC). |
| IHC and ICC-IF images seem to show different compartments. | HPA reports cytoplasmic tissue IHC, including luminal membrane, and approved mitochondrial ICC-IF localisation (HPA: tissue IHC; HPA: subcellular ICC-IF). | Evaluate each image against its own HPA application record. Record the method and observed compartment; do not use the ICC-IF result alone to reject an otherwise matching IHC section. |
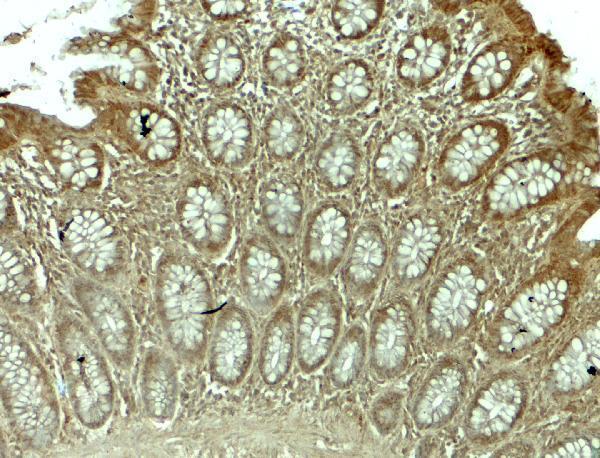
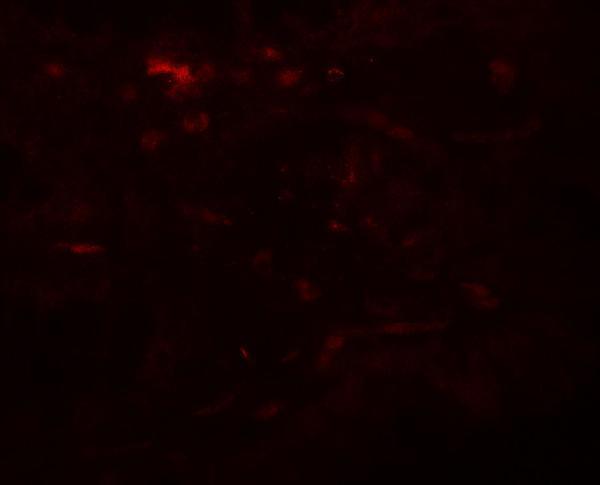


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Colon | Glandular cells | High | Protein (IHC) | HPA → |
| Gallbladder | Glandular cells | High | Protein (IHC) | HPA → |
| Kidney | Cells in tubules | High | Protein (IHC) | HPA → |
| Prostate | Glandular cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Not detected | Protein (IHC) | HPA → |
| Endometrium | Cells in endometrial stroma | Not detected | Protein (IHC) | HPA → |
Troubleshoot WSB1 staining in paraffin section IHC by checking retrieval, controls, cellular pattern and scoring before interpreting signal.
The catalog antibody has IHC-P and IF applications in human samples (catalog: IHC-P; IF; Human), with images from human colon tissue (IHC and IF image captions: human colon tissue).
A07445 is listed for human IHC-P, with an IHC image of human colon tissue (catalog: Human; IHC-P; IHC image caption: human colon tissue). The same SKU is listed for IF, with an IF image of human colon tissue (catalog: IF; IF image caption: human colon tissue).
Which to pick: For tissue IHC, choose A07445: it is listed for paraffin sections (catalog: IHC-P), and its own IHC image shows human colon tissue at 5 μg/mL (IHC image caption: human colon tissue; 5 μg/mL); the fixative is unreported (IHC image caption). For IF, A07445 has a human colon tissue image at 20 μg/mL (IF image caption: human colon tissue; 20 μg/mL), while ICC validation is unreported (catalog: application list). No cross-species choice is supported: A07445 lists Human reactivity and a Rabbit host, with clonality unreported.