This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic WWC1 IHC-P using the catalog antibody's starting concentration of 5 μg/mL (datasheet: A02837). Assess cytoplasmic staining in glandular cells and interpret it with the reported low consistency between antibody staining and RNA expression (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining in most tissues (HPA tissue IHC) | |
| Staining pattern | Glandular cells show cytoplasmic staining in several tissues (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen) | |
| Positive control | Appendix+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A02837) | |
| Caveat | Antibody staining has low consistency with RNA expression (HPA tissue IHC) | |
| Regulation | Expression varies by tissue and cell type (HPA tissue IHC) | |
| Isoform / epitope | 2 isoforms; epitope coverage is unspecified (UniProt) |
Compare the catalog antibody’s IHC-P protocol (datasheet) with two published kidney IHC protocols (PMC11896158; PMC11301351).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A02837); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-WWC1, 5 μg/mL (datasheet A02837) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | WWC1-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control. |
Expect predominantly cytoplasmic WWC1 staining in glandular cells, especially in appendix, duodenum, endometrium, epididymis, fallopian tube and small intestine (HPA: High in these cells; cytoplasmic expression in most tissues). Perinuclear and nuclear localisation is also reported, so assess compartment alongside tissue and cell identity (UniProt Q8IX03: subcellular location). WWC1 has no transmembrane segment (UniProt Q8IX03: topology). HPA rates tissue IHC Approved but reports low consistency between staining and RNA expression (HPA: reliability).
| Glandular cells show clear cytoplasmic chromogen above nearby background in appendix or duodenum (HPA: High in glandular cells). | This matches the reported IHC pattern when staining follows the glandular cell outlines and controls behave as expected (HPA: cytoplasmic expression in most tissues; general IHC practice). A positive slide supports the run; it does not resolve HPA’s reported staining–RNA inconsistency (HPA: reliability). |
| Staining is exclusively membranous, or outlines nearly every cell while expected glandular cytoplasm is blank. | Treat this as a localisation mismatch and investigate artefact or nonspecific detection (UniProt Q8IX03: no transmembrane segment; HPA: cytoplasmic expression in most tissues; general IHC practice). Do not reject a small perinuclear or nuclear component solely on its location (UniProt Q8IX03: subcellular location). |
| Strong colour appears in adipocytes, cardiomyocytes or bone marrow hematopoietic cells. | These cell populations are reported as Not detected, so prominent staining warrants checks for cross-reactivity or endogenous detection activity (HPA: adipose tissue, heart muscle and bone marrow IHC; general IHC practice). A negative atlas observation is a comparison, not proof that every sample must be blank (HPA: reliability). |
| Chromogen forms a widespread haze across cells, connective tissue and empty slide areas. | A pattern without cellular boundaries cannot establish WWC1 localisation (general IHC practice). Check background with a no-primary control, blocking and wash steps before scoring intensity (general IHC practice). HPA’s cytoplasmic profile describes cellular staining, not diffuse slide background (HPA: tissue IHC profile). |
| A known-positive glandular population has no discernible cytoplasmic signal. | First confirm that the expected cells are present, then review the IHC-P workflow and detection controls (HPA: High in glandular cells of appendix, duodenum, endometrium, epididymis, fallopian tube and small intestine; general IHC practice). Absence in one section alone does not establish true WWC1 loss (general IHC practice). |
| Tissue and cell selection | Use a reported High glandular population as a positive reference and score its cells separately from other compartments (HPA: appendix, duodenum, endometrium, epididymis, fallopian tube and small intestine). Breast glandular cells are reported Medium, so a weaker comparison there is plausible (HPA: breast IHC). |
| Evidence strength | The tissue IHC profile is Approved, with low consistency between antibody staining and RNA expression (HPA: reliability). The listed antibodies are IHC Approved; this record does not report IHC Enhanced validation (HPA: HPA038016 and HPA038017 antibody status). Interpret unexpected patterns cautiously and use appropriate controls (general IHC practice). |
| Antigen location and isoforms | WWC1 is a single reported protein chain with 2 isoforms and no transmembrane segment (UniProt Q8IX03: processing, isoforms and topology). The supplied evidence does not locate the catalog antibody’s epitope, so it cannot establish which isoforms it detects or predict an antigen retrieval response (UniProt Q8IX03: supplied record). |
| Endogenous detection activity | Chromogenic IHC can produce signal from tissue activity or nonspecific reagent binding; a no-primary control helps distinguish that background from primary-antibody-dependent staining (general IHC practice). Judge the control in the same cell population being scored (general IHC practice). |
| IF/ICC Q: What location should I expect? | A: HPA reports an approved Golgi apparatus location in ICC-IF images from A-431, U-251MG and U2OS (HPA: subcellular ICC-IF). UniProt also reports cytosol, perinuclear region and nucleus (UniProt Q8IX03: subcellular location). These IF observations do not establish a paraffin-section IHC staining pattern or an IF protocol (HPA: separate tissue IHC and ICC-IF records). |
| Situation | Likely cause | Next action |
|---|---|---|
| Positive-reference glandular cells remain blank (HPA: High glandular populations). | The expected cells may be absent from the section, or the IHC-P staining or detection run may have failed (general IHC practice). | Confirm the tissue and cell population; check the catalog antibody’s IHC-P instructions, reagent preparation and detection controls before interpreting a biological negative (general IHC practice). |
| Background obscures cytoplasmic boundaries. | Incomplete blocking, washing or detection-system background can mask cellular staining (general IHC practice). | Inspect the no-primary control, then review blocking, wash steps and detection-system controls; score only cellular signal distinguishable from background (general IHC practice). |
| Reported Not detected cells stain as strongly as the positive reference (HPA: listed negative cell populations). | Cross-reactivity or endogenous detection activity is possible; HPA’s low staining–RNA consistency also limits certainty (general IHC practice; HPA: reliability). | Compare the same cell types in a no-primary control and a reported High glandular tissue; investigate persistent primary-dependent staining before assigning WWC1 specificity (HPA: tissue IHC levels; general IHC practice). |
| Signal is predominantly a crisp plasma-membrane rim. | This conflicts with the reported predominantly cytoplasmic IHC profile and WWC1’s lack of a transmembrane segment (HPA: tissue IHC profile; UniProt Q8IX03: topology). | Review counterstain, cell boundaries and controls; document any cytoplasmic component separately and treat isolated rim staining as questionable (general IHC practice). |
| A nuclear or perinuclear component accompanies cytoplasmic staining. | WWC1 has reported nuclear and perinuclear localisation, although HPA describes cytoplasmic expression in most tissues (UniProt Q8IX03: subcellular location; HPA: tissue IHC profile). | Score compartments separately and compare them with controls and the expected cell population; do not classify the entire slide as nonspecific solely because of this component (general IHC practice). |
| IHC shows little Golgi-like concentration despite an ICC-IF report (HPA: Golgi apparatus, ICC-IF). | The HPA Golgi assignment comes from ICC-IF, while its tissue IHC summary describes cytoplasmic staining (HPA: subcellular ICC-IF and tissue IHC). | Interpret the paraffin-section slide against the tissue IHC pattern and its controls; reserve Golgi localisation assessment for the separate IF/ICC design (HPA: tissue IHC and subcellular ICC-IF; general IHC practice). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | High | Protein (IHC) | HPA → |
| Endometrium | Glandular cells | High | Protein (IHC) | HPA → |
| Epididymis | Glandular cells | High | Protein (IHC) | HPA → |
| Fallopian tube | Glandular cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Heart muscle | Cardiomyocytes | Not detected | Protein (IHC) | HPA → |
| Lymph node | Germinal center cells | Not detected | Protein (IHC) | HPA → |
| Parathyroid gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
Use compartment, cell type, and matched controls to troubleshoot WWC1 chromogenic staining in paraffin sections (UniProt Q8IX03; HPA tissue IHC).
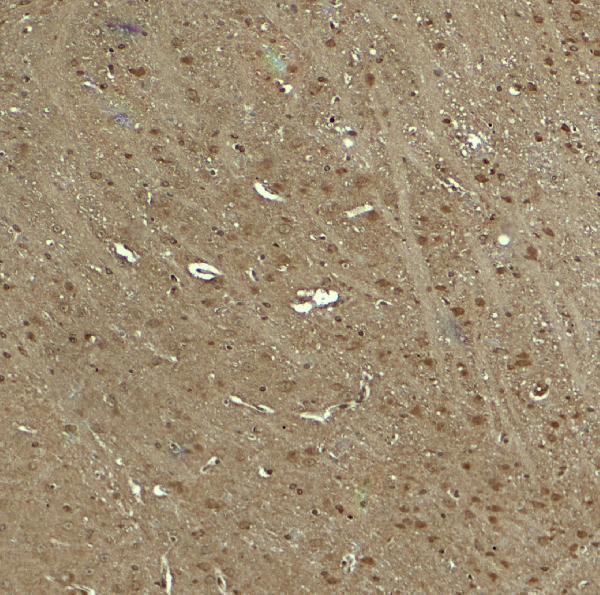
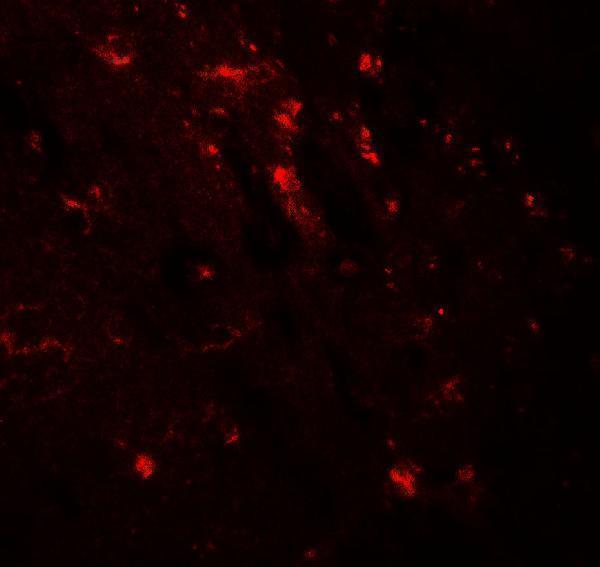
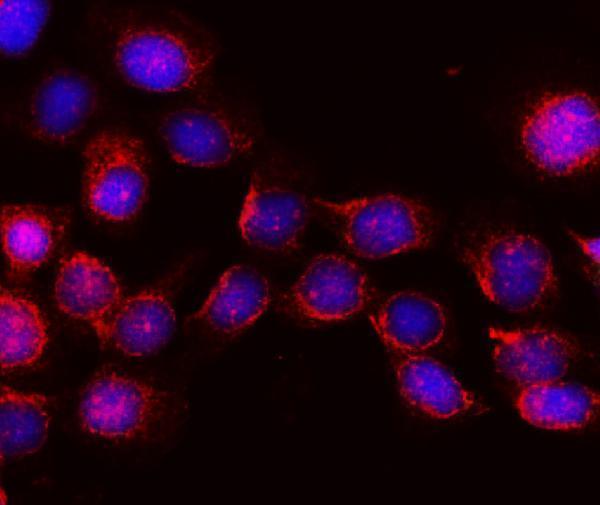
The catalog shows WWC1 IHC in mouse brain tissue (A02837 image caption) and IF/ICC in A431 cells (A02837-2 image caption); both antibodies list Human, Mouse, and Rat reactivity (catalog reactivity).
A02837 lists IHC-P and IF, with mouse brain tissue images for both applications (catalog applications; image captions). A02837-2 lists IF/ICC and shows staining in A431 cells; it has no listed IHC-P application (catalog applications; IF image caption).
Which to pick: Choose A02837 for paraffin-section tissue IHC: IHC-P is listed, and its own caption shows mouse brain IHC at 5 μg/mL; the fixative is unreported (catalog applications; A02837 IHC image caption). Choose A02837-2 for IF/ICC in cells: its own caption shows A431-cell staining at 5 μg/mL (catalog applications; A02837-2 IF image caption). For work across species, both list Human, Mouse, and Rat reactivity, but the pictured IHC evidence is limited to mouse tissue with A02837; both hosts are Rabbit and neither clone is specified (catalog reactivity, host and clone fields; A02837 IHC image caption).