ANXA4 / Annexin A4 · IHC design guide

Design Immunohistochemistry for ANXA4

Plan ANXA4 paraffin IHC using gallbladder glandular cells as a positive tissue control (HPA tissue IHC). Assess cytoplasmic and membranous epithelial staining, with separate attention to cilia in bronchus or fallopian tube (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ANXA4 (IHC for ANXA4): expected localisation Cytoplasmic and membranous in epithelia (HPA tissue IHC), antibody A04840, validated IHC image, and IHC protocol steps
Printable ANXA4 IHC protocol sheet — expected localisation Cytoplasmic and membranous in epithelia (HPA tissue IHC), antibody A04840, controls and protocol steps. Open the full ANXA4 IHC guide →

ANXA4 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and membranous in epithelia (HPA tissue IHC)
Staining pattern Most epithelial tissues show cytoplasmic and membranous staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A04840)
Positive control ⓘ Bronchus+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Cilia stain strongly in bronchus and fallopian tube (HPA tissue IHC)
Regulation Tissue-enhanced RNA: gallbladder, pancreas (HPA tissue RNA)
Isoform / epitope 3 isoforms; epitope coverage is unreported (UniProt)
Section 1

Recommended ANXA4 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet A04840) with published ANXA4 protocols for ovarian and cervical tissue (PMC3823662; PMC5746128; PMC4940752).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast cancer tissue; fixative not specified (datasheet A04840)
FixationImage fixative and duration unreported (datasheet A04840); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A04840); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A04840)
Primary antibodyRabbit anti-ANXA4, 2-5μg/ml (datasheet A04840)
Primary incubationOvernight at 4 °C (datasheet A04840)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A04840)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
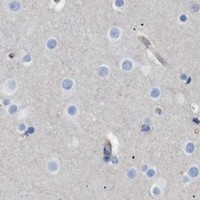
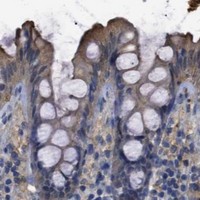
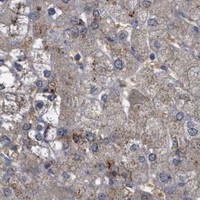
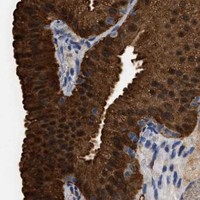
Expected resultANXA4-positive staining in ciliated cells (cilia axoneme) of bronchus (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic and membranous expression in most epithelial tissues. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 heat retrieval for the catalog antibody (datasheet A04840); the cervical study used pH 6.0 citrate for ANXA4 (PMC4940752).
Section 2

What Is the Expected ANXA4 Staining Pattern?

ANXA4 staining should be mainly cytoplasmic and membranous in epithelial cells, with strong signal in selected glandular and ciliated cells (HPA tissue IHC). HPA rates the tissue pattern Enhanced, while reporting medium consistency between staining and RNA data (HPA tissue IHC). UniProt places ANXA4 at the zymogen granule membrane and annotates no transmembrane segment (UniProt P09525 topology). Judge the stained cell type and compartment together.

What am I looking at on my slide?
Cytoplasmic or membranous stain in gallbladder glandular cells, or at bronchial cilia (HPA: High).This fits the reported IHC pattern (HPA tissue IHC). Record whether signal is in the glandular cell body or cilia; a brown deposit elsewhere in the section does not confirm the expected ANXA4 distribution.
Predominantly nuclear stain with little cytoplasmic or membranous signal.Treat this as a compartment mismatch: HPA reports cytoplasmic and membranous tissue staining and approved cytosolic ICC-IF localisation (HPA tissue IHC; HPA subcellular). Review morphology, controls and detection before assigning nuclear ANXA4.
Strong stain in adipocytes or cardiomyocytes, where ANXA4 was not detected (HPA tissue IHC).Unexpected staining may reflect cross-reactivity or endogenous detection activity (general IHC practice). Compare cell identity and matched negative controls; an HPA ‘Not detected’ entry describes its observed sample, not an absolute biological absence.
Broad, even colour over cells and surrounding section, obscuring boundaries.Diffuse background prevents a reliable compartment call (general IHC practice). Check the no-primary control and whether colour also covers tissue regions lacking the expected epithelial pattern; do not score background as ANXA4 positivity.
No stain in gallbladder glandular cells despite preserved morphology (HPA: High).The expected positive population is missing (HPA tissue IHC). Check a working positive control and the detection run before interpreting the specimen as negative; HPA’s Enhanced rating does not guarantee every section or antibody will stain.
💡Expected ANXA4 appearanceCall a result positive when distinct cytoplasmic or membranous signal appears in the expected epithelial cells, including High gallbladder glandular or bronchial ciliated cells (HPA tissue IHC); predominant nuclear colour or uniform background is suspect (HPA subcellular; general IHC practice).
How each factor affects the staining
Cell and tissue selectionHPA reports High staining in gallbladder glandular cells and bronchial cilia, but Low staining in rectal glandular cells (HPA tissue IHC). Compare like cell types when judging intensity.
Antibody evidenceThree listed antibodies have Enhanced IHC validation (HPA antibodies). That supports the reported pattern, while HPA describes only medium agreement with RNA; assess the actual slide and its controls (HPA tissue IHC).
Compartment and topologyANXA4 is associated with the zymogen granule membrane and has no transmembrane segment (UniProt P09525 topology). Membranous staining can fit the record; topology alone cannot identify which stained cellular boundary is specific.
Protein formsUniProt lists 3 isoforms and a chain spanning residues 2–319, with no signal peptide or propeptide (UniProt P09525). The payload gives no antibody epitope, so it cannot establish which isoforms the stain detects.
IF/ICC Q&A: what localisation should I expect?HPA approves cytosolic ICC-IF localisation and lists images from A-431, U-251MG and U2OS (HPA subcellular). Use that as an IF interpretation reference; tissue IHC additionally reports membranous epithelial staining (HPA tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Gallbladder glandular cells lack visible stain (HPA: High).A failed detection step or insufficient usable signal is possible (general IHC practice).Verify the positive control, reagent sequence and chromogen development; then review the antibody’s validated IHC-P instructions (general IHC practice).
The whole section is brown, including expected negative regions.Nonspecific binding or endogenous detection activity may contribute (general IHC practice).Inspect no-primary and detection controls; adjust blocking or detection conditions according to the assay controls (general IHC practice).
Only nuclei stain strongly.The compartment conflicts with HPA’s tissue and ICC-IF localisation (HPA tissue IHC; HPA subcellular).Recheck counterstain versus chromogen, controls and cell boundaries before scoring ANXA4 (general IHC practice).
Adipocytes stain as strongly as the epithelial positive control (HPA: Not detected in adipocytes).Cell misidentification, cross-reactivity or endogenous activity is possible (general IHC practice).Confirm morphology and compare matched controls; do not override the observed HPA pattern without independent evidence (HPA tissue IHC).
Only weak rectal glandular staining is visible (HPA: Low).Low signal can match the reported tissue pattern (HPA tissue IHC).Compare with a High-staining reference tissue under the same run before changing conditions (HPA tissue IHC; general IHC practice).
Signal differs between two IHC antibodies.The supplied record gives validation ratings but no epitopes or isoform coverage (HPA antibodies; UniProt P09525).Compare their validated controls and stained cell compartments; avoid attributing the difference to an isoform without epitope evidence.

Sample controls for ANXA4 IHC & IF

🧪Run gallbladder first: glandular cells should stain (HPA: High in gallbladder glandular cells). Use heart muscle as a negative tissue, focusing on cardiomyocytes (HPA: Not detected in cardiomyocytes); on the gallbladder slide, assess nonglandular areas for background, but do not treat them as validated negative cells because their ANXA4 status is unspecified (HPA: gallbladder row identifies glandular cells only).
Positive control tissue: Bronchus (Ciliated cells (cilia axoneme), HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show ANXA4 in A-431, U-251MG, U2OS, with annotated localisation: Cytosol (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit IgG isotype control (caption: rabbit primary antibody); use ANXA4 knockout tissue or cells, if available, as a biological negative (standard IHC practice). Quench endogenous peroxidase before HRP–DAB detection and inspect gallbladder pigment for brown signal that could be mistaken for DAB (caption: HRP–DAB detection; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A04840 paraffin-section caption does not state the fixative (caption: fixative unreported). The documented IHC workflow used heat retrieval in EDTA at pH 8.0, but whether ANXA4 staining depends on that retrieval condition is unreported (caption: EDTA retrieval); the supplied evidence does not establish that frozen sections or IF are easier (HPA: ICC-IF cytosolic localization). Gallbladder pigment may complicate interpretation of brown DAB signal (standard IHC practice).

HPA tissue IHC evidence for ANXA4

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Bronchus Ciliated cells (cilia axoneme) High Protein (IHC) HPA →
Fallopian tube Ciliated cells (cilia axoneme) High Protein (IHC) HPA →
Gallbladder Glandular cells High Protein (IHC) HPA →
Kidney Bowman's capsule High Protein (IHC) HPA →
Nasopharynx Ciliated cells (tip of cilia) High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Cerebral cortex Glial cells Not detected Protein (IHC) HPA →
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Section 3

Advanced ANXA4 IHC Tips

Troubleshoot ANXA4 staining in paraffin-section chromogenic IHC using the selected antibody workflow, tissue patterns, and compartment-specific controls.

Which retrieval conditions should I try first for weak ANXA4 staining?
Start with heat-mediated EDTA retrieval at pH 8.0 for ANXA4 paraffin-section IHC (datasheet A04840). The selected tissue image used this condition before 2 μg/ml primary antibody overnight at 4°C (datasheet A04840). If staining is weak, check heating consistency and section adhesion, using glandular cells in gallbladder as a reference for expected signal (standard IHC practice; HPA: gallbladder glandular cells high). Compare heat exposure on adjacent sections while keeping antibody concentration and DAB development constant (standard IHC practice). Prefer improved cellular staining over uniform darkening across the section (HPA: epithelial cytoplasmic and membranous profile; standard IHC practice).
How should I troubleshoot a possible fixation effect on ANXA4 IHC?
ANXA4-specific sensitivity to fixation is unknown because the selected paraffin-section image caption does not state a fixative (datasheet A04840). Record the actual fixative and fixation duration for each specimen, then compare sections processed identically through retrieval and detection (standard IHC practice). Hold EDTA at pH 8.0 and the 2 μg/ml primary concentration constant during that comparison (datasheet A04840). Include tissue with an expected positive glandular compartment and inspect tissue preservation alongside stain intensity (HPA: gallbladder glandular cells high; standard IHC practice). Neither reported tissue patterns nor protein modifications establish a fixation effect for this antibody (HPA: tissue IHC profile; UniProt P09525 modified residues).
Should ANXA4 appear on membranes, in cytoplasm, or in cilia?
Assess epithelial cytoplasmic and membranous staining as the main tissue pattern in chromogenic IHC (HPA: tissue IHC profile). Cytosol is the approved subcellular location, while zymogen granule membrane is also annotated for ANXA4 (HPA: subcellular location; UniProt P09525 subcellular location). High staining is reported in ciliated cells of bronchus and fallopian tube, including the cilia axoneme (HPA: bronchus and fallopian tube ciliated cells high). ANXA4 has no annotated transmembrane segment, so a sharp membrane outline alone does not establish membrane-spanning localisation (UniProt P09525 topology; standard IHC interpretation). Compare staining with cell morphology and a counterstain before assigning a compartment (standard IHC practice).
Can an ANXA4 epitope explain discordant staining between samples?
Three ANXA4 isoforms are listed, but the supplied antibody caption gives no epitope sequence or isoform coverage (UniProt P09525 isoforms; datasheet A04840). The annotated protein chain spans residues 2–319, and modified residues include positions 2, 7, 12, 213, and 293 (UniProt P09525 processing and modified residues). Those annotations do not establish which isoform or modification this antibody detects in tissue (UniProt P09525 isoforms and modified residues; datasheet A04840). Compare serial sections with an independently characterised ANXA4 antibody if epitope dependence is critical (standard IHC practice). Keep retrieval and detection matched, and interpret disagreement as unresolved until antibody specificity is checked (standard IHC practice).
How can IF help check a disputed ANXA4 IHC pattern?
Use IF as a separate localisation check, since the supplied ANXA4 tissue image documents chromogenic paraffin-section IHC (datasheet A04840). Multiplex ANXA4 with a validated marker for the expected cell type, such as a ciliated-cell marker when examining ciliated epithelium (HPA: bronchus and fallopian tube ciliated cells high; standard IF practice). Choose spectrally separated fluorophores and assess tissue autofluorescence in each channel, favouring a red or far-red channel when background is strong (standard IF practice). For a cytosolic epitope, optimise gentle permeabilisation; an epitope on the opposite side of a membrane requires access through that membrane (HPA: cytosol approved; standard IF practice). The supplied record does not identify this antibody’s epitope orientation or an IF fixation condition (datasheet A04840; UniProt P09525 topology).
What causes diffuse brown background in ANXA4 sections?
First compare a no-primary section with the stained section to locate background from detection reagents or endogenous peroxidase (standard IHC practice). The selected workflow used 10% goat serum blocking, a peroxidase-conjugated secondary for 30 minutes at 37°C, and DAB development (datasheet A04840). Verify that the routine peroxidase block and washes were effective, then shorten DAB development or retitrate primary antibody if staining remains diffuse (standard IHC practice). Inspect pigment, tissue edges, and damaged areas before calling brown deposits ANXA4-positive cells (standard IHC practice). Expected epithelial cytoplasmic or membranous distribution is a useful check against uniform haze (HPA: tissue IHC profile; standard IHC practice).
How should I quantify ANXA4 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the epithelial population and score cytoplasmic and membranous staining consistently across all sections (HPA: tissue IHC profile; standard IHC practice). An H-score combines percentages at intensities 0–3 and ranges from 0–300; report the scoring rules with the result (standard IHC practice). Alternatively, report the percentage of positive cells or positive-cell density per mm² of evaluable tissue (standard IHC practice). Normalise counts to the relevant epithelial-cell denominator or measured epithelial area, and exclude folds, necrosis, and unstained tissue (standard IHC practice). Keep retrieval, antibody concentration, DAB timing, and image thresholds consistent across the comparison (standard IHC practice).
When is an ANXA4-positive IHC signal convincing rather than artefactual?
A convincing result follows cellular boundaries and expected cytoplasmic or membranous compartments, with morphology visible in the counterstain (HPA: tissue IHC profile; standard IHC practice). High signal in gallbladder glandular cells provides a reference, while reported absent staining in adipocytes can help assess nonspecific staining within an appropriate section (HPA: gallbladder glandular cells high; HPA: adipocytes not detected). Treat isolated edge staining, necrotic deposits, and uniform nuclear or extracellular colour cautiously (standard IHC practice; HPA: cytosol approved). Compare a no-primary control to identify endogenous enzyme or detection background before interpreting DAB deposits (standard IHC practice). HPA labels tissue reliability Enhanced but reports medium agreement with RNA, so confirm unexpected patterns independently (HPA: tissue IHC reliability description).
Boster reagents

Best ANXA4 / Annexin A4 IHC Antibodies

Three antibodies have ANXA4 IHC images from human or rat paraffin sections (catalog: IHC image captions); a human-reactive IF/ICC antibody is listed without an IF image (catalog: M04840-1).

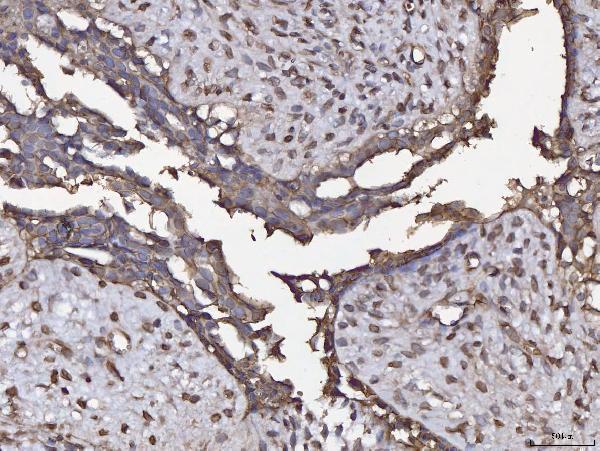
Real IHC data IHC analysis of ANXA4 using anti-ANXA4 antibody (A04840). ANXA4 was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-ANXA4 Antibody (A04840) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-Annexin IV/ANXA4 Antibody ®
Cat # A04840
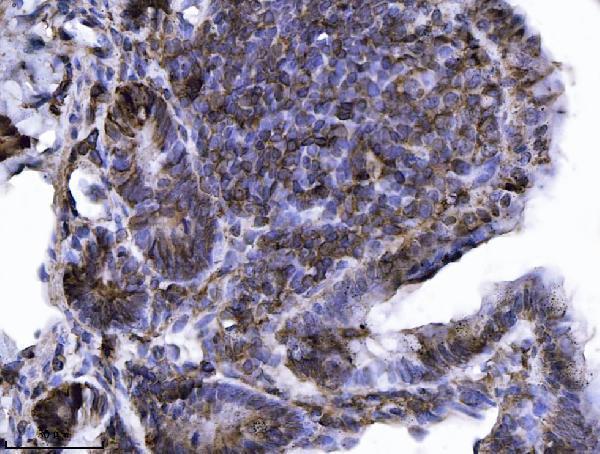
Real IHC data IHC analysis of Annexin-4/ANXA4 using anti-Annexin-4/ANXA4 antibody (A04840-2). Annexin-4/ANXA4 was detected in a paraffin-embedded section of rat colon tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-Annexin-4/ANXA4 Antibody (A04840-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-Annexin-4/ANXA4 Antibody ®
Cat # A04840-2
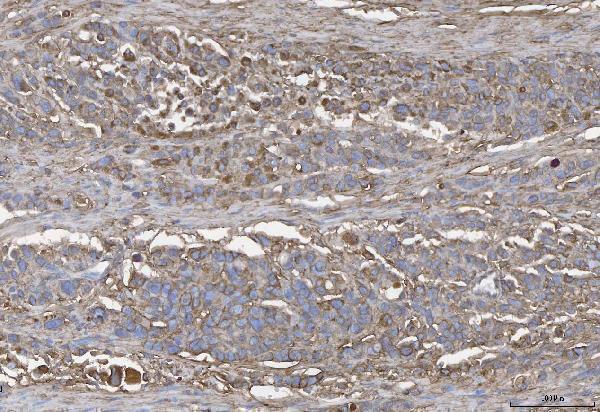
Real IHC data IHC analysis of Annexin IV/ANXA4 using anti-Annexin IV/ANXA4 antibody (PA1007-1). Annexin IV/ANXA4 was detected in a paraffin-embedded section of Human Mammary Cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1 μg/ml rabbit anti-Annexin IV/ANXA4 Antibody (PA1007-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-Annexin IV/ANXA4 Antibody ®
Cat # PA1007-1

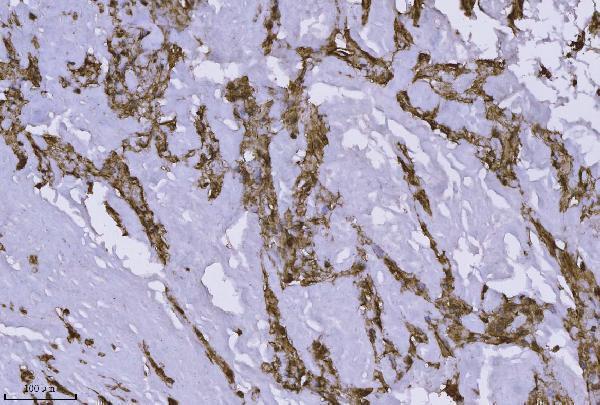
A04840 shows human breast cancer paraffin sections (A04840 image caption), and A04840-2 shows rat colon paraffin sections (A04840-2 image caption). PA1007-1 shows human mammary cancer paraffin sections (PA1007-1 image caption); all three list IHC and human, mouse, and rat reactivity (catalog: applications and reactivity).

Which to pick: For tissue IHC, choose A04840 for human breast cancer, A04840-2 for rat colon, or PA1007-1 for human mammary cancer paraffin sections (each SKU’s IHC image caption). For IF/ICC, M04840-1 is a human-reactive rabbit monoclonal, clone 19A60, with IF/ICC listed but no IF image supplied (catalog: M04840-1). For cross-species IHC, A04840, A04840-2, and PA1007-1 list human, mouse, and rat reactivity (catalog: reactivity); each caption documents paraffin sections with EDTA retrieval at pH 8.0, but does not report the fixative (each SKU’s IHC image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P09525 (ANXA4_HUMAN, Annexin A4).
  2. Human Protein Atlas. ANXA4 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. ANXA4 subcellular location (ICC-IF): Localized to the cytosol..
  4. Human Protein Atlas. ANXA4 antibody validation summary (3 antibodies).
  5. Annexin A4 is involved in proliferation, chemo-resistance and migration and invasion in ovarian clear cell adenocarcinoma cells. PloS one 2013 — PMC3823662.
  6. Annexin A4 fucosylation enhances its interaction with the NF-kB p50 and promotes tumor progression of ovarian clear cell carcinoma. Oncotarget 2017 — PMC5746128.
  7. Prognostic significance of annexin A2 and annexin A4 expression in patients with cervical cancer. BMC cancer 2016 — PMC4940752.
  8. Annexin A4-nuclear factor-κB feedback circuit regulates cell malignant behavior and tumor growth in gallbladder cancer. Scientific reports 2016 — PMC4974512.
  9. PubMed PMID:2970257 — UniProt-cited evidence.
  10. PubMed PMID:1346776 — UniProt-cited evidence.
  11. PubMed PMID:9084877 — UniProt-cited evidence.