AVEN / Cell death regulator Aven · IHC design guide

Design Immunohistochemistry for AVEN

Plan chromogenic AVEN IHC on paraffin sections using the catalog antibody at 1:100–1:300 (datasheet A08274). Use high cytoplasmic staining in colon glandular cells as a positive reference (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for AVEN (IHC for AVEN): expected localisation General cytoplasmic tissue staining (HPA tissue IHC), antibody A08274, validated IHC image, and IHC protocol steps
Printable AVEN IHC protocol sheet — expected localisation General cytoplasmic tissue staining (HPA tissue IHC), antibody A08274, controls and protocol steps. Open the full AVEN IHC guide →

AVEN Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation General cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Glandular and other positive cells show cytoplasmic staining (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A08274)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Soft tissue
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Liver and kidney stain low despite reported high expression (HPA tissue IHC; UniProt)
Regulation No expression regulator specified (UniProt)
Isoform / epitope No annotated isoforms or cleavage; one 1–362 chain (UniProt)
Section 1

Recommended AVEN IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet: A08274) is followed by published AVEN IHC methods for mouse brain (PMC12552703) and human skin (PMC4392043).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human Colon cancer tissue; fixative not specified (datasheet A08274)
FixationImage fixative and duration unreported (datasheet A08274); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Tris-EDTA pH 9.0 (datasheet A08274); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-AVEN, 1:100-1:300 (datasheet A08274)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultAVEN-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated Tris-EDTA retrieval at pH 9.0 (datasheet: A08274); neither published excerpt specifies retrieval (PMC12552703; PMC4392043).
Section 2

What Is the Expected AVEN Staining Pattern?

AVEN shows general cytoplasmic staining in tissue IHC (HPA: tissue IHC profile; Approved, with medium consistency against RNA data). Intracellular membrane association is also annotated (UniProt Q9NQS1: endomembrane system; no transmembrane segment). Expect staining in the cell populations HPA identifies, including colon glandular cells and pancreatic exocrine glandular cells (HPA: High in both).

What am I looking at on my slide?
Distinct cytoplasmic staining in colon glandular cells or pancreatic exocrine glandular cells.This fits the reported tissue pattern (HPA: High in both cell populations; general cytoplasmic expression). Judge the cellular distribution alongside a negative detection control, since brown signal alone does not establish AVEN specificity (general IHC practice).
Predominantly nuclear staining, with little cytoplasmic signal, in an otherwise positive tissue.This conflicts with the tissue IHC profile (HPA: general cytoplasmic expression). Treat it as a possible staining artefact or antibody-specific pattern; review controls and the IHC-validated antibody’s validation before assigning it to AVEN (general IHC practice).
Strong staining in soft-tissue fibroblasts while expected positive cells also stain.HPA reports AVEN as Not detected in soft-tissue fibroblasts (HPA: soft tissue, fibroblasts). Check for cross-reactivity or endogenous detection activity with appropriate controls (general IHC practice). That HPA observation does not make every fibroblast in every tissue a universal negative control.
Uniform colour across cells, stroma and areas without tissue.A broad deposit has little resemblance to cell-specific cytoplasmic staining (HPA: tissue IHC profile). Suspect nonspecific background or detection chemistry; compare with a no-primary control and inspect blocking, washes and chromogen development (general IHC practice).
No convincing signal in colon glandular cells or pancreatic exocrine glandular cells.These are reported High populations (HPA: colon and pancreas). First check section quality and a working detection control, then review the antibody’s IHC-P instructions, retrieval and detection steps (general IHC practice). A single negative section does not overturn the HPA pattern.
💡Expected AVEN appearanceCall positive a discernible cytoplasmic signal in the appropriate cells, potentially strong in colon glandular or pancreatic exocrine glandular cells (HPA: High; general cytoplasmic expression); uniform background or isolated nuclear colour is suspect (general IHC practice).
How each factor affects the staining
Choice of comparison tissue (HPA: tissue IHC)Colon glandular and pancreatic exocrine glandular cells are High, while liver hepatocytes and kidney tubular cells are Low (HPA: listed cell populations). Compare the named cells, since staining strength is not uniform across tissues.
IHC evidence and antibody validation (HPA: tissue IHC; HPA020863)The tissue profile is Approved but has medium consistency with RNA data (HPA: reliability). HPA020863 is IHC Approved (HPA: antibody validation); neither label guarantees that every chromogenic deposit is target-specific.
Compartment and topology (HPA: tissue IHC; UniProt Q9NQS1)General cytoplasmic tissue staining is reported (HPA: tissue IHC). AVEN is associated with intracellular membranes and has no transmembrane segment (UniProt Q9NQS1); that annotation does not predict a crisp cell-surface outline in paraffin IHC.
IF/ICC: what should a different localisation mean? (HPA: subcellular ICC-IF)HPA lists plasma membrane as approved in ICC-IF, with actin filaments and centrosome uncertain (HPA: subcellular). Interpret that assay-specific observation separately from the general cytoplasmic tissue IHC profile (HPA: tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Positive tissue has no cytoplasmic signal (HPA: High in colon glandular cells).A failed IHC step or unsuitable assay conditions are possibilities (general IHC practice); this record gives no AVEN-specific fixation sensitivity.Confirm tissue identity and cell type, run a working detection control, and check the antibody’s IHC-P instructions for retrieval and dilution (general IHC practice).
Signal is weak in liver hepatocytes or kidney tubular cells (HPA: Low in both).Low staining is consistent with the reported cell-level observations (HPA: liver and kidney); it need not indicate assay failure.Assess a reported High population, such as colon glandular cells, on a suitable control section before changing assay conditions (HPA: High in colon; general IHC practice).
Stroma or soft-tissue fibroblasts stain as strongly as glandular cells.Nonspecific binding or endogenous detection activity is possible (general IHC practice); soft-tissue fibroblasts are Not detected in HPA’s tissue profile (HPA: soft tissue).Check a no-primary control and the detection system’s blocking steps; compare the same cell populations rather than treating all stromal cells as equivalent (general IHC practice).
Signal is mainly nuclear, with little cytoplasmic staining.The pattern disagrees with general cytoplasmic tissue expression (HPA: tissue IHC) and may reflect an assay artefact (general IHC practice).Review control sections and confirm that cytoplasmic signal appears in a reported High cell population before scoring the nuclear deposit as AVEN (HPA: High in colon glandular cells; general IHC practice).
Brown colour appears broadly, including in areas without tissue.Diffuse background can arise from detection reagents, incomplete washes or excessive chromogen development (general IHC practice).Compare a no-primary control, inspect washing and development, and score cellular staining only after background is controlled (general IHC practice).
IF/ICC images suggest a cell outline, while IHC shows cytoplasmic staining.The assays have different reported patterns: plasma membrane is approved in ICC-IF, whereas tissue IHC is generally cytoplasmic (HPA: subcellular; tissue IHC).Interpret each result using its assay-specific HPA evidence; keep actin-filament and centrosome assignments provisional because HPA marks them uncertain (HPA: subcellular).

Sample controls for AVEN IHC & IF

🧪Run colon first: glandular cells should stain (HPA: High in colon glandular cells). Use soft tissue fibroblasts as the negative tissue (HPA: Not detected in soft tissue fibroblasts); on the colon slide, cells judged negative should lack specific chromogen deposition, but do not assume a particular cell type is AVEN-negative.
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Soft tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show AVEN in A-431, U-251MG, U2OS, with annotated localisation: Plasma membrane (approved), Actin filaments (uncertain) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) control, a host-species- and antibody-class-matched isotype control where applicable, and an AVEN knockout specimen as a biological negative if available. For chromogenic colon IHC, quench endogenous peroxidase and check luminal mucus and debris for nonspecific staining (standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported in the supplied evidence, and the selected A08274 colon-cancer caption does not state the fixative (selected-SKU caption: fixative not stated). That caption reports Tris-EDTA retrieval at pH 9.0 and primary antibody at 1:200, but does not establish that retrieval is required (selected-SKU caption). The evidence does not establish whether frozen sections or IF/ICC are easier than paraffin IHC; inspect colon luminal mucus and debris when assessing staining (standard IHC practice).

HPA tissue IHC evidence for AVEN

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Cerebellum Purkinje cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Gallbladder Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Soft tissue Fibroblasts Not detected Protein (IHC) HPA →
Section 3

Advanced AVEN IHC Tips

Troubleshoot AVEN staining in paraffin sections by checking retrieval, cell type, compartment and controls before comparing staining intensity.

How should I retrieve AVEN antigen when staining paraffin sections?
Start with heat-mediated Tris-EDTA at pH 9.0 for AVEN antigen retrieval in paraffin-section IHC (datasheet A08274). The selected colon cancer image used that retrieval, a 1:200 primary antibody dilution at 4°C overnight, and a 1:200 secondary antibody dilution for 45 minutes at room temperature (caption A08274). If staining is weak, compare sections processed with the same retrieval method while checking reagent performance and tissue preservation (standard IHC practice). Keep retrieval conditions identical across comparison slides, because uneven heating or tissue loss can make differences in AVEN staining difficult to interpret (standard IHC practice).
Could fixation explain weak AVEN staining in my paraffin sections?
Target-specific sensitivity of AVEN to fixation is unknown from the supplied evidence, and the selected paraffin-section caption does not state a fixative (caption A08274). Record the actual fixative, time before fixation, and fixation duration for each specimen before comparing staining results (standard IHC practice). Process a known staining control alongside the test section and inspect tissue preservation and section adherence before changing antibody conditions (standard IHC practice). If specimens differ in fixation history, compare them cautiously and optimize processing with matched material where possible; neither tissue staining patterns nor AVEN topology establishes a fixation effect for this antibody (standard IHC practice; UniProt Q9NQS1 topology).
Which AVEN staining compartments should I expect in tissue IHC?
Expect a broadly cytoplasmic tissue-IHC pattern as the initial reference for AVEN (HPA: general cytoplasmic expression). AVEN is associated with intracellular membranes and has no annotated transmembrane segment (UniProt Q9NQS1 subcellular location and topology). Separate tissue-IHC evidence from cell-based IF observations: the latter report an approved plasma membrane location, with actin-filament and centrosome locations marked uncertain (HPA subcellular). Examine intact cells at high magnification and compare staining with a matched negative control before assigning a compartment (standard IHC practice). A purely nuclear or diffuse extracellular signal needs additional validation rather than an automatic AVEN localisation call (HPA tissue IHC; standard IHC practice).
How do I assess an unexpected AVEN staining pattern without an epitope map?
AVEN has one annotated chain spanning residues 1–362, with no annotated isoforms, glycosylation sites, or transmembrane segment in the supplied record (UniProt Q9NQS1). Phosphoserine at residue 94 and N6-methyllysine at residue 230 are listed modifications, but the antibody epitope is not supplied (UniProt Q9NQS1; supplied antibody evidence). Do not attribute a changed paraffin-section staining pattern to either modification without epitope and assay evidence (standard IHC interpretation). Check antibody documentation for its immunogen, then compare independent staining controls and tissue morphology before treating a compartment shift or lost signal as AVEN biology (standard IHC practice).
How should I check an AVEN IHC pattern using multiplex IF?
Use multiplex IF as a separate check of the cell populations that carry the chromogenic AVEN signal, rather than transferring the paraffin-section detection settings directly (standard IF practice; caption A08274). Pair AVEN with a marker of the expected cell type; colon glandular cells are one evidence-based comparison population (HPA: high in colon glandular cells). Choose spectrally separated fluorophores after checking tissue autofluorescence and include single-stain controls for bleed-through (standard IF practice). Because AVEN has no transmembrane segment and is associated with intracellular membranes, choose permeabilisation according to the mapped antibody epitope and whether that epitope faces an accessible compartment (UniProt Q9NQS1 topology and location; standard IF practice).
What should I check when AVEN staining covers the entire section?
First compare an antibody-omission control with the AVEN-stained section to identify detection-system background (standard IHC practice). In chromogenic IHC, block endogenous peroxidase before a peroxidase-based detection step and assess DAB deposition independently of the primary antibody (standard IHC practice). Check blocking, washes, section drying, and whether excess chromogen development produces diffuse colour across otherwise preserved tissue (standard IHC practice). The selected paraffin-section image used a 1:200 primary antibody dilution at 4°C overnight, but those conditions alone do not establish specificity in another specimen (caption A08274; standard IHC interpretation). Recheck cell borders and tissue morphology before calling widespread AVEN positivity (standard IHC practice).
How should I quantify AVEN staining across paraffin-section samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and tissue area before scoring, and exclude folds, detached tissue, necrosis, and visibly damaged edges (standard IHC practice). For glandular samples, score staining within the relevant viable cells rather than using total section area as the denominator (standard IHC practice; HPA: high in colon glandular cells). Report percentage of positive cells with an intensity-based H-score, or report positive-cell density per mm² when counts fit the study design (standard IHC practice). Normalize comparisons to the same cell population, viable area, staining run, and scoring thresholds, then retain separate records for cytoplasmic and other compartment assignments (standard IHC practice; HPA tissue IHC profile).
How can I distinguish genuine AVEN staining from an IHC artefact?
Look for staining within preserved cells in a plausible compartment, using the general cytoplasmic tissue-IHC pattern as the reference (HPA: general cytoplasmic expression; standard IHC practice). Colon glandular cells provide a reported high-staining comparison, while soft-tissue fibroblasts were reported as not detected; neither observation alone validates a new slide (HPA tissue IHC). Question staining confined to cut edges, necrotic zones, or extracellular debris, and investigate nuclear-only staining against appropriate controls (standard IHC practice; HPA tissue IHC profile). If an antibody-omission control retains chromogen, examine endogenous enzyme activity or detection reagents before calling AVEN positive (standard IHC practice).
Boster reagents

Best AVEN / Cell death regulator Aven IHC Antibodies

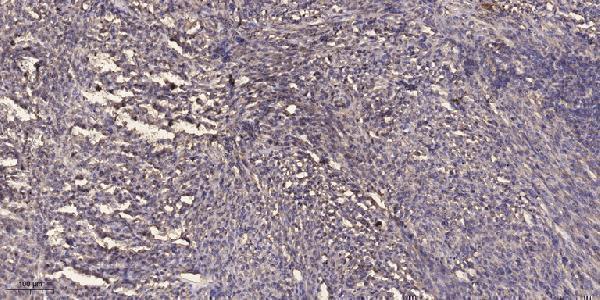
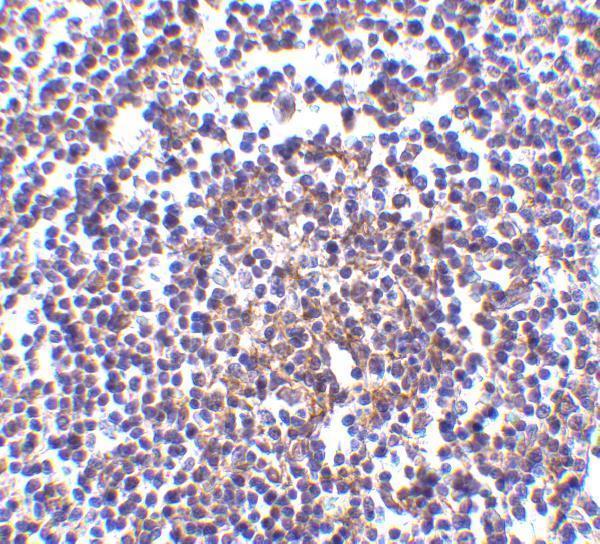
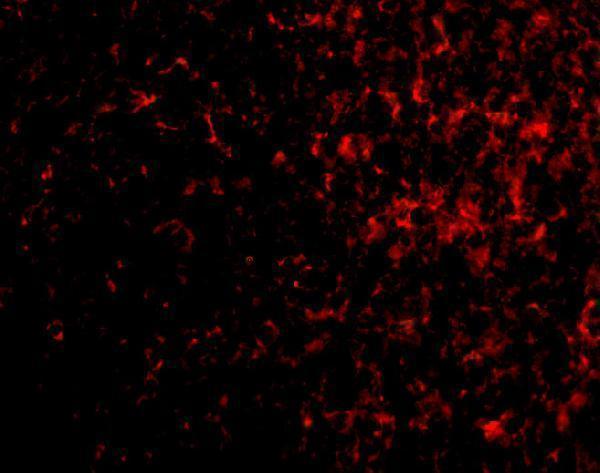
Two anti-AVEN antibodies have human tissue IHC images (A08274 IHC caption: colon cancer; A08274-1 IHC caption: spleen); A08274-1 also has a human spleen-cell IF image (A08274-1 IF caption).

Real IHC data Immunohistochemical analysis of paraffin-embedded human Colon cancer. 1, Antibody was diluted at 1:200 (4° overnight). 2, Tris-EDTA, pH9.0 was used for antigen retrieval. 3, Secondary antibody was diluted at 1:200 (room temperature, 45min).
Anti-Cell death regulator Aven Aven Antibody
Cat # A08274
Real IHC data Immunohistochemistry of Aven in human spleen tissue with Aven antibody at 5 μg/mL.
Anti-Cell death regulator Aven Aven Antibody
Cat # A08274-1

A08274 supports IHC in paraffin-embedded human colon cancer (A08274 IHC caption) and lists IF for human and monkey samples (A08274 catalog: applications and reactivity). A08274-1 shows IHC in human spleen tissue and IF in human spleen cells (A08274-1 IHC and IF captions), with mouse and rat reactivity listed (A08274-1 catalog: reactivity).

Which to pick: For paraffin-section IHC, choose A08274, whose image used 1:200 on paraffin-embedded human colon cancer (A08274 IHC caption); A08274-1 offers IHC-P with a human spleen image at 5 μg/mL (A08274-1 catalog: applications; A08274-1 IHC caption), but neither IHC caption reports the fixative (A08274 and A08274-1 IHC captions). For IF, A08274-1 has a human spleen-cell image at 20 μg/mL (A08274-1 IF caption); ICC validation is unreported (both catalogs: applications). For species selection, A08274 lists human and monkey reactivity and is polyclonal (A08274 catalog: reactivity and dilution_raw), while A08274-1 lists human, mouse and rat reactivity with clonality unspecified (A08274-1 catalog: reactivity and clone).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9NQS1 (AVEN_HUMAN, Cell death regulator Aven).
  2. Human Protein Atlas. AVEN tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. AVEN subcellular location (ICC-IF): Mainly localized to the plasma membrane and actin filaments. In addition localized to the centrosome..
  4. Human Protein Atlas. AVEN antibody validation summary (1 antibodies).
  5. An expression screen for aged-dependent microRNAs identifies miR-30a as a key regulator of aging features in human epidermis. Aging 2017 — PMC5723692.
  6. The impact of PANoptosis-related genes on immune profiles and subtype classification in ischemic stroke. Scientific reports 2025 — PMC12552703.
  7. Proteasome localization and activity in pig brain and in vivo small molecule screening for activators. Frontiers in cellular neuroscience 2024 — PMC10925635.
  8. Psoriasis drug development and GWAS interpretation through in silico analysis of transcription factor binding sites. Clinical and translational medicine 2015 — PMC4392043.
  9. PubMed PMID:10949025 — UniProt-cited evidence.
  10. PubMed PMID:15489334 — UniProt-cited evidence.
  11. PubMed PMID:17081983 — UniProt-cited evidence.